Being told that there is “no bone” for dental implants can sound like a final diagnosis. It is not. The phrase may describe a narrow ridge at one missing tooth, reduced height below a sinus, loss of support around remaining teeth, a severely resorbed edentulous jaw, or simply the limits of a particular scan, technique or provider. Those situations do not carry the same choices or risks. A responsible assessment replaces the slogan with a site-by-site diagnosis and a prosthetic question: what, if anything, needs replacing, and what option can be maintained safely?
Severe bone loss also does not create a promise that an implant can be placed. Bone augmentation, shorter or narrower implants, tilted implants and zygomatic implants are different clinical categories with different evidence, anatomy, competence requirements and complications. None is a universal escape route. Sometimes a restorable tooth should be retained. Sometimes a bridge, removable prosthesis or no immediate replacement is more proportionate. Sometimes disease must be controlled before any replacement decision. In another case, the safest conclusion may be that an implant plan should be postponed or declined.
This is an evidence-led decision guide for adults researching dental implants with severe bone loss, including people considering treatment abroad. It is not a diagnosis, personal recommendation, prescription, quotation, timetable or result promise. A remote photograph or panoramic image may help organise questions, but it cannot establish implant suitability. The named clinicians who examine the patient, interpret the necessary records and accept responsibility for each procedure must make and document the decisions.
“No bone” is a description to investigate, not a treatment plan
Ask what the original statement meant. Was the problem at one premolar, several posterior sites, the whole upper jaw, the whole lower jaw, or around teeth that are still present? Was it based on a clinical examination, two-dimensional radiograph, cone-beam computed tomography, or a quick visual opinion? Did it refer to ridge width, ridge height, bone quality, a sinus, a nerve canal, active periodontal disease, a previous failed implant, or the intended position of a particular restoration? Was the clinician saying “not possible here,” “not suitable for me to perform,” “not suitable without reconstruction,” or “not proportionate to your goals and risks”?
Those distinctions matter. Bone that looks adequate on a panoramic image may be too narrow in a critical direction. A dramatic-looking defect may still permit several non-implant choices. A technically placeable fixture may emerge in a position that cannot support a cleanable or functional restoration. Conversely, a missing posterior tooth may not require immediate replacement if the remaining dentition is stable and the patient accepts the trade-offs. The decision is not simply whether a drill can enter bone.
A useful written problem list should identify:
- each tooth or missing site under consideration rather than labelling an entire mouth;
- whether any tooth is restorable, uncertain or non-restorable, and why;
- active caries, endodontic disease, periodontal inflammation or peri-implant disease;
- the shape and location of the hard-tissue defect and the condition of the soft tissues;
- nearby anatomical structures relevant to surgery;
- the intended restoration, space, appearance, speech, chewing and hygiene requirements;
- medical, medicine and behavioural factors that may alter risk or healing;
- reasonable implant, non-implant and no-treatment alternatives;
- what remains uncertain until examination, imaging, surgery or healing;
- who is responsible for surgery, restoration, maintenance, urgent care and any referral.
If a sales message jumps from “no bone” directly to a named procedure, fixed package or same-day teeth, it has skipped the most important steps.
Deal with urgent disease before elective implant planning
Reduced bone may coexist with infection or another urgent problem. Rapidly increasing facial or neck swelling, difficulty breathing or swallowing, uncontrolled bleeding, severe trauma, altered consciousness or another medical emergency requires urgent local assessment rather than travel planning or an online quotation. Fever, spreading swelling, discharge, worsening pain, persistent numbness, an exposed wound, a loose implant or prosthesis, or an inability to eat or drink also warrants prompt professional advice. Local emergency pathways should be known before leaving home and before returning from treatment abroad.
Pain alone does not prove that a bone graft or implant is needed. It may arise from a tooth, periodontal tissues, an existing implant, sinus disease, jaw muscles, a nerve-related condition or another cause. Antibiotics do not replace drainage, diagnosis or definitive dental care, and there is no universal antibiotic regimen for bone-loss cases. An authorised prescriber must consider the diagnosis, allergies, interactions, medical history, local guidance and the procedure. Do not self-start leftover medication or change prescribed anticoagulants, antiresorptive medicines, steroids, diabetes treatment or other medicines without the relevant clinician.
Elective implant planning should not be used to conceal uncontrolled disease. Active periodontal inflammation, untreated caries, an unresolved endodontic source, poor plaque control or a prosthesis that cannot be cleaned may change the order of care. The European Federation of Periodontology guideline on prevention and treatment of peri-implant diseases supports a structured pathway that includes control of periodontal and peri-implant risk, cleanable prosthetic design and supportive care. A plan should state what must be stabilised and how stability will be reassessed.
Preserve a restorable natural tooth before creating an implant site
“Not enough bone” can be used inappropriately to turn a compromised tooth into an implant sale. Extraction is irreversible. Before removing a tooth, ask whether it can reasonably be retained through periodontal treatment, restorative care, endodontic treatment or retreatment, repair, orthodontic movement, crown-length considerations, monitoring, or another conservative approach. A tooth may still be non-restorable, but the reason should be recorded rather than assumed.
The American Association of Endodontists position statement warns against treating implants as a panacea and says retention should be the first consideration for a compromised natural tooth. It also recognises that implants can be useful when teeth are missing or cannot be saved. These are complementary decisions, not competing products. A person facing extraction should understand the prognosis and burden of retaining the tooth, the prognosis and burden of extraction and replacement, the option of no immediate replacement, and the uncertainty attached to each route.
Questions worth putting in writing include:
- What exact finding makes this tooth non-restorable?
- Has an appropriate restorative, periodontal or endodontic opinion been obtained?
- Which records support the prognosis?
- Could disease control or a less destructive procedure meet the goal?
- What would happen if treatment were deferred or the tooth monitored?
- If extraction proceeds, what are the replacement and no-replacement options?
- Does extraction make future reconstruction more complex, and is any socket or ridge management proposed?
A second opinion is particularly reasonable when the recommendation involves removing several teeth, converting a partly dentate mouth to a full-arch prosthesis, undertaking advanced augmentation, or changing a stable removable solution to a surgical one. A second opinion is not disloyal; it is a normal way to test an irreversible plan.
Diagnose the patient, arch, site and disease separately
Severe bone loss is not one condition. Diagnosis should move from the whole person to the proposed restoration and then to each surgical site.
Medical and medicine history
The clinician needs an accurate medical history, medicine list, allergies and relevant previous events. Important information can include cardiovascular and respiratory disease, diabetes and its control, immune conditions, bleeding disorders, cancer treatment, radiotherapy, current or previous antiresorptive or antiangiogenic medicines, steroid exposure, transplant history, allergies, adverse reactions to anaesthesia or antibiotics, smoking or nicotine use, alcohol or drug use, pregnancy possibility and the capacity to follow hygiene and review. This list does not automatically include or exclude anyone. It identifies questions for the clinician and, when appropriate, for the patient’s medical team.
The relevant risk is not captured by a single checkbox. For example, the name “diabetes” without recent control information is incomplete. “Blood thinners” may represent different medicines and indications. A history of medication associated with jaw complications requires careful individual assessment, not casual reassurance or unilateral interruption. A complex sedation or general-anaesthetic plan raises questions about facilities, monitoring, recovery and emergency arrangements that are separate from the implant itself.
Dental and periodontal history
Record why teeth were lost, when changes occurred, previous periodontal treatment, previous implants or grafts, complications, maintenance attendance, dry mouth, decay experience, grinding or clenching symptoms, denture tolerance and cleaning ability. Bone loss caused or accompanied by periodontal disease creates a different maintenance problem from a local defect after trauma. The remaining teeth, gums and existing implants need examination; planning only the empty space is not enough.
The periodontal assessment should establish inflammation, plaque control, pocketing, bleeding, mobility, recession and patterns of bone support where relevant. Disease diagnosis and control should be explicit. The future prosthesis must permit the patient and dental team to inspect and clean it. A design that looks attractive in a photograph but blocks hygiene access transfers risk into long-term care.
Functional and prosthetic assessment
Assess how the teeth meet, available restorative space, jaw relationships, tooth wear, parafunction, opening, speech, smile and lip support, opposing teeth and the distribution of forces. A replacement for one tooth presents a different biomechanical question from a long-span bridge or a full-arch prosthesis. The clinician should understand what the patient expects to eat, how a removable option would be tolerated, whether appearance or function is the main priority and what compromises are acceptable.
Photographs, scans, impressions, mounted models or a diagnostic set-up may be appropriate depending on complexity. These records are not decoration. They allow the team and patient to test tooth position, contours, cleaning space, lip support and restorative dimensions before surgery commits the implant positions.
Hard and soft tissue at each site
Bone should not be described only as “enough” or “not enough.” The assessment may consider ridge width, height, contour, defect shape, cortical and cancellous characteristics, relation to adjacent roots and implants, previous extraction sockets, scar tissue, infection, and the position of anatomical boundaries. Soft-tissue quantity, thickness, mobility, keratinised tissue, vestibular depth, papillae and cleansability may also influence planning. Hard-tissue reconstruction cannot automatically solve an unfavourable soft-tissue or prosthetic problem.
The defect may be horizontal, vertical, combined, contained or non-contained, localised or extensive. The upper posterior jaw raises sinus and nasal questions. The lower posterior jaw raises inferior alveolar and mental nerve questions. Anterior sites add appearance, speech and tissue-contour demands. A full edentulous arch adds jaw relationship, lip support, restorative space and prosthesis maintenance. These are reasons to avoid universal millimetre thresholds in a public decision guide.
Imaging must answer a justified clinical question
No single image should be marketed as proof of suitability. Current ADA and American Academy of Oral and Maxillofacial Radiology recommendations place history and clinical examination before imaging selection. A panoramic or intraoral image can contribute to initial assessment. Cone-beam computed tomography may be justified for presurgical implant planning because it can show three-dimensional relationships that a two-dimensional image cannot. The field of view and exposure should be appropriate to the question, and the entire acquired volume must be interpreted by someone competent to do so.
CBCT is not a substitute for periodontal probing, tissue examination, pulp or tooth diagnosis, occlusal assessment or a medical history. It also does not guarantee what will be found surgically or how tissue will respond. A remote DICOM file can be valuable, but quality, date, field of view, artefact and the absence of an examination limit what can be concluded. Repeating imaging merely for marketing or administrative convenience is not justified; the clinician should explain why a new image is needed.
A written radiographic report or documented interpretation should identify the areas relevant to the plan and incidental findings that require action. If specialist radiology input is needed, the referral and report should be retained. Baseline clinical and radiographic records after restoration are also important for future comparison. A patient should be able to obtain copies in a usable format for local aftercare.
Begin with the prosthesis, then work backwards to surgery
Implant planning is prosthesis-led. That means defining the intended teeth, function, contour, emergence, hygiene access and restorative materials before choosing fixture positions. The question is not “Where is there bone?” but “Can a maintainable restoration be supported in an appropriate position, and what surgery would that require?” Placing an implant wherever bone happens to remain can create an angled emergence, an over-contoured crown, inaccessible cleaning space, unfavourable force, speech difficulty or a prosthesis that cannot be repaired predictably.
A diagnostic set-up or virtual prosthetic plan may reveal that the desired tooth position is outside the available ridge. It may show that augmentation is needed, that a different prosthesis is more sensible, or that expectations must change. For a full arch, it should evaluate tooth display, smile line, lip support, vertical space, transition line, opposing dentition, phonetics, occlusion, cantilever and access for hygiene and components. The patient should see and understand major compromises before surgery.
Surgical guides and digital workflows can transfer a plan, but they do not replace diagnosis or professional judgment. A guide has design, support and fit limitations. Mouth opening, tissue movement, manufacturing error and intraoperative findings can alter execution. The consent discussion should explain whether the plan is fully guided, partly guided or freehand, who designed and checked it, and what changes may be necessary if reality differs from the simulation.
Decide first whether the missing tooth or teeth need replacing
Replacement is not compulsory in every gap. A stable, accepted space may be monitored where function, appearance, migration risk, opposing teeth and disease status make that reasonable. This “no immediate replacement” option avoids surgery and restoration but requires a deliberate explanation of likely benefits, limits and review needs. It should not be hidden merely because a clinic sells implants.
Other non-implant categories may include:
- a resin-bonded or conventional tooth-supported bridge, depending on neighbouring teeth, span, bite and restorative need;
- a removable partial denture, which may replace teeth and tissue while remaining repairable and adjustable;
- a complete denture for an edentulous arch;
- an implant-retained removable overdenture where a smaller number of implants and a removable design may address retention while preserving cleanability;
- orthodontic movement or space redistribution where appropriate;
- repair or redesign of an existing prosthesis;
- staged disease control and monitoring before any definitive replacement.
Each has costs and maintenance. A bridge may involve neighbouring teeth; a removable prosthesis may affect comfort, speech, retention and adaptation; no replacement may not meet functional or aesthetic goals. An implant option adds surgery and lifelong implant-specific maintenance. The aim is not to declare one category superior but to match the person’s anatomy, health, goals, dexterity, budget, local access and tolerance for uncertainty.
Map the decision before choosing a reduced-bone technique
A clear decision map can be organised in this order:
- Is urgent disease controlled?
- Can a useful natural tooth be retained?
- Does the missing site require replacement now?
- What prosthetic outcome is acceptable and maintainable?
- What anatomy and soft tissue exist at the proposed positions?
- What medical, periodontal, functional and behavioural risks matter?
- Can a non-implant option meet the goal with less burden?
- If implants remain reasonable, is reconstruction necessary or can a reduced-dimension or altered-position category be considered safely?
- What expertise, facilities and multidisciplinary support does that category require?
- What is the fallback if the planned stability, tissue volume or restorative condition is not achieved?
- Who will provide review, maintenance, urgent care and repair after travel?
- What does the itemised quote include, exclude and leave provisional?
This sequence prevents a catchy technique name from becoming the diagnosis. The following sections describe categories that a responsible team may discuss. They are not recommendations for any reader.
Conventional augmentation is a category, not a guaranteed rebuild
Bone augmentation aims to change the hard-tissue conditions around a planned restoration. The term covers very different procedures: management of an extraction socket, local contour grafting, guided bone regeneration, ridge splitting or expansion in selected anatomy, onlay grafting, vertical augmentation and sinus-floor elevation. Their indications, evidence, donor or biomaterial needs, wound risks and contingency plans differ. A public page cannot select among them.
The clinician should define the proposed defect and purpose. Is the aim to support a fixture, cover a dehiscence, improve contour, move the prosthetic position, support soft tissue or reconstruct a larger segment? Is the proposed gain horizontal, vertical or both? Is the defect contained by bony walls or open? Is there active infection or an extraction site? Will the implant be placed at the same operation or later? What evidence will be used to decide that the reconstructed site is ready for the next stage?
Avoid the promise that grafted bone can “rebuild any site.” Augmentation can be limited by wound stability, blood supply, soft-tissue closure, anatomy, infection, medical factors, smoking or nicotine exposure, patient behaviour and the size or shape of the defect. Complications can include pain, swelling, bleeding, infection, wound opening, membrane or graft exposure, loss or incomplete maturation of grafted material, altered sensation, donor-site morbidity, sinus complications and a need to change or stop the plan. The responsible clinician should explain risks specific to the chosen procedure and the patient.
Socket and ridge management after extraction
When a tooth really must be removed, socket or ridge-preservation measures may be discussed to limit unfavourable contour change or prepare for a later option. They do not freeze anatomy, create a guaranteed future implant site or prove that an implant will be selected. Extraction technique, infection, socket walls, soft tissue, prosthetic goal and material choice affect the decision. The patient should know whether the material is intended to be removed, replaced, incorporated or reassessed, and what happens if healing differs from the plan.
An immediate implant at extraction is a distinct decision. It requires appropriate anatomy, disease management, position and stability; it is not automatically the most tissue-preserving or fastest route. “Immediate placement” describes timing of the fixture relative to extraction, not immediate loading, immediate final teeth or immediate integration. Those terms must not be used interchangeably.
Guided bone regeneration and local contour augmentation
Guided bone regeneration commonly uses a barrier approach with graft material or other space-maintaining measures. The exact material, membrane, fixation and soft-tissue management vary. A small contour correction performed with implant placement is not equivalent to reconstructing a large vertical defect. The quote and consent should name what is proposed, whether the plan is simultaneous or staged, which elements remain contingent, and whether a second procedure may be needed to remove fixation or address exposure.
Ask how the team will manage a wound problem during travel, what instructions apply to a removable provisional over the site and who can see the patient locally. A provisional that compresses a graft can undermine the surgical plan. The restorative and surgical teams should agree on protective design before the procedure, not after discomfort starts.
Staged versus simultaneous augmentation
“Simultaneous” means grafting and implant placement occur at the same operation. “Staged” means reconstruction and implant placement occur at different operations. Neither label establishes suitability or quality. A simultaneous approach depends in part on whether the implant can be placed in the correct prosthetic position with the required intraoperative conditions while the defect is managed. A staged approach may be considered when the reconstruction, disease control, soft tissue, anatomy or uncertainty makes separation more appropriate. Staging adds another decision point but can allow the team to reassess the tissue before committing to fixture placement.
The sequence must remain conditional. A preoperative plan for simultaneous placement may change if the socket, defect, sinus, stability or soft tissue differs from imaging. A staged plan may later be abandoned if healing is insufficient or if the patient chooses another prosthesis. Consent should cover those branches. A quote that lists only the preferred route and hides likely alternatives does not support an informed decision.
Onlay, block and vertical augmentation
Larger or vertical defects may prompt discussion of onlay grafts, blocks, meshes, reinforced membranes or other reconstructive methods. These are advanced categories, not automatic escalators after a routine graft. They can involve fixation, donor tissue, demanding wound closure and a meaningful complication burden. The source site, recipient site, nerve and vessel relationships, soft-tissue envelope, prosthetic necessity and the team’s training all matter.
If the plan includes harvesting the patient’s own tissue, ask exactly where, what morbidity is expected, whether another specialist or facility is involved and what alternatives avoid the donor site. If fixation devices are planned, ask whether and when they may need removal and how their identity will be recorded. If a mesh or membrane becomes exposed, the patient needs written contact and review instructions rather than a promise that this can be handled remotely.
The patient should understand that greater anatomical reconstruction does not automatically produce a better prosthesis. The burden may be disproportionate where a removable alternative, shorter span, modified tooth position or no treatment meets the patient’s priorities.
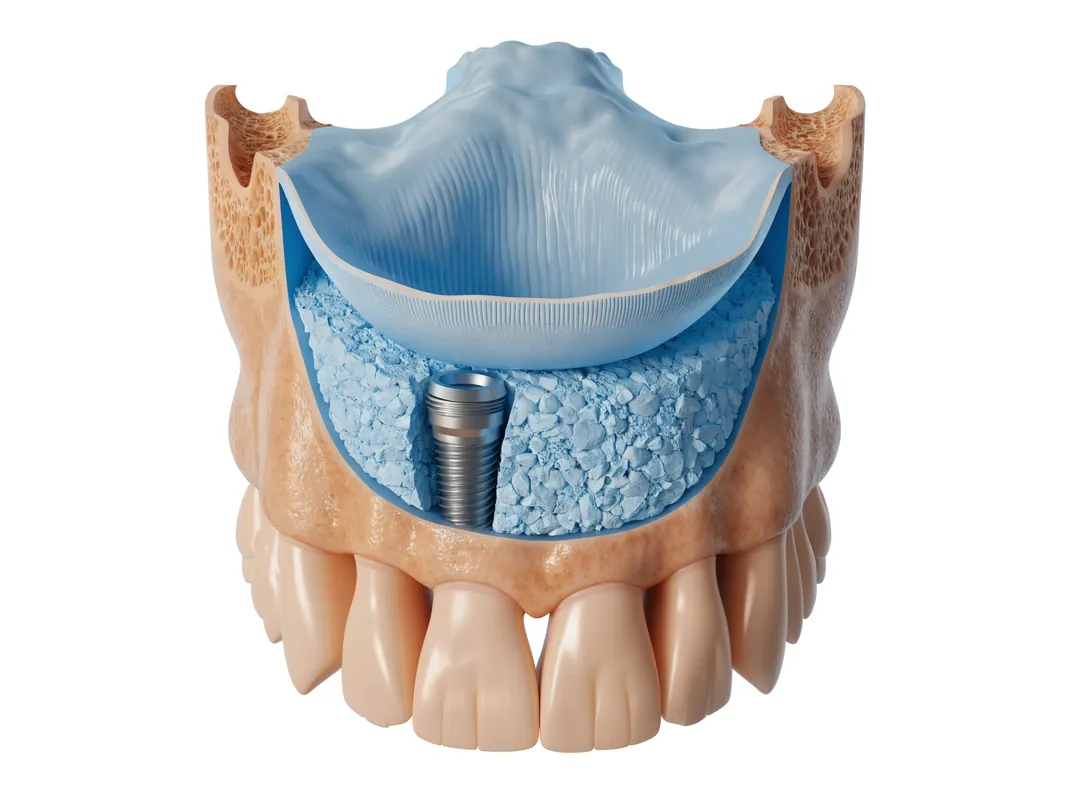
Sinus-floor elevation requires a sinus-specific assessment
Reduced posterior upper-jaw height may lead to discussion of sinus-floor elevation. This is not merely “adding bone under the sinus.” The clinician must assess the prosthetic site, residual ridge, sinus anatomy and health, dental infection, membrane and ostium considerations, medical history and any symptoms or findings that may require dental, radiology or ear-nose-throat input. A panoramic image alone may not answer the necessary three-dimensional questions.
Different access approaches exist, and implant placement may be simultaneous or staged. Public fixed-height rules are unsafe because the decision depends on more than a single measurement. The intended implant position, achievable stability, defect, sinus findings, technique, operator competence and contingency all matter. The plan should explain the chosen approach without claiming that one label guarantees less discomfort, a particular gain or a fixed healing interval.
Potential complications include membrane perforation, bleeding, infection, sinus symptoms, graft migration or loss, wound problems, implant complications and the need for additional care. Patients should receive clear instructions about symptoms that require assessment and what to do if they develop congestion, discharge, fever, worsening unilateral pain, communication between mouth and sinus, or other concerning changes. Flight timing and pressure-related advice must be individualised by the treating team; a generic website rule is not a medical clearance to fly.
Graft material choice needs source, purpose and consent
Graft descriptions such as “your own,” donor-derived, animal-derived or synthetic are broad categories. Products can differ in processing, composition, resorption behaviour, handling and regulatory status. Some procedures use combinations. Membranes, fixation devices and biologic adjuncts introduce additional material questions. No category should be called inherently best on a marketing page.
Before consent, ask for:
- the material category and exact product or device planned where known;
- why it is proposed for this defect and what alternatives exist;
- whether tissue is taken from the patient and from which site;
- whether donor- or animal-derived material is involved;
- relevant allergy, ethical, religious or dietary preferences;
- whether the choice could change during surgery and how consent covers that;
- product, lot or batch and device traceability retained in the clinical record;
- information supplied by the manufacturer where relevant;
- who is responsible for reporting or managing a device concern.
A patient may decline a material category. The clinician can then explain whether another material, another procedure, another prosthesis or no treatment remains reasonable. Preference should be discussed early, not discovered after a non-refundable purchase or on the day of surgery.
Short implants may reduce augmentation in selected sites
Shorter implants are one case-specific category where available anatomy, prosthetic position and evidence may allow discussion of a fixture with reduced length instead of, or alongside, augmentation. Systematic reviews have compared short implants with longer implants placed after augmentation in certain posterior reduced-bone situations. Those comparisons are useful for shared decision-making but do not turn “short implant” into a universal recommendation. Definitions, sites, follow-up, prosthesis designs and study quality vary.
The clinician should consider the exact arch and site, bone dimensions, implant diameter and design, restorative space, crown-to-implant relationship, opposing dentition, force, parafunction, splinting, hygiene, component availability and maintenance. A shorter implant does not eliminate biological or technical complications. It does not solve poor prosthetic position, active disease or an uncleanable design. It may be inappropriate where anatomy, loading or restorative needs do not fit.
Ask whether the alternative being compared is augmentation, a bridge, a removable prosthesis, no immediate replacement or another implant configuration. Ask how the evidence relates to this particular site rather than accepting a generic survival figure. The consent discussion should cover what would happen if the chosen site or stability is inadequate during surgery.
Narrow implants are not simply thinner versions for every ridge
Reduced-diameter implants may be considered for selected narrow spaces or ridges, but diameter affects more than whether a fixture physically fits. The site, tooth being replaced, prosthetic connection, material and design, load, bone dimensions, tissue, component range and evidence all matter. A narrow implant should not be used merely to avoid appropriate reconstruction without checking the restorative and biomechanical consequences.
Systematic review evidence has compared narrow implants with standard-diameter implants used with horizontal augmentation in particular settings. It does not support applying one conclusion to every anterior, posterior, single-tooth or full-arch case. The treating team must state the indication, alternatives and limits. Component traceability is particularly important because future screw, abutment or restoration repair may depend on knowing the exact system and dimensions.
Tilted implants describe position, not a complete full-arch diagnosis
In some full-arch plans, implants may be tilted to engage available anatomy or alter the prosthetic support distribution. This is sometimes presented under a branded numerical concept, but the brand or number does not establish that the patient needs extraction, that grafting is avoided, that immediate loading is safe or that the design will be maintainable. The decision begins with tooth prognosis, jaw relationship, prosthetic set-up, anatomy, implant distribution, restorative materials and hygiene.
Tilt may affect restorative angulation, access channels, component choice, cantilever, force and cleaning. The team should show how the prosthesis is supported and retrievable, where the transition line will sit, how the patient will clean beneath it and how mechanical complications will be managed. An implant placed at an angle is not automatically problematic, but neither is it a generic solution to severe bone loss.
ITI prosthodontic consensus work emphasises considering placement and loading protocols together and within defined clinical conditions. That supports a conditional plan, not a same-day promise. If an implant cannot achieve the required intraoperative conditions, the provisional or loading plan must change. The patient should know that branch before surgery.
Zygomatic implants are a high-complexity specialist category
Zygomatic implants engage the zygomatic region and may be discussed for selected severe maxillary deficiency. They should never be described as a simple bypass, a rescue for everyone told “no bone,” or proof that an upper jaw can always receive a fixed prosthesis. They involve complex three-dimensional anatomy and require appropriate diagnosis, planning, surgical and restorative competence, facilities, complication management and follow-up.
The ITI consensus report on zygomatic implants describes indications and acknowledges anatomical and biological complications. Earlier ITI review work also states that alternatives such as augmentation, short, reduced-diameter or tilted implants may need consideration before a zygomatic route, depending on the case. The important point for a patient is that zygomatic treatment belongs at the end of a careful comparative assessment, not at the top of an advertisement.
Questions should include:
- Why is a zygomatic option being considered for this particular maxilla?
- Which conventional, reduced-dimension, tilted, removable and no-treatment alternatives were assessed?
- Who performs the surgery and who designs and maintains the prosthesis?
- What training, experience and case-specific competence do they have?
- In what clinical setting will surgery and anaesthesia occur?
- What imaging and specialist interpretation support the plan?
- How are sinus, orbital, soft-tissue and prosthetic risks addressed?
- What hospital or specialist pathway exists for a serious complication?
- Who provides urgent assessment after the patient returns home?
- What happens if the intended prosthesis cannot be loaded or delivered?
Potential complications must be discussed in patient-specific terms and may include sinus problems, soft-tissue or hygiene difficulties, infection, altered sensation, oroantral communication, prosthetic complications, failure to achieve the planned support and the need for further intervention. This page does not estimate an individual probability and does not certify any provider or facility. Independent verification and a specialist second opinion are proportionate for such an irreversible plan.

Provider competence and clinical setting are part of the treatment
The procedure name does not reveal whether a team is equipped to deliver it safely. Verify the legal healthcare provider, clinic address, professional registration of each treating clinician, scope of practice, indemnity or insurance arrangements where relevant, anaesthesia team, radiology support, laboratory relationship, emergency equipment and referral pathway. A coordinator, hotel or transport company is not a substitute for the named clinical provider.
GDC Principle 7 requires dental professionals to work effectively with colleagues, refer where appropriate and work within their knowledge, skills and professional competence. For a patient, this means asking who owns each decision: diagnosis, periodontal stabilisation, radiographic interpretation, augmentation, implant placement, sedation or anaesthesia, prosthetic design, laboratory manufacture, maintenance and complication management. “Our team” is not an adequate answer when names and roles are missing.
Complex reconstruction may require periodontal, oral surgery, maxillofacial, restorative, prosthodontic, radiology, anaesthesia or medical input. Multidisciplinary involvement is not a marketing badge. The record should show referral questions, reports, decisions and handover. If part of the care occurs at another facility, the patient should know where, why and under whose responsibility.
Placement, loading, provisional restoration and final restoration are separate events
Marketing often compresses several decisions into “teeth in a day.” Keep them separate:
- implant placement is the surgical insertion of a fixture;
- immediate placement means placement in relation to extraction timing;
- loading means applying a prosthetic load and may be immediate, early or conventional according to the clinician’s protocol and case;
- a provisional restoration is an interim prosthesis used while tissues, appearance, function and cleaning are assessed;
- a final restoration is the definitive prosthesis selected after the required clinical conditions and acceptance checks;
- biological integration is a tissue process assessed over time, not something a same-day photograph can prove.
One event does not guarantee the next. An implant can be placed without being suitable for immediate loading. A provisional may be fixed, removable or deliberately absent. A fixed provisional is not necessarily the final material or design. A final prosthesis should not be delivered merely because flights are booked if disease, tissue, fit, function, phonetics or patient acceptance requires reassessment.
Before surgery, the written plan should specify the intended pathway and the fallback. For example, if primary stability or implant distribution does not meet the pre-agreed loading criteria, will the patient receive a removable provisional, retain an existing denture with modification, leave the site unloaded or enter another pathway? Who decides and how are additional laboratory, clinical and travel costs handled? The patient should consent to realistic branches rather than a single advertising outcome.
Healing cannot be reduced to a universal travel timetable
Tissue response varies with the operation, defect, site, medical context, disease control, wound stability, loading, hygiene and complications. Public fixed healing periods cannot tell an individual when a graft is mature, an implant can be loaded or a final prosthesis can be made. Calendar time is not a substitute for clinical evidence. The treating clinician should define what findings are needed at each decision point and what could delay or change the plan.
Appointments can include wound review, suture care, prosthesis adjustment, clinical testing, imaging where justified, impression or scan, try-in, fitting and maintenance. These do not automatically equal separate international trips, but the quote should not conceal the possibility. A medically safe schedule also allows the patient to recover before flying and preserves time for unexpected review. The relevant clinician, not a sales representative, should advise on flying, driving, work, exercise and dietary restrictions based on the actual procedure and recovery.
Build explicit contingencies into the plan
Severe bone-loss treatment has uncertainty even when carefully planned. A contingency is not evidence of poor care; hiding it is poor communication. The consent and quote should address foreseeable branches such as:
- the extraction site or defect differs from the imaging;
- infection or diseased tissue requires another step;
- the graft cannot be stabilised or the wound cannot be closed as planned;
- the sinus membrane or another anatomical structure is encountered differently from expected;
- the intended implant position or primary stability cannot be achieved;
- fewer implants are placed than planned;
- immediate loading criteria are not met;
- a provisional breaks, rubs, compresses tissue or cannot be tolerated;
- wound opening, exposure, bleeding, altered sensation or sinus symptoms occur;
- the reconstructed tissue is insufficient at reassessment;
- a fixture does not integrate or a later biological or technical complication develops;
- the final restoration needs redesign for speech, hygiene, contour, appearance or force;
- the patient chooses to stop, postpone or change course.
For each material branch, ask who makes the decision, how the patient is informed, whether another consent is required, what alternatives remain and which costs follow. The patient retains the right to withdraw consent before a procedure and to ask the team to stop where it is safe to do so. A signature obtained before travel is not blanket permission for unplanned treatment.
Material, implant, component and laboratory traceability
Long-term maintenance depends on knowing what is in the mouth. The final record should identify the implant manufacturer and system, model or connection, dimensions, site, relevant lot or batch information, surgical components, graft and membrane products where used, fixation devices, abutments, screws and the restoration or framework materials. It should also retain radiographs, photographs, scans, laboratory prescriptions, conformity documentation where applicable and the final occlusal and prosthetic design.
Avoid vague labels such as “premium implant” or “German material.” Country adjectives do not establish identity, evidence, authenticity or future component availability. If alternatives might be used during surgery, the consent should define the reason and record the actual product afterwards. Ask whether compatible components and technical support are reasonably accessible in the country where maintenance will occur.
For a custom-made restoration supplied in Great Britain, relevant MHRA requirements and documentation may apply. Treatment abroad can involve a different regulatory route, but the patient still needs intelligible records sufficient for another dentist or laboratory to understand the device. Do not assume that a local dentist can repair an unknown connection or undocumented framework immediately.
Laboratory responsibility also matters. Ask which laboratory makes the provisional and final prostheses, where manufacture occurs, who checks the prescription, how fit and material are verified, and what happens if the prosthesis needs repair. The clinical provider remains responsible for accepting and fitting a restoration; a laboratory warranty is not a biological guarantee.
Maintenance is not optional after reduced-bone treatment
An implant restoration requires ongoing home care and professional review. Severe initial tissue loss, a large prosthesis, complex contours or reduced dexterity may make maintenance more demanding. The design should be tested for access before finalisation. The patient should be shown the brushes, floss, irrigating aids or removable components needed for that specific prosthesis and demonstrate that they can use them.
Maintenance may include review of symptoms, plaque and inflammation, probing where appropriate, tissue and recession changes, mobility, occlusion, screw or component integrity, wear, fracture, denture attachments and radiographs when clinically justified. The EFP peri-implant guideline supports supportive peri-implant care and prosthetic designs that allow hygiene and professional assessment. A promise of “permanent teeth” is incompatible with the need for maintenance and possible repair.
Before choosing treatment abroad, identify a willing local dental professional for routine and urgent care. Do not assume that every practice services every implant system or accepts responsibility for another provider’s treatment. Share the plan and records early where possible. Ask what the overseas provider expects the local professional to do and whether those expectations are realistic.
Smoking or nicotine use, unstable periodontal disease and poor plaque control can affect risk and maintenance, but they should be discussed without blame. The plan should document support, achievable hygiene and reassessment rather than offering a transaction that ignores modifiable factors.
Consent must compare meaningful options and uncertainty
Valid consent is a continuing conversation. GDC Principle 3 requires relevant options, risks, benefits and costs to be explained in a way the patient can understand, enough time for questions, and recognition that a patient can change their mind. For severe bone loss, that conversation should compare the burden and uncertainty of grafting, non-graft implant categories, removable and fixed alternatives, retention of teeth, no immediate replacement and declining treatment.
Consent should not rely on dramatic before-and-after images. Images may illustrate a provider’s work but cannot predict another patient’s anatomy, healing, appearance or function. If computer simulations are shown, label them as planning aids rather than guarantees. If testimonials are used, they do not replace complication data, professional credentials or the patient’s own diagnosis.
A high-quality consent record should state:
- the diagnosis and limitations of current information;
- which teeth are retained or removed and why;
- the prosthetic objective and expected compromises;
- each reasonable alternative, including no treatment;
- material surgical, medical, anaesthetic, prosthetic and maintenance risks;
- which elements are provisional or conditional;
- the intended sequence and criteria for progression;
- the fallback if grafting, stability, loading or tissue response differs;
- material and tissue-source preferences;
- fees, exclusions and potential additional costs;
- aftercare, emergency and complaint arrangements;
- the patient’s questions, preferences and decision.
Translation must be reliable enough for consent, not merely convenient for sales. The patient should be able to communicate directly with the responsible clinician and receive documents in a language they understand. A friend, driver or salesperson should not be the sole interpreter for complex clinical consent.

A second opinion is especially valuable when treatment is extensive
Seek an independent opinion before irreversible full-arch extraction, advanced vertical augmentation, zygomatic surgery, a proposal that requires several international stages, or a plan that dismisses all removable alternatives. Give the second clinician the actual DICOM imaging, reports, periodontal charting, photographs, diagnostic set-up and proposed prosthesis rather than only a screenshot or sales brochure.
Ask the second clinician to answer a defined question: Are the teeth genuinely non-restorable? Is the prosthesis-led position reasonable? Is the imaging adequate? Are graft and non-graft categories presented fairly? Is the proposed setting appropriate? Is the maintenance design realistic? A disagreement does not automatically prove misconduct. It may expose uncertainty or different reasonable trade-offs that the patient should understand.
Be cautious if a provider discourages independent review, refuses records, claims all alternatives are obsolete, offers an expiring medical discount, or demands payment before naming the treating clinicians and legal provider. Time pressure is particularly inappropriate where the patient is asymptomatic and the procedure is elective.
Remote review can organise records but cannot finalise suitability
A remote consultation may gather the medical history, photographs, previous radiographs, DICOM files, treatment records and goals. It can identify missing information, flag urgent symptoms, explain broad categories and prepare questions. It should label any proposed plan and quote as provisional. It cannot examine tissue, probe pockets, test teeth, assess stability, evaluate the bite fully, confirm imaging interpretation in clinical context or predict surgical findings.
Before sharing health data, identify the recipient, legal provider, privacy notice, secure method, purpose, retention period and who can access it. Ordinary messaging may be convenient but does not remove confidentiality duties. Send original-quality files through an agreed secure route rather than repeatedly forwarding compressed screenshots when diagnostic quality matters.
At the in-person assessment, the clinician should confirm or revise the diagnosis, imaging need, tooth prognosis, prosthetic plan, risks and quote. A substantial change requires explanation and renewed consent. The patient should never feel compelled to accept additional extraction or surgery merely because travel and accommodation have already been paid.
Demand an itemised quote that follows the clinical stages
“Implant package” is too vague for a severe bone-loss plan. Ask for a written, itemised quote from the legal clinical provider. It should separate clinical fees from travel or accommodation and identify:
- consultations, specialist opinions and reports;
- radiographs, CBCT acquisition and interpretation;
- disease control or preparatory care;
- extractions and socket management by site;
- grafting or sinus procedures, donor-site care, materials and fixation;
- implant placement by site and the actual implant system;
- sedation or anaesthesia, facility and monitoring fees where relevant;
- provisional prostheses and adjustments;
- impressions, scans, diagnostic and verification stages;
- abutments, components, framework and final restoration;
- laboratory work and material documentation;
- planned reviews, maintenance and record transfer;
- medicines where lawfully prescribed;
- management of a foreseeable complication or an incomplete stage;
- cancellation, postponement, refund and complaint terms;
- travel, accommodation and transfers as separate non-clinical items if purchased.
The quote should state what is excluded and what cannot be priced until examination or surgery. Ask what happens financially if fewer implants are placed, a graft is abandoned, a provisional cannot be fixed, an additional stage is required, or the patient chooses a removable alternative. “Free remedial treatment” can still leave flights, lodging, time off work and local care unpaid; read the exact contract rather than assuming a warranty covers biology.
Never infer clinical quality from a high or low price alone. Compare like with like: diagnosis, named team, procedures, products, laboratory, records, maintenance and contingency. Currency conversion, card charges and staged payment terms should be transparent. Avoid cash-only pressure or payment to an unrelated individual.
Travel planning follows clinical planning
The GDC and NHS guidance for patients considering dental treatment abroad emphasises checking qualifications and regulation, understanding the treatment and costs, arranging aftercare, knowing complaint routes and considering insurance and travel consequences. These questions are especially important when reconstruction has multiple stages or a complication may require prompt local assessment.
Before booking travel, obtain:
- the name and address of the legal clinical provider;
- the named clinicians and their roles;
- a provisional clinical sequence and the conditions that could change it;
- the minimum clinically required attendance windows, with buffer for review;
- advice on flying and activity from the treating clinician;
- emergency contacts available outside routine hours;
- a local aftercare plan and permission to share records;
- insurance terms, exclusions and medical disclosure requirements;
- accessible accommodation and support if mobility or sedation affects independence;
- a plan for a companion where clinically advisable;
- enough medicine and medical documentation for travel, lawfully carried;
- financial capacity for an unexpected delay or local assessment.
Flights, hotels and transfers are logistics, not evidence of implant suitability and not a clinical outcome. They should be optional and separately described. A transport provider does not take responsibility for diagnosis, surgery or aftercare. Do not let a return flight become the deadline for final fitting. If a clinician recommends staying longer for review, changing the restoration or postponing travel, safety takes priority over itinerary convenience.
After returning home, give the local dental professional the operative notes, product and component record, radiographs, prosthetic design, laboratory documents, medicine list, complications, aftercare instructions and overseas contact route. An English summary can help. Keep your own copy; do not rely on a messaging history that may disappear.
Red flags during sales and consent
Pause and seek independent advice if you encounter:
- a claim that “no bone” can always be solved;
- a final plan made from photographs or one panoramic image;
- extraction of restorable teeth presented as the only route without reasons;
- a technique selected before the prosthesis is planned;
- fixed dimensions, loading or healing promises applied without examination;
- a named implant count used as proof that grafting is unnecessary;
- zygomatic treatment marketed as routine or risk-free;
- no named clinical provider, clinician, facility or registration route;
- consent conducted only by sales staff;
- refusal to provide DICOM data, reports, product records or an itemised quote;
- materials described only by luxury adjectives or country of origin;
- no discussion of removable, bridge or no-treatment alternatives;
- no local maintenance plan or assumption that any dentist can repair the work;
- guaranteed success, lifetime results or “permanent” teeth;
- an expiring discount tied to same-day consent;
- travel arrangements bundled so tightly that the patient feels unable to postpone;
- no written contingency for graft exposure, failed stability, altered sensation, sinus symptoms or prosthetic breakage.
Red flags after surgery
Follow the treating team’s individual instructions. Seek urgent local assessment for difficulty breathing or swallowing, rapidly increasing facial or neck swelling, uncontrolled bleeding, collapse, severe trauma or another emergency. Contact an appropriate dental or medical professional promptly for worsening swelling or pain, fever, pus or foul discharge, persistent vomiting or dehydration, new or persistent altered sensation, wound opening, exposed material or device, significant sinus symptoms, a loose implant or prosthesis, a bite that suddenly changes, or inability to clean or eat as instructed.
The NHS urgent dental guidance explains how to obtain urgent dental help in the UK and identifies emergency situations such as severe swelling affecting breathing and uncontrolled bleeding. Do not wait for an overseas reply when symptoms require local emergency care. Inform the original treating team when safe, preserve records and obtain a written account of local findings and treatment.
A practical reduced-bone consultation checklist
Take this list to the consultation and ask for written answers where the decision is complex:
- What does “no bone” mean at each named site?
- Which teeth can be retained, and which are proposed for extraction?
- What diagnoses are active, and what must be stabilised first?
- What clinical and radiographic records support the diagnosis?
- Why is each image justified, and who interprets the full volume?
- What is the intended prosthesis before surgery is planned?
- Can I see a diagnostic set-up that demonstrates tooth position and cleaning access?
- Is no immediate replacement a reasonable option?
- What bridge or removable alternatives exist?
- If implants are considered, why is augmentation or a non-graft category proposed?
- Is grafting simultaneous or staged, and what would change that decision?
- What graft, membrane, fixation or device materials may be used?
- What are their sources, identities and traceability arrangements?
- What donor-site or sinus risks apply?
- Are short, narrow or tilted implants relevant, and what are their case-specific limits?
- If zygomatic implants are discussed, why are lower-complexity alternatives unsuitable?
- Who performs each stage, and what evidence supports their competence for it?
- What facility, anaesthesia and emergency pathway will be used?
- What must be achieved before loading?
- What provisional will I have if loading is not possible?
- How are placement, loading, provisional and final stages separated?
- What are the main biological, neurological, sinus, mechanical and aesthetic risks?
- What contingency applies if the graft, stability or tissue result is insufficient?
- How will I clean the proposed prosthesis?
- Who provides maintenance and urgent care near my home?
- Which implant, components and laboratory materials will be recorded?
- What exactly is included and excluded from the itemised quote?
- Which costs follow if the plan changes?
- What written records will I receive after each stage?
- Can I take time for an independent second opinion before paying?
How to compare two plans without chasing a promise
Place the plans side by side. Compare the diagnosis, tooth-preservation rationale, intended prosthesis, anatomy, alternatives, number and complexity of operations, anaesthesia, named clinicians, materials, provisional strategy, contingencies, maintenance, local support and total itemised burden. Do not compare only implant count, fixture length, a headline price or a photograph.
A more extensive plan is not automatically more comprehensive, and a less invasive plan is not automatically safer. A short implant may reduce augmentation in one posterior site yet be unsuitable elsewhere. Staged reconstruction may be proportionate for one patient and excessive for another. A removable prosthesis may be a durable, maintainable choice rather than a failure to qualify for surgery. Zygomatic surgery may be considered in a narrowly selected maxillary case but should not be sold as the inevitable next step after conventional implants are declined.
The best-quality decision is one whose assumptions are visible, alternatives are genuine, uncertainty is admitted, responsibilities are named and maintenance can happen where the patient lives. It may end with an implant plan, a non-implant plan, disease control first, a second opinion or no treatment now.
Evidence and further reading
The sources below inform this decision framework. They do not diagnose an individual and should not be turned into universal thresholds or personal outcome estimates.
- American Association of Endodontists, AAE Position Statement – Implants, accessed 29 August 2026: preserving restorable natural teeth, comparing retention with implant replacement, complications and informed consent. https://www.aae.org/specialty/wp-content/uploads/sites/2/2019/04/Implants_PositionStatement_v2.pdf
- American Dental Association and American Academy of Oral and Maxillofacial Radiology, patient selection for dental radiography and cone-beam computed tomography, published 2026 and accessed 29 August 2026: examination-led imaging selection and implant-planning recommendations. https://pubmed.ncbi.nlm.nih.gov/41500761/
- European Federation of Periodontology, S3 clinical practice guideline for prevention and treatment of peri-implant diseases, published 2023 and accessed 29 August 2026: periodontal risk control, cleanable prosthetic design and supportive peri-implant care. https://pubmed.ncbi.nlm.nih.gov/37271498/
- Systematic review of short implants compared with longer implants placed after bone augmentation in atrophic posterior mandibles, accessed 29 August 2026: one evidence base for discussing reduced-length implants as a selected alternative, not a universal recommendation. https://pubmed.ncbi.nlm.nih.gov/34037243/
- Systematic review comparing narrow-diameter implants with standard-diameter implants plus horizontal augmentation, accessed 29 August 2026: selected indications and the limits of generalising diameter choices. https://pubmed.ncbi.nlm.nih.gov/38443497/
- ITI consensus report on zygomatic implants, published 2023 and accessed 29 August 2026: indications, planning, provider expertise and recognised complications in severe maxillary deficiency. https://pubmed.ncbi.nlm.nih.gov/37698775/
- ITI consensus paper on implant placement and loading protocols, accessed 29 August 2026: placement and loading are related but distinct clinician-owned decisions. https://pubmed.ncbi.nlm.nih.gov/30328196/
- General Dental Council Principle 3, Obtain valid consent, accessed 29 August 2026: options, risks, benefits, costs, time for decisions and continuing consent. https://standards.gdc-uk.org/pages/principle3/principle3
- General Dental Council Principle 4, Maintain and protect patients’ information, accessed 29 August 2026: complete clinical records, radiographs, photographs, models, laboratory documents and referrals. https://standards.gdc-uk.org/pages/principle4/principle4
- General Dental Council Principle 7, Work with colleagues in a way that serves patients’ interests, accessed 29 August 2026: competence, collaboration and referral. https://standards.gdc-uk.org/pages/principle7/principle7
- Medicines and Healthcare products Regulatory Agency, custom-made medical devices in Great Britain, updated 20 July 2026 and accessed 29 August 2026: documentation and responsibilities for relevant custom-made devices. https://www.gov.uk/government/publications/custom-made-medical-devices/custom-made-devices-in-great-britain
- General Dental Council, Going abroad for dental treatment, accessed 29 August 2026: provider checks, records, costs, aftercare and complaints. https://www.gdc-uk.org/standards-guidance/information-for-patients-public/going-abroad-for-dental-treatment
- NHS, Treatment abroad checklist, accessed 29 August 2026: informed questions, travel, follow-up, insurance and contingency planning. https://www.nhs.uk/using-the-nhs/healthcare-abroad/going-abroad-for-treatment/treatment-abroad-checklist/
- NHS, How to find an NHS dentist in an emergency, accessed 29 August 2026: urgent dental access and emergency warning signs. https://www.nhs.uk/nhs-services/dentists/how-to-find-an-nhs-dentist-in-an-emergency/
The evidence supports careful diagnosis, tooth preservation, prosthesis-led planning, case-specific comparison and maintainable follow-up. It does not support the promise that every person described as having “no bone” can or should receive implants.