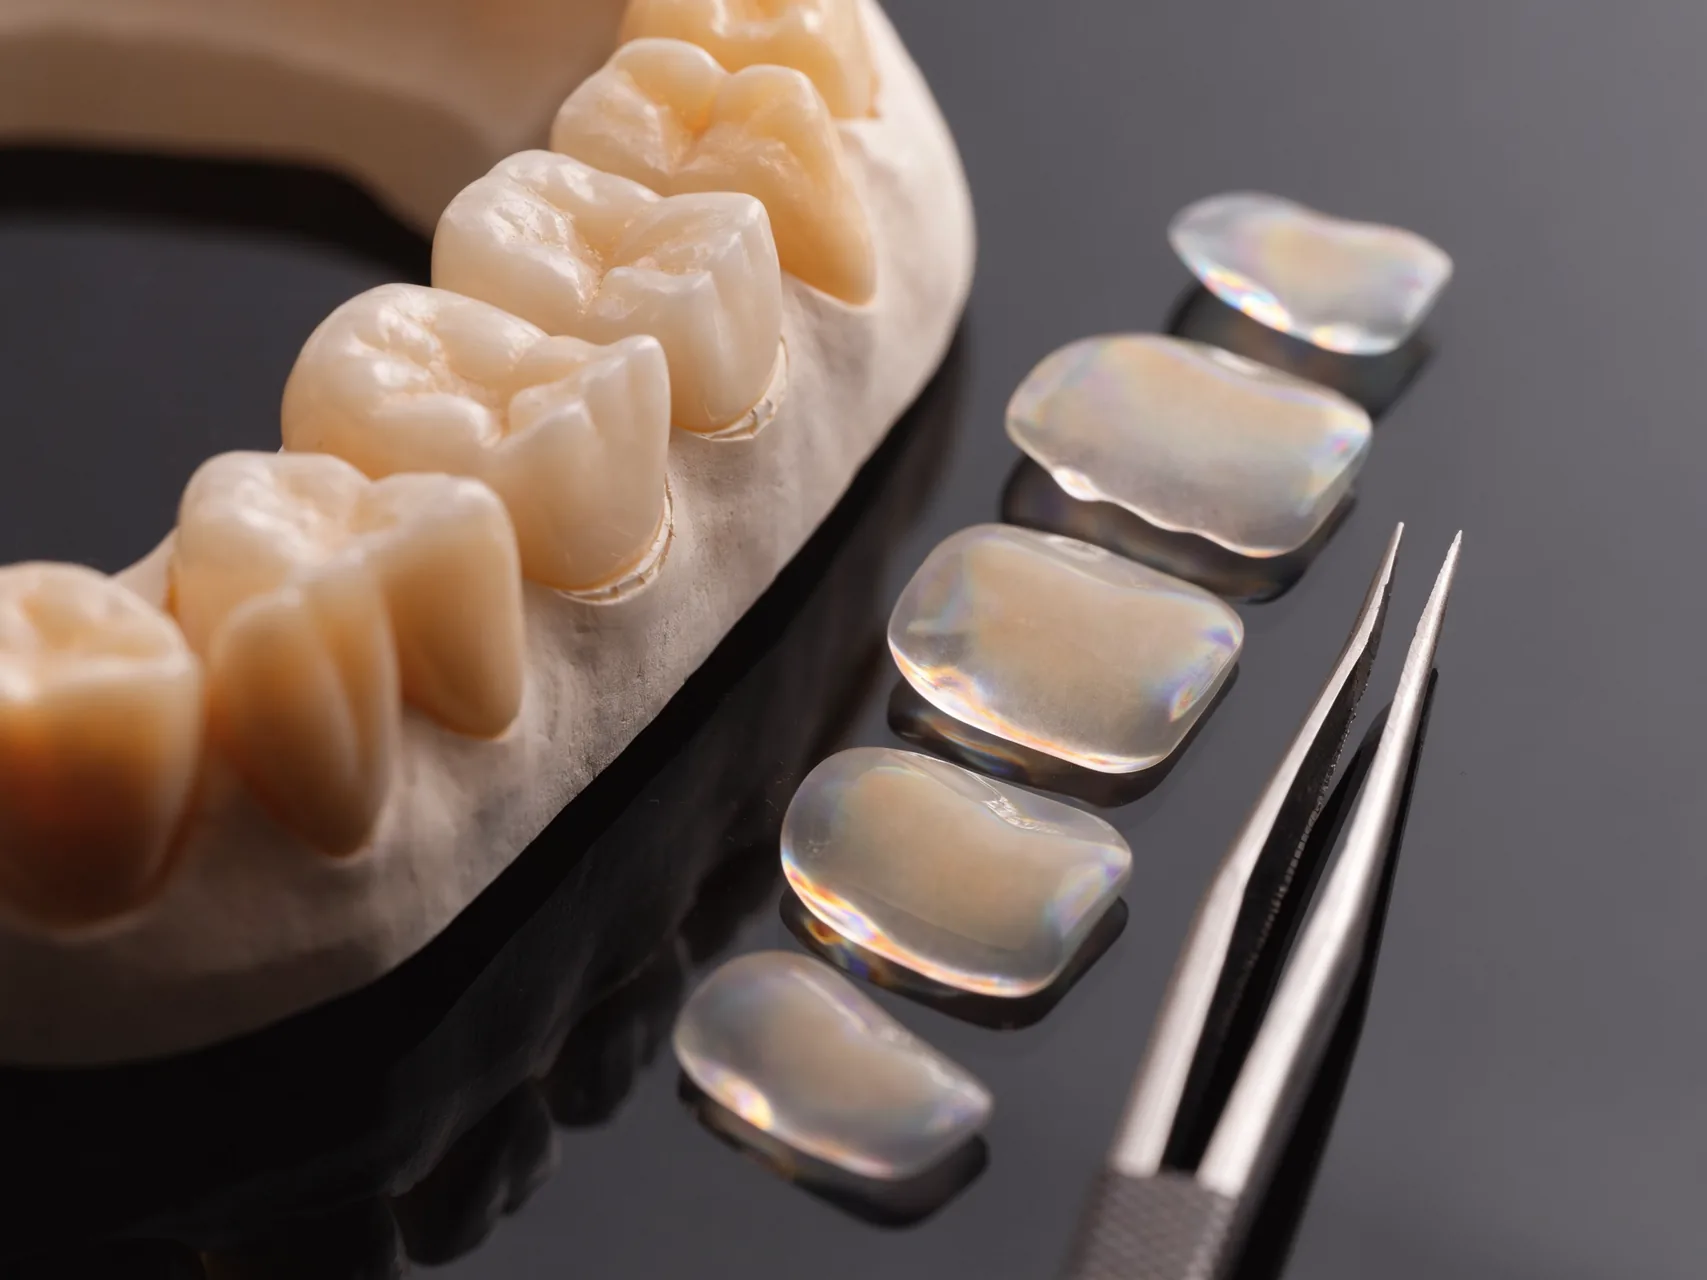
Dental veneers are thin restorations bonded to the front of selected teeth. They can change visible colour, shape, edge form or spacing, but they do not treat every cosmetic concern and they are not a substitute for a full dental diagnosis. The useful question is not simply “Can I have veneers in Turkey?” It is whether veneers are suitable for each tooth, how much healthy tooth would be altered, which alternatives preserve more structure, and how the result and aftercare will be managed once you return home.
The [NHS dental treatment overview](https://www.nhs.uk/live-well/healthy-teeth-and-gums/dental-treatments/) describes veneers as facings for selected teeth and notes that preparation varies. The [ADA MouthHealthy veneer guide](https://www.mouthhealthy.org/all-topics-a-z/veneers) explains that porcelain and composite pathways differ, that teeth must be assessed and that some veneer treatment is irreversible. The [GDC consent standard](https://standards.gdc-uk.org/pages/principle3/principle3) and [patient-record standard](https://standards.gdc-uk.org/pages/principle4/principle4) provide useful questions for UK patients; they do not certify a Turkish provider or prescribe a veneer.
This guide does not select a material, brand, tooth count, preparation depth, shade, bonding system, laboratory, appointment count, lifespan, price or travel schedule. It is a decision framework for comparing dental veneers in Antalya without turning a simulation or package into a clinical promise.
Define the concern before choosing veneers
Write the concern in plain language: colour, chip, surface texture, edge length, gap, proportion, crowding, rotation, wear, asymmetry or an existing restoration. Then identify whether it affects one tooth, several teeth or the whole visible smile and whether it changes through speech and movement.
Different concerns can look similar in photographs. A dark tooth may have pulpal or restorative causes. A short edge may be wear, fracture, tooth position or gum display. A gap can be related to tooth size, alignment, missing teeth, gum attachment or bite. Diagnosis determines whether a facing is sensible.
Ask what remains acceptable without treatment. A natural variation is not a disease, and cosmetic preference should not be converted into a need for irreversible work. The plan should preserve the option to choose less treatment or no treatment after seeing the evidence.
Compare a tooth-preservation ladder
Start with oral-health treatment and no elective change. Then compare cleaning, stain removal, whitening where suitable, small additive repair, edge reshaping, composite bonding, orthodontic movement, a veneer and a crown only when each is clinically relevant. The order is not automatic; it shows how much tissue and future maintenance each step may involve.
Whitening changes natural tooth colour but not existing crowns, veneers or fillings. Orthodontics moves teeth rather than disguising position. Composite may allow additive repair and direct maintenance. A veneer covers the visible surface. A crown wraps much more of a tooth and should not be a routine cosmetic substitute on a healthy tooth.
Request a tooth-by-tooth reason for rejecting a more conservative alternative. A uniform package count is not an explanation, especially when some visible teeth may need no restoration or a different treatment.
Veneers, crowns and bonding are not synonyms
Marketing sometimes calls crowns full veneers or uses laminate for several unrelated procedures. Ask which surfaces are covered and how much tooth is prepared. A veneer generally covers the facial surface and may wrap selected edges; a crown covers the tooth circumferentially. Composite bonding may be applied directly without a laboratory shell.
The clinical record and quote should use the actual procedure for each tooth. Mislabelled crowns change tissue removal, pulp risk, margins, laboratory work, maintenance and future replacement. Ask to see the preparation design in a tooth diagram or model, not only the final front view.
If a tooth already has a large restoration or crown, replacing it is a different decision from placing a veneer on intact enamel. The plan should not force every tooth into one marketing category.
Treatment must stay under a licensed dentist
The ADA veneer guide warns about services offered without licensed dental diagnosis. Veneer placement changes teeth and bite and can conceal disease; it is not a beauty-salon procedure. Verify the legal facility, named examining and treating dentist, current professional registration and each person's role.
A technician can manufacture a restoration from a prescription but should not diagnose, prepare teeth, bond veneers or obtain clinical consent. A coordinator can arrange appointments and quotations but should not decide candidacy, material or preparation.
If the clinician, facility or laboratory changes after payment, request an updated plan, quote and consent. A social-media title, certificate or before-and-after gallery does not establish recognised specialist status or current registration.
Who May Be Suitable for Veneers?
Veneers may be considered when a licensed dentist finds that teeth and gums are healthy enough and the concern is mainly on the visible front surface. Examples include a chipped edge, a shape or size difference, a gap, a colour concern that does not respond as hoped to whitening, or limited wear. Suitability depends on the bite, enamel available for bonding, existing fillings, gum position, tooth vitality, oral hygiene, expectations and any history of clenching or grinding.
Active decay, untreated gum disease, unstable bite problems or unexplained pain should be assessed before elective veneer treatment. Significant crowding may be better addressed with orthodontics. A heavily filled, cracked or root-treated tooth may need a different restoration. A clinician should explain why each proposed tooth needs treatment rather than applying one design to every visible tooth.
Oral health is the first eligibility gate
Active decay, gum inflammation, untreated periodontal disease, unexplained pain, infection and defective restorations need diagnosis before elective veneers. Covering a discoloured or damaged tooth does not remove disease beneath it. Ask for the examination findings and any stabilisation that must be completed first.
The provider should assess plaque control and whether margins can be kept clean. Swollen gums can distort scans, preparation boundaries and shade decisions. Tissue appearance may change after inflammation is controlled, altering the proposed tooth length or margin.
If a remote quote already fixes the number of veneers, ask which examination finding could reduce or increase that number. A safe plan can change after direct assessment.
Enamel, dentine and existing restorations affect bonding
Bonding conditions differ between enamel, dentine, old composite, ceramic, metal and other substrates. The amount and distribution of enamel remaining can influence the preparation, material, adhesive strategy and repair options. A photograph cannot map those surfaces reliably.
Ask for a tooth-by-tooth substrate record after examination and preparation. If a large area may expose dentine, the consent discussion should explain sensitivity, bonding uncertainty and whether another restoration design is more suitable.
An existing facial filling can change colour and support. Removing it may reveal decay or reduce remaining tissue. Keeping it may create a mixed bonding surface. The final plan should record the decision rather than treating every front tooth as untouched enamel.
Tooth vitality, cracks and previous root treatment matter
A dark or heavily restored tooth may need pulp and crack assessment before cosmetic coverage. Veneers do not treat pulpal disease, vertical fracture or an unstable restoration. A root-treated tooth may have different structural and colour considerations and could require another restorative design.
Ask about symptoms, trauma, previous root canal treatment, large fillings and colour change. Clinical tests and imaging should be justified by diagnosis; a routine cosmetic package is not a reason for unnecessary radiation.
If a tooth develops symptoms during planning or provisionals, pause and reassess. Do not bond a definitive veneer merely to preserve the travel schedule.
Bite, grinding and jaw symptoms change suitability
Deep bite, edge-to-edge contacts, tooth wear, clenching, grinding, missing back teeth and unstable contacts can increase load on veneer edges or alter the aesthetic plan. A front-view photograph does not show functional movement.
Ask how the clinician records the bite, checks jaw movements and distinguishes desired length from a contact interference. A guard may be considered in selected cases but cannot compensate for an unsuitable preparation or restoration design.
Existing jaw pain or muscle symptoms need their own assessment. Veneers should not be sold as a treatment for temporomandibular disorders without a separate diagnosis and evidence-based plan.
Gum line and margin planning are biological decisions
Software can redraw a gum line immediately, but real tissue has inflammation, attachment, thickness, recession risk and healing behaviour. Ask whether apparent asymmetry comes from disease, tooth position, natural variation, restoration contour or another cause.
The margin position influences appearance, bonding isolation, cleaning, gum response and future repair. A deep margin may be harder to keep dry and maintain. The clinician should explain why each margin is placed and how it will be examined and cleaned.
If gum contouring or grafting is proposed, treat it as a separate procedure with diagnosis, named clinician, risks, alternatives, healing review and an updated design after tissue change.
Alternatives Worth Comparing First
A conservative plan starts with the least invasive option that can meet the clinical goal. Depending on the diagnosis, alternatives can include professional cleaning, whitening, orthodontic alignment, edge reshaping, composite bonding, replacing a defective filling, or accepting a harmless variation. A crown covers much more of a tooth and should not be presented as a routine cosmetic substitute for a veneer on an otherwise healthy tooth.
Ask for the benefit, limitation and maintenance burden of every realistic alternative. Composite can often be repaired directly but may require more maintenance. Porcelain may offer different optical and wear characteristics but normally involves laboratory work and may require enamel removal. Orthodontics takes a different route: it moves teeth rather than masking their position. The right choice depends on the tooth, bite and priorities, not on a package name.
Whitening must be sequenced before irreversible shade work
Professional whitening may be considered when the main concern is colour and the patient is suitable. Natural teeth can lighten while existing restorations do not, so sequencing matters. If whitening occurs after veneers are made, untreated teeth may no longer match.
Ask which teeth are natural, restored, root-treated or intrinsically discoloured. Agree whether whitening will occur, when shade stabilisation is reassessed and which restorations might later need replacement. A screen simulation cannot predict the response of natural tooth structure.
Use the professional whitening guide to separate product verification, sensitivity and restoration-colour questions. Whitening should not be bundled automatically with veneers when it does not serve the patient's objective.

Orthodontics changes position rather than hiding it
Crowding, rotation, protrusion and gaps can sometimes be treated by moving teeth. Veneers may visually mask position but can require greater reduction or create wide, overcontoured shapes when alignment is ignored.
Ask whether an orthodontic opinion would reduce the number of restored teeth, preserve enamel or improve bite and cleaning. Treatment time and retention are real trade-offs, but speed alone is not a clinical reason to remove more tooth tissue.
Combined plans need a new scan, bite and margin assessment after tooth movement. A veneer design made before orthodontics is not automatically valid afterwards.
Composite bonding deserves a true comparison
Direct composite can add or reshape selected areas and may be easier to repair without laboratory work. It can stain, wear, chip or need polishing and replacement. Suitability depends on size, substrate, bite, colour requirement and maintenance expectations.
Compare additive composite, indirect composite and ceramic veneers rather than using composite as a vague budget option. Ask how much tooth is altered, how shade and texture are controlled, what repair looks like and which maintenance can be provided near home.
A trial additive repair may provide useful information before a broader irreversible plan. It is still treatment requiring diagnosis, isolation, material documentation and consent.
Tooth Reduction Is an Irreversible Trade-Off
Some veneer preparations remove enamel so the restoration can sit without looking bulky and the margin can be placed appropriately. The amount of tooth reduction is case-specific; it cannot be promised from photographs alone. A claim that preparation will be unnecessary should not be treated as a clinical commitment because position, contour, colour and bite may make reduction necessary. Once healthy tooth structure has been removed, it does not grow back, and the tooth will usually need ongoing restorative care.
Before consent, ask the treating dentist to mark which teeth are proposed, why each is included, what reduction is expected, whether any area may reach dentine, and what happens if the examination changes the plan. Discuss possible sensitivity, chipping, debonding, gum changes, bite adjustment, decay around margins and the future need to repair or replace a restoration. Anaesthesia and comfort measures should be agreed for the individual; discomfort and recovery cannot be predicted with certainty.
No-prep is a finding, not a product promise
An additive or minimal-preparation veneer may be possible when tooth position, colour, space, contour, bite and material permit it. Adding thickness to a prominent, crowded or dark tooth can create bulk, opaque material or difficult margins. Photographs alone cannot establish no-prep suitability.
Ask the provider to distinguish truly additive areas from enamel finishing, contact opening, edge reduction and any removal of old restorations. Even a small irreversible change should appear in the consent record.
Do not pay extra for a no-prep label before examination. The clinical objective is appropriate tissue preservation and maintainable contour, not loyalty to a marketing category.
Map additions and reductions tooth by tooth
A useful design shows where material will be added and where tooth tissue may be reduced on facial, edge and side surfaces. Front-view images can hide contact opening, wrap, margin depth and reduction of protruding areas.
Ask for the proposed preparation to be explained on a model, scan or diagram. Record the baseline tooth, approved design, preparation guide where used and final preparation so that changes can be compared.
If the actual reduction exceeds the discussed plan, pause before impression or scan and renew consent. The patient should understand whether a more extensive veneer, crown, alternative restoration or no continuation is now proposed.
Sensitivity and pulp risk need honest boundaries
Preparation, dehydration, bonding, bite changes and underlying tooth condition can contribute to sensitivity. Symptoms can be temporary or require further diagnosis. No provider can promise that every tooth will remain comfortable or avoid later pulp treatment.
Ask how baseline sensitivity and vitality are recorded, how the preparation protects tooth structure and what symptoms require review. A deep preparation, crack or existing large restoration may change the risk discussion.
If root canal treatment becomes necessary, obtain a diagnosis rather than accepting it as a normal package add-on. The tooth's restorability and final restoration design must be reassessed.
Porcelain, Composite, Shade and Material Verification
“Porcelain veneer” describes a category, not one identical product. Ceramic systems differ in composition and fabrication, while composite veneers use tooth-coloured resin placed directly or indirectly. A material that suits one tooth may not suit another. The clinician and dental technician should consider remaining enamel, required opacity, available space, bite load, opposing teeth, repair strategy and the desired level of translucency.
Brands such as IPS e.max from Ivoclar may be discussed as options, but a brand name on a webpage does not prove that it is stocked, selected or appropriate for your case. Ask the provider to verify the exact material, manufacturer and traceability details in the final written quote before you pay or travel. The same rule applies to bonding products and temporary materials.
Shade planning should happen in a controlled way. Existing crowns and fillings will not change colour through whitening, and very bright shades can affect the plan for untreated teeth. Ask how shade will be recorded, whether photographs or a physical shade guide will be used, how the restoration will be assessed in different light, and at what point changes are still possible. A digital image or mock-up can support discussion, but it is a planning aid rather than a promise of the clinical result.
Material category is only the beginning
Ceramic, porcelain, glass-ceramic and composite are broad terms. Exact composition, translucency, opacity, thickness, surface treatment, firing or processing and bonding instructions affect the workflow. A famous product family on a website is not proof that the actual case uses it.
Request the proposed manufacturer and exact material after assessment, and obtain the final case-specific label, invoice or laboratory traceability evidence. If the material changes, ask why, how optical and mechanical properties differ, and whether preparation or bonding must change.
The material should fit substrate colour, remaining enamel, available space, bite, opposing teeth, repair strategy and desired appearance. One material cannot be declared best for every veneer.
Laboratory ownership and prescription must be visible
Ask for the laboratory's legal identity and who communicates with the technician. The prescription should identify the patient and teeth, design version, material, substrate, shade, margin, contacts, bite, surface character and any special instructions.
A technician may flag manufacturability or aesthetic limits, but the dentist remains responsible for clinical decisions and consent. If the laboratory changes the design or material, the clinician should review the effect and discuss material changes with the patient before delivery.
After treatment, request the relevant laboratory prescription and conformity or traceability record available for the supplied restoration. A claim that a laboratory operates at the treatment address, or a technician portrait, is not a case record.
Shade selection needs controlled evidence
Tooth colour varies with hydration, light, surrounding colours, camera settings and display calibration. A shade chosen from a filtered photograph or immediately after dehydration can mislead. Natural teeth, fillings, crowns and veneer substrates should be mapped separately.
Ask when and under what conditions shade is recorded, whether the laboratory receives calibrated photographs and substrate information, and how the patient reviews character, translucency and surface texture. Brightness is a preference, not a clinical quality score.
If the requested shade requires heavy opacity or thickness, discuss the effect on preparation, natural appearance and future matching. The patient should be free to choose a less uniform result.
Digital smile design is a planning aid
A two-dimensional preview can explore outline and colour direction but cannot fully represent thickness, bite, speech, gum response, texture or changing light. A three-dimensional wax-up adds geometry but still depends on records and assumptions.
Use the digital smile planning guide to separate source photographs, scans, design versions, mock-up and definitive restoration. The preview must be labelled as illustrative and subject to examination, function, material limits and renewed consent.
Do not approve irreversible preparation solely because a dramatic simulation looks attractive. Ask what part of the image can actually be tested before treatment.
A mock-up should answer named questions
An additive trial smile may help assess visible length, proportion, speech, lip support and general contour. It can feel thicker than a definitive veneer and may not reproduce material colour or fine surface. It should not be presented as proof of the final outcome.
Ask whether the mock-up alters tooth structure, how it is removed, which design version it represents and what feedback is recorded. View it at conversational distance, during speech and in ordinary expressions rather than only under a ring light.
If concerns arise, change the design before preparation where possible. Record which features were accepted and which remain uncertain.
Provisionals are another clinical gate
Prepared teeth may need temporary veneers while laboratory work is completed. Provisionals can protect teeth and test broad appearance, speech, contours and bite, but their material and fit differ from definitive veneers.
Obtain instructions for eating, cleaning and what to do if one loosens, fractures or feels high. A provisional should not remain indefinitely without review. Gum inflammation or discomfort during this stage may change the final design.
Use the provisional to record patient and clinician observations. Do not silently transfer an uncomfortable contour into the definitive restorations merely to meet a departure date.

Try-in is not the same as final bonding
Before definitive bonding, the clinician should check tooth identity, fit, margin, contacts, contour, shade direction, symmetry, speech and bite within the limits of the try-in. Some try-in media and lighting can alter apparent colour.
Ask which changes are still possible before bonding and which require laboratory remake. The patient needs enough time to inspect and ask questions without pressure from a flight or payment milestone.
Once bonded, removal may damage the veneer or tooth and can require a replacement restoration. Renew consent before this irreversible step, especially when the appearance or material differs from the approved plan.
Bonding needs isolation and exact instructions
Bonding depends on clean, controlled surfaces and the correct sequence for the tooth substrate and veneer material. Moisture, contamination, mixed substrates, incompatible products or incorrect surface treatment can affect retention. A brand name alone does not prove the protocol was followed.
Ask how isolation is achieved and how the clinician handles enamel, dentine, existing restoration and veneer surface under the applicable manufacturer instructions. The patient does not need a recipe, but the record should identify the actual materials used.
After placement, remove excess material, check margins, contacts and bite, and document any adjustment and final polishing. Bonding day is not the end of review.
What a Written Treatment Plan and Quote Should State
Do not rely on a social-media message or a total price without scope. A useful written treatment plan should identify the named provider, responsible treating dentist, diagnosis, teeth under consideration, alternatives, expected tooth reduction, material category, proposed shade process, provisional-restoration plan, clinical stages and important risks. It should make clear which decisions remain subject to an in-person examination.
The written quote should list treatment fees by item and state what is included and excluded. Ask separately about examinations, imaging, temporary restorations, laboratory remakes, bite guards, medication, translation, transport and accommodation. If any warranty or remedial policy is offered, obtain the provider or manufacturer terms in writing, including the covered item, duration, maintenance conditions, exclusions, evidence required and who pays travel or further treatment. General website wording is not a substitute for those terms.
Compare quotes by tooth and clinical stage
The quote should identify every tooth and whether the item is assessment, whitening, bonding, veneer, crown, replacement of existing work, gum procedure, provisional, laboratory work, try-in, bonding or review. One smile makeover total can hide a different procedure count or material.
Separate confirmed scope from findings that may change after examination or removal of old work. State the currency, payment stages, taxes where applicable, cancellation and refund rules, laboratory remake terms and cost if the patient stops after preparation.
Do not compare totals until materials, preparation, laboratory, provisionals, reviews and aftercare are normalised. A cheap veneer that excludes diagnostics, temporaries or remakes is not the same service.
Warranty language needs an actual remedy
A written policy should name the issuer, covered restoration, start date, duration, exclusions, maintenance requirements, evidence and remedy. Chipping, debonding, colour preference, gum change, decay, trauma, grinding and pulp treatment may be treated differently.
Ask who decides whether the policy applies, whether repair or replacement is offered, and who pays clinical time, laboratory, local care and travel. A material manufacturer's product term is separate from a clinic's labour or outcome policy.
No lifetime phrase can predict biological or restorative performance. Keep the policy with the itemised invoice and clinical record; marketing screenshots can change.
Consent occurs at several irreversible gates
Separate consent for records, simulation, mock-up, preparation, provisional, definitive material, bonding and marketing photographs. Approval of a preview is not consent to remove tooth structure, and preparation consent is not automatic approval of a different final shade or material.
Renew consent when examination changes tooth count, procedure, reduction, material, gum plan, laboratory, cost or expected maintenance. The patient should be able to pause before preparation and before bonding.
Agree what happens if a tooth proves unsuitable after old work is removed or if the patient dislikes a provisional. State temporary protection, alternative restoration, additional fee and record release before starting.
Clinical photographs are not marketing permission
Photographs, scans and videos can be clinical records and health information. Ask the legal data controller, purpose, recipients, international transfers, retention, security and access route before sending files.
Permission to use images in advertising or social media must be separate from clinical care. Refusal should not affect diagnosis or the agreed treatment price. If publication is permitted, record which images, platforms and editing are approved and how future withdrawal works.
Do not send identifiable clinical images to a public image-generation or messaging service without an appropriate, explained pathway. Keep original clinical records distinct from edited simulations.
Treatment Stages the Provider Must Confirm
A common pathway can include remote record review, an in-person examination, diagnostic records, planning, tooth preparation where indicated, impressions or scans, provisional restorations, laboratory fabrication, try-in, bonding and a bite review. Not every case follows all of these stages, and the order can change if decay, gum inflammation, a bite concern or another diagnosis is found.
Ask the provider to confirm the schedule in writing after reviewing the information needed for your case. The plan should allow time for clinical checks, laboratory work, requested changes and a post-fitting review. Do not assume that a fixed number of days is sufficient, and do not book a departure that leaves no margin for an adjustment. Remote screening can help organise a visit but cannot replace the examination on which final consent and treatment depend.
Clinical readiness controls the schedule
Gum inflammation, decay, pulpal symptoms, whitening, orthodontics, tissue healing, laboratory remake or an unsatisfactory provisional can change the sequence. A package duration cannot make a tooth ready for preparation or a veneer ready for bonding.
Ask what findings are required at each gate and which finding causes delay, redesign or stopping. Keep travel changeable enough to allow responsible review without forcing a rushed decision.
If only one visit is available, compare what can be assessed safely with what should wait. A planning consultation may be more valuable than irreversible treatment under a compressed timetable.
Material or laboratory substitution needs renewed agreement
If the quoted ceramic, composite, laboratory or technician changes, ask for the new exact identity, reason, evidence, optical and maintenance differences, price and effect on preparation or bonding. Similar-looking categories are not automatically equivalent.
Do not allow a substitute because the original material is out of stock after teeth have already been prepared without a clear contingency. The plan should identify alternative protection and the right to delay or decline.
Update the prescription, consent, invoice and final traceability record. The case file must match what was actually bonded.
Accessibility and translation affect valid consent
Request information in a usable language and format, enough time for questions, appropriate interpretation and physical access for mobility or sensory needs. A support person can help, but the clinician must still address the patient and preserve confidentiality.
Automated translation can miss the difference between veneer and crown, enamel and dentine, temporary and definitive, or repair and replacement. Have the named clinician confirm the clinical meaning.
Digital previews should have a non-digital explanation for someone who cannot use a portal or three-dimensional viewer. Accessibility is part of understanding, not a decorative website feature.
Planning Dental Travel to Antalya
Before booking non-refundable travel, confirm the legal treatment provider, the named clinician, professional registration, treatment address, emergency contact and expected appointment schedule. Share an accurate medical and dental history, current medicines, allergies, relevant radiographs and details of previous restorations. Ask whether new imaging may be required and how it will be justified.
Budget separately for flights, accommodation, local transport, meals, travel insurance, an extended stay and a possible return visit. Confirm in writing whether any travel service is actually included; do not infer it from the word “package.” Tell your insurer about planned dental treatment and check exclusions. Arrange enough time after fitting for the provider to review comfort, margins and bite before you leave.

Keep clinical and travel contracts separate
The clinic, facilitator, hotel and transport company may be different legal entities. Identify who supplies each service, who takes payment, what cancellation terms apply and who handles a complaint. Travel convenience does not transfer clinical responsibility to a coordinator.
Treatment consent should not require accepting accommodation or transport. If travel changes, access to clinical records, aftercare and the right to stop should remain intact.
Use the dental treatment timeline guide to map examination, preparation, provisionals, laboratory, try-in, bonding and review without assigning a universal duration.
Arrange the home-care route before preparation
Ask a dentist near home whether they are willing to examine, maintain or repair overseas veneers. They may need a new assessment and are not automatically responsible for another provider's work.
Provide tooth-by-tooth records, material and bonding information, laboratory details, baseline images and the final bite and margin record. Agree how the overseas dentist answers clinical questions and transfers files.
The returning home after dental tourism guide provides a broader handover checklist. Do not wait for a fracture or pain episode to discover that the only record is a filtered photograph.
Aftercare at Home
Veneers still require care of the tooth and gum around them. Follow the treating clinician’s instructions, brush with fluoride toothpaste, clean between the teeth and maintain examinations with a dentist at home. Avoid using veneered teeth to open packaging or bite hard objects. If grinding or contact sport is relevant, ask whether a suitable guard is indicated rather than assuming one is included.
Contact a dentist promptly for persistent pain, swelling, a loose or fractured veneer, a bite that feels high, gum inflammation or a new sharp edge. Before treatment, agree who will assess a concern after you travel, how records will be shared, whether remote review is appropriate, and what requires an in-person visit. Your local dentist is not automatically responsible for work performed abroad, so make an aftercare route before treatment begins.
Veneers can chip, crack, loosen or wear
Material, thickness, bonding substrate, bite, trauma, habits and maintenance affect mechanical complications. A small chip may be polished or repaired in selected cases; another defect may require replacement. Diagnosis comes before choosing a remedy.
If a veneer loosens, keep it safely and avoid rebonding it with household or cosmetic adhesive. A dentist needs to inspect the tooth, restoration, contamination, fit and cause. Repeated debonding calls for assessment of preparation, bite and material rather than endless rebonding.
Update the clinical and material record after repair or replacement. A different material or design should trigger a new consent discussion.
Margins, gums and decay still need monitoring
Veneers do not make teeth immune to decay. Plaque can accumulate around margins, and gum inflammation, recession or contour change can expose edges or alter appearance. Home cleaning and professional review remain necessary.
Ask the clinician to demonstrate brushing and interdental access around the actual restorations. A contact that cannot be cleaned or an overcontoured margin needs review rather than acceptance as cosmetic fullness.
Persistent bleeding, swelling, bad taste, sensitivity or a visible margin change should be assessed. Polishing or cleaning alone may not correct decay, a defective margin or biological-width problem.
A high or changed bite needs prompt review
Veneers can alter edge contacts and guidance. A restoration that contacts prematurely may feel high, affect chewing or increase load on the veneer and opposing tooth. The patient should have a route for adjustment before departure and near home.
Do not self-grind or file a veneer. A clinician should identify the contact in closure and movement, assess symptoms and polish adjusted material appropriately.
Jaw or muscle discomfort can have several causes. A veneer adjustment should follow examination rather than assuming every symptom comes from one visible tooth.
Repair, replacement and future escalation are distinct
Composite may be added to selected defects; ceramic repair has different limitations. A full replacement removes the existing veneer and may remove more tooth tissue. Repeated replacement can reduce remaining enamel and eventually change the appropriate restoration.
Ask how the proposed design can be removed, repaired or replaced and what happens if the underlying tooth fractures, decays or needs root canal treatment. A veneer is not a one-time lifetime intervention.
Future crowns should not be described as inevitable, but the patient should understand that a more extensive restoration may become necessary if tissue, bonding or structural conditions change.
Urgent symptoms are not an online aftercare issue
Severe or increasing pain, facial swelling, fever, trauma, uncontrolled bleeding, difficulty swallowing or breathing, or a serious medicine reaction needs prompt local clinical advice. A remote photograph cannot rule out infection or pulpal disease.
A loose veneer without severe symptoms still needs timely protection because the prepared tooth may be sensitive or vulnerable. Ask what temporary care is appropriate; do not place unapproved material on the tooth.
Keep the provider informed, but do not delay accessible urgent care while waiting for an international reply or remedial decision.
Records to Take Home
Request copies of the final treatment plan, signed consent, itemised invoice and receipt, pre- and post-treatment photographs or radiographs used in care, the tooth-by-tooth treatment record, material and shade details, laboratory prescription where available, medication record, aftercare instructions and emergency contact information. Keep any written remedial terms with these records. They help another dentist understand what was done if you need maintenance later.
You can send existing dental records and clear photographs to request an initial review. Treat any remote response as provisional. Ask for alternatives, uncertainties, the responsible clinician, a written plan and a written quote before committing to irreversible treatment or travel.
Records should show what actually happened
Keep the original concern and diagnosis, medical history, examination, vitality and bite findings, authorised photographs and scans, design versions, mock-up feedback, tooth-by-tooth preparation, provisional record and changes to the plan.
After bonding, retain material manufacturer and exact product where available, shade, substrate, bonding materials, laboratory identity and prescription, invoice, contacts and bite adjustments, aftercare, review and remedial policy. If crowns were supplied instead of veneers, the record must say crowns.
The GDC patient-record standard lists photographs, models, consent, laboratory prescriptions and conformity information among records where available. That UK framework does not dictate Turkish law, but it is a useful completeness check for a UK patient returning home.
Red flags in a veneer offer
Pause when an offer relies on:
- a fixed veneer count from selfies alone;
- no decay, gum, vitality, crack or bite assessment;
- veneer language for what is actually a crown;
- no-treatment, whitening, orthodontic or bonding alternatives omitted;
- no-prep promised before examination;
- tooth reduction hidden behind a front-view preview;
- a technician or coordinator making clinical decisions;
- no named dentist, facility or verifiable registration;
- one generic porcelain label without exact case material;
- no laboratory identity or prescription;
- a preview presented as the promised final outcome;
- no provisional, try-in or change pathway;
- bonding rushed to meet a flight;
- a package total without tooth-by-tooth scope;
- no local repair, urgent-care or record route.
Resolve material gaps before payment or preparation. Several unresolved gaps justify an independent opinion or choosing a more transparent provider.
Veneer decision worksheet
| Decision | Evidence to request |
|---|---|
| Patient objective | Plain-language concern and no-treatment option |
| Oral health | Decay, gum, vitality, crack and existing-restoration findings |
| Suitability | Tooth-by-tooth enamel, substrate, position and bite assessment |
| Alternatives | Whitening, orthodontics, composite, veneer and crown trade-offs |
| Clinical owner | Named examining and treating dentist with current registration |
| Design | Source records, version, mock-up and limitations |
| Preparation | Additions and reductions on every surface and tooth |
| Material | Exact manufacturer, product, shade and substrate strategy |
| Laboratory | Legal identity, prescription and traceability record |
| Trial stages | Mock-up, provisional, try-in, feedback and stop points |
| Bonding | Isolation, substrate, material record and final checks |
| Consent | Separate gates and renewed agreement after changes |
| Quote | Tooth-by-tooth scope, laboratory, remakes and exclusions |
| Handover | Treatment, material, bite, images, aftercare and local route |
| Maintenance | Cleaning, review, repair and replacement pathway |
Sources and evidence limits
This guide uses the [NHS dental treatment overview](https://www.nhs.uk/live-well/healthy-teeth-and-gums/dental-treatments/), [ADA MouthHealthy veneer guide](https://www.mouthhealthy.org/all-topics-a-z/veneers), [GDC consent standard](https://standards.gdc-uk.org/pages/principle3/principle3), [GDC patient-record standard](https://standards.gdc-uk.org/pages/principle4/principle4) and [GDC consent FAQ](https://standards.gdc-uk.org/pages/principle3/faq).
These sources describe general treatment, consent and record questions in their own jurisdictions. They do not diagnose a tooth, certify a Turkish provider, choose a material or predict appearance, comfort or lifespan. Professional registration, product instructions, evidence and legal requirements change; verify the named clinician, exact material, laboratory, facility and applicable jurisdiction.
Final decision rule
Choose the smallest treatment that meets a clearly defined objective after oral-health, tooth, bite and alternative assessment. Before preparation, require a named clinician, tooth-by-tooth reduction map, exact material and laboratory pathway, staged consent, itemised quote, realistic maintenance, local aftercare and complete records. A fast package or perfect preview is not evidence that irreversible veneers are the right choice.