Head and neck radiotherapy changes the context in which any invasive dental procedure is considered. It does not produce one answer for every person, every jaw or every potential implant site. The relevant questions include which tissues were inside the treated field, how much radiation reached the exact proposed site, how much jaw was exposed, whether treatment has been repeated, what surgery or reconstruction was performed, whether cancer care is active, and what the mouth is like now. Those questions cannot be resolved from a panoramic image, a total treatment figure, a photograph or an online message alone.
Dental implants may be one possible route to oral rehabilitation for selected people after head and neck cancer treatment. They may also be disproportionate when weighed against osteoradionecrosis, wound-healing, infection, dry-mouth, caries, periodontal, functional or continuity-of-care risks. A removable prosthesis, a tooth-supported restoration, preservation of usable teeth, modification of an existing prosthesis, or no elective intervention may be more appropriate. The decision belongs to a named treating clinician working with the relevant cancer and dental specialists, after an examination and review of the original radiotherapy information.
This page is a planning guide, not personalised medical advice, a remote diagnosis or permission to have surgery. It intentionally gives no universal dose cut-off, no fixed waiting period and no promised result. It does not tell anyone to start, stop or change a medicine. It does not replace the person’s oncology, radiation oncology, oral and maxillofacial, restorative, oral medicine or local dental teams.
WeCare is not the treating dental provider. Its limited role is to receive an enquiry, help identify missing administrative records, support a referral to a named clinic and named clinician, and discuss practical logistics only after clinical ownership is clear. The treating clinic and clinician must independently examine the patient, verify the source records, explain options and risks, obtain consent, prescribe or perform care, provide written aftercare and accept responsibility for follow-up. If those responsibilities are unclear, elective travel should pause.
Start with the exact radiotherapy record
“I had radiotherapy to my head or neck” is important history, but it is not a site-specific treatment record. Implant planning should begin with the exact radiotherapy plan, dose distribution, treated volume and anatomical field, together with the location of the planned implant. The 2024 ISOO-MASCC-ASCO guideline emphasises communication between the radiation oncologist and the dental specialist because the amount and volume of jaw exposed at the proposed intervention site matter. A single headline total cannot show what happened to each part of the mandible, maxilla, grafted bone, soft tissue or salivary apparatus.
Ask the treating cancer centre for the radiotherapy treatment summary and, where available, the planning information that allows a radiation oncologist to interpret exposure at the proposed dental site. Useful material may include the diagnosis and anatomical site, treatment dates, technique, planning images, dose distribution or dose-volume information, treated fields, laterality, fractionation summary, any boost or reirradiation, and notes about whether the mandible, maxilla, salivary glands or reconstructed tissues were within the plan. If radiotherapy occurred more than once, the cumulative plan or a specialist reconstruction of the available records may be important. The patient should not be expected to interpret these technical files.
The dental record should also identify prior extractions, episodes of delayed healing, exposed bone, osteoradionecrosis, infection, surgery, flap or graft reconstruction, altered sensation, trismus, feeding or swallowing difficulty, dry mouth, denture trauma and changes in oral function. Add the cancer operation note, reconstruction report, pathology information where relevant, current surveillance plan, medicines, allergies and contact details for the oncology team. A concise referral letter is useful, but it should not substitute for the source material when a specialist needs to understand the treated anatomy.
Records sometimes cannot be recovered. That absence is clinically meaningful; it should not be filled with assumptions based on the year, country, cancer label or patient memory. The named clinicians can decide whether further reconstruction of the treatment history is possible, whether uncertainty can be managed, or whether an elective implant proposal should stop. A sales quotation is not an acceptable substitute for missing cancer-treatment evidence.
Keep copies in a durable format that can be shared with the local dentist, oncology service and any overseas provider. Record who supplied each file and when. Do not crop out patient identifiers, dates, laterality or imaging labels needed for safe interpretation. Secure transfer matters because cancer and imaging records are health data. Use a channel agreed by the relevant provider, confirm the recipient, and ask how long the records will be retained.
Active cancer and oncology-team ownership
Implant rehabilitation must not compete with cancer diagnosis, treatment, surveillance or recovery. The oncology team owns decisions about cancer status, ongoing treatment and whether a proposed dental intervention conflicts with current care. A radiation oncologist interprets the radiotherapy plan. The dental and surgical specialists own the oral diagnosis and proposed dental procedure. One professional should not casually speak for another discipline.
If cancer treatment is ongoing, recurrence is suspected, new symptoms are being investigated, or a surveillance result is outstanding, an elective implant discussion may need to wait. That is not a generic website rule about time. It is a case decision made by the team that understands the cancer, prognosis, treatment burden, blood counts where relevant, medicines, nutrition, airway, swallowing and planned oncology interventions. The same principle applies after reirradiation, major reconstruction, immunotherapy, chemotherapy or other systemic treatment: the actual current context matters more than a calendar label.
The patient should know the name and role of the clinician who confirms cancer-related information and the clinician who accepts responsibility for implant planning. Useful questions include: Is the oncology service aware of this proposal? Who will interpret the proposed implant site against the original plan? Is there any active investigation that should finish first? Could future cancer treatment alter the prosthetic design or access? Who should be contacted if oral symptoms may represent cancer recurrence rather than a dental problem?
No “oncology clearance” phrase should be treated as a transferable certificate. A brief note that someone is medically stable does not answer site-specific dental questions. Equally, a dental scan cannot establish cancer status. The relevant clinicians need a defined question, adequate records and a route to communicate. If there is disagreement, the patient deserves an explanation of the uncertainty and may seek an appropriately qualified second opinion.
Urgent dental infection or severe symptoms still require timely local assessment even when elective implants are deferred. The oncology or hospital dental team can help decide how necessary care should be delivered in the context of previous radiotherapy. Implant marketing must never delay urgent care.
Osteoradionecrosis risk without a website dose threshold
Osteoradionecrosis, often shortened to ORN, is a serious late effect involving irradiated jaw tissue that does not heal normally and can develop exposed or otherwise necrotic bone. It may be associated with pain, infection, discharge, altered sensation, fistula, fracture or major functional impact, but presentation varies and diagnosis belongs to an appropriately qualified team. A website cannot diagnose ORN and cannot rule it out.
Previous radiotherapy does not distribute risk evenly. The exact site, radiation distribution and volume, local tissue condition, prior surgery or reconstruction, oral disease, trauma, smoking, nutrition, medicines, systemic health and the invasiveness of the proposed procedure may all be relevant. Risk is not reduced to a simple “upper jaw versus lower jaw” slogan. Nor does time alone erase the history. NHS professional guidance describes ORN risk after head and neck radiotherapy as potentially lifelong, which is why later invasive dental treatment may need specialist input.
This guide uses no website dose threshold. Published professional guidance may contain technical categories and recommendation qualifiers, but applying them requires the original plan, the intervention location and specialist judgement. Copying one number onto a marketing page could falsely reassure one person and unnecessarily alarm another. The safer public message is that dose distribution and treated volume at the exact site must be reviewed by the relevant radiation oncology and dental specialists.
The 2024 ISOO-MASCC-ASCO guideline supports personalised risk assessment and communication between disciplines. It also reflects limitations in the evidence base. Some recommendations depend on consensus because trials are difficult and patient groups, radiation techniques, anatomy and interventions differ. That uncertainty belongs in consent. It is not a reason to promise that a particular adjunct eliminates risk.
If there is current exposed bone, persistent socket breakdown, unexplained swelling, discharge, a draining tract, worsening pain, altered sensation or suspected fracture, the next step is not an implant quotation. The person needs prompt local clinical assessment through their established cancer, oral and maxillofacial or urgent dental pathway. Imaging and treatment are then selected by the responsible team.
Clinical assessment and imaging limits
A credible assessment is whole-mouth and function-led. It should document the reason rehabilitation is being considered, the patient’s priorities, chewing and speech needs, appearance concerns, denture tolerance, mouth opening, swallowing, nutrition, manual dexterity, oral hygiene capacity, local support and willingness to attend long-term maintenance. The proposed benefit must be specific enough to compare with the burden and risk of treatment.
The examination may need to cover oral mucosa, scars, flap or graft tissues, salivary function, jaw movement, occlusion, remaining teeth, caries, restorability, periodontal condition, existing implants, peri-implant tissues, prostheses, denture-bearing areas, trauma, sensation and suspected infection. Palpation and direct inspection can reveal information that a scan cannot. The clinician should record both positive and negative findings and explain which specialist input is still missing.
Radiographs or cross-sectional imaging may be justified to answer defined clinical questions about teeth, bone, pathology, reconstruction, anatomy or a proposed site. The choice and field should follow professional justification and optimisation. A panoramic image can provide an overview but cannot show the full radiotherapy distribution. Cross-sectional dental imaging can show anatomy but does not prove that irradiated tissue will heal. Radiation planning images answer a different question from dental implant imaging. One should not be presented as a replacement for the other.
Remote photographs and uploaded scans may help a referral service organise the next step, but remote review remains provisional. Image quality, date, orientation, incomplete coverage and missing clinical findings limit interpretation. No one should receive a definitive surgical plan solely from a messaging exchange. The final plan should follow an in-person assessment by the clinician who will be responsible for treatment or by a clearly documented team working together.
Imaging findings may also require escalation outside implant planning. Suspicious lesions, unexplained bone change or symptoms that could relate to cancer or ORN need the appropriate diagnostic pathway. A clinician should explain who owns that investigation and why elective rehabilitation is paused. The absence of pain does not by itself establish that intervention is appropriate.

Tooth preservation and alternatives
Implant planning begins with the question of whether a tooth truly needs replacement. Where a tooth is restorable and maintainable, preserving it may avoid an invasive intervention in irradiated tissues. That does not mean every tooth must be retained. It means extraction and replacement should follow a diagnosis, prognosis discussion and comparison of burdens rather than an automatic package design.
Possible routes may include prevention and disease control, restoration of a tooth, endodontic care, periodontal care, adjustment or repair of an existing prosthesis, a tooth-supported option, an adhesive option, a removable partial or complete prosthesis, an obturator, or accepting a space. Each option has limitations. A removable design can create pressure or friction on vulnerable mucosa if it fits poorly, so design, review and adjustment matter. A fixed tooth-supported option depends on the condition and prognosis of potential supporting teeth. No-treatment may be reasonable when intervention offers little functional benefit or adds disproportionate burden.
For people with major surgical reconstruction, prosthetic needs may be complex. An implant can sometimes help retain a prosthesis, but the plan must account for reconstructed anatomy, tissue mobility, access, sensation, hygiene and future surveillance. The desired result may be improved retention or function rather than replication of natural dentition. The patient should understand what the prosthesis is expected to do, what it cannot do, and what maintenance or replacement might involve.
The 2024 guideline advises consideration of alternatives when invasive intervention would affect a higher-risk area. That is a clinical comparison, not an instruction that one anatomical region is always acceptable. A restorative dentist or prosthodontist should be involved early enough to test whether the proposed implant position and number would actually support a maintainable prosthesis. Surgical feasibility without a workable restoration is not a complete plan.
Ask for a written options table. For each route, it should state the purpose, evidence and uncertainties, invasive steps, likely maintenance, impact on local follow-up, foreseeable complications, and what happens if the route is stopped. A patient should be able to choose an alternative without being told that declining implants means declining care.
Dry mouth, caries and periodontal control
Head and neck radiotherapy can reduce salivary gland function and cause persistent dry mouth. Saliva supports comfort, lubrication, swallowing, speech, taste, buffering and protection against tooth decay. A dry mouth can therefore affect remaining teeth, mucosa, denture tolerance, diet, sleep and the ability to maintain a complex implant prosthesis. The severity and pattern vary with the treated structures and the individual.
Assessment should document symptoms, salivary function where clinically useful, hydration and diet context, caries activity, plaque control, mucosal soreness, infection, denture trauma and access for cleaning. A person may be coping well in daily life yet still face accelerated caries or mucosal injury. Conversely, a self-report of dryness does not establish a particular diagnosis or treatment. The named local dentist, oral medicine clinician or cancer team should individualise preventive and symptom-management advice.
The ISOO/MASCC/ASCO guideline on salivary gland hypofunction and xerostomia describes preventive and supportive approaches but does not turn them into a universal home prescription. Products, medicines and stimulation methods can have contraindications, interactions or practical limitations. This page therefore does not tell readers to start a medicine, use a particular concentration, or follow a fixed regimen. Ask the responsible clinician for written instructions suited to the person’s teeth, mucosa, swallowing, medicines and oncology history.
Active caries, uncontrolled periodontal inflammation or an unmaintainable hygiene situation changes the risk-benefit discussion. Disease control should be demonstrated over time in the person’s real environment, not only during a short treatment trip. The plan should show who will provide prevention, periodontal monitoring and prosthesis maintenance near home. A complex restoration that cannot be cleaned because of trismus, altered anatomy, limited dexterity or design is not made appropriate by adding implants.
Dry-mouth and caries planning continues after rehabilitation. Components, contours and cleaning access should be chosen with long-term care in mind. The local dentist needs baseline records and a clear escalation route. If the person cannot secure local maintenance, a lower-burden alternative or no elective surgery deserves serious consideration.
Smoking, nutrition and medical context
Smoking can affect oral disease, wound healing and the wider cancer-survivorship context. It should be recorded without judgement, including current use, recent change, other nicotine products and exposure patterns. A website should not impose a fictional abstinence interval or imply that one declaration removes risk. The named clinicians should explain how smoking affects the proposed plan and offer referral to evidence-based cessation support through the person’s usual healthcare where appropriate.
Vaping and other nicotine delivery methods should also be disclosed. Evidence and exposure vary, and they should not be marketed as a guaranteed risk-free substitute for oral surgery. Do not self-prescribe nicotine or cessation medicine from an online article. A GP, pharmacist or established cessation service can consider interactions, cancer treatment, cardiovascular history and individual preference.
Nutrition may be affected by dry mouth, altered taste, chewing difficulty, pain, swallowing problems, previous surgery or cancer therapy. A person may prioritise oral rehabilitation because eating has become difficult, yet elective surgery can also add burden. A dietitian or speech and language therapist may be relevant where intake or swallowing is compromised. Weight change, feeding support, aspiration concerns and nutritional supplements should be discussed with the established team rather than hidden to keep a travel date.
The clinical history should include medicines, allergies, anticoagulant or antiplatelet treatment, antiresorptive or antiangiogenic medicines, immune-modifying treatment, diabetes, cardiovascular or respiratory conditions, previous bleeding or infection problems, renal or liver issues and any other factor identified by the treating clinician. This is not a checklist that makes someone suitable once every box is filled. It helps the responsible team identify questions, coordinate with usual care and avoid unsafe medicine changes.
Patients should never stop cancer, blood-thinning, bone, immune or other prescribed medicine because an implant itinerary says so. Any change belongs to the prescriber and dental clinician working from the actual indication and procedure. If medicine information is uncertain, resolve it before elective intervention.
Specialist multidisciplinary planning
“Specialist review” should mean identifiable professionals with relevant scopes, not a generic logo or sales phrase. Depending on the case, the planning group may involve the radiation oncologist, head and neck oncologist or surgeon, oral and maxillofacial surgeon, restorative dentist or prosthodontist, oral medicine clinician, periodontist, dental radiologist, local general dentist, oncology nurse, dietitian, speech and language therapist, and another prescriber. Not every person needs every discipline, but the reasons for including or excluding relevant expertise should be clear.
The multidisciplinary question must be specific. Examples include: What radiation did the proposed site receive? Is cancer treatment or surveillance affected? Is there suspected ORN or another condition needing diagnosis? Can remaining teeth be maintained? Is a removable option workable? Would the proposed prosthesis improve a defined function? Can it be cleaned and serviced? Who will manage complications after the patient returns home?
A handover should name the clinical owner for each stage. One clinician accepts responsibility for the dental diagnosis and overall plan. Another may perform surgery. Another may provide the prosthesis. The local dentist may deliver maintenance, but only after agreeing and receiving sufficient information. The oncology team remains responsible for cancer-related decisions. When a provider cannot state who owns a decision, the patient should not be expected to infer responsibility from messages sent by a coordinator.
The team should record areas of agreement, uncertainty and disagreement. If clinicians recommend against implants, the patient should receive the reasons and alternative rehabilitation options. If they support proceeding, the written rationale should connect the proposed benefit with site-specific evidence and explain residual risk. A second opinion should review the source records, not merely endorse a previous quotation.
Cross-border care adds communication challenges: language, time zones, record formats, professional registration and different urgent-care systems. Before booking, ask how specialists communicate, whether interpretation is independent and accurate, how questions become part of the clinical record, and who will explain changes in a language the patient understands. Consent cannot depend on an informal companion translating complex risk.

Implant-site and prosthesis planning
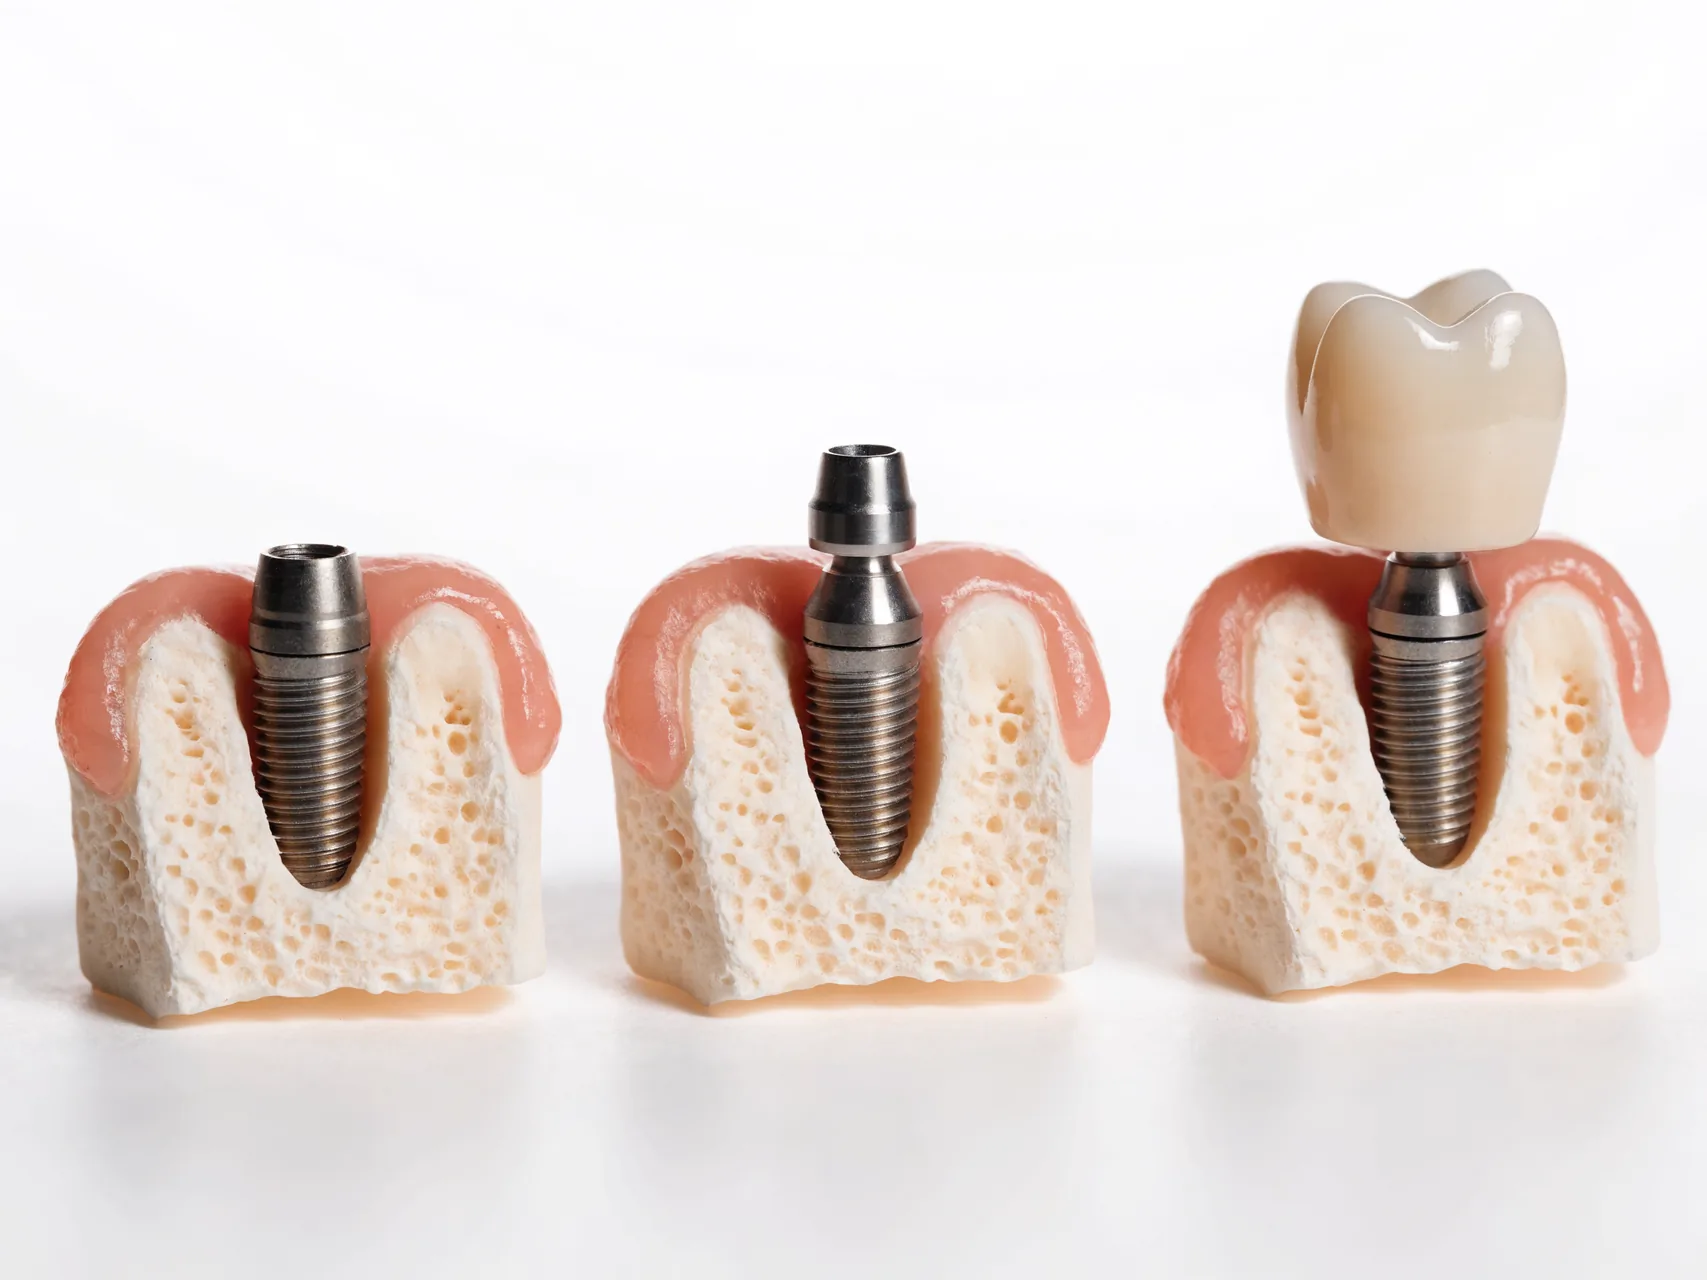
An implant is one component of a rehabilitation system. Planning should start with the intended function and prosthesis, then work backward to whether any implant position is biologically, anatomically and mechanically defensible. In a post-radiotherapy mouth, tissue health, altered anatomy, reconstruction, scarring, dry mouth, sensation, mouth opening and cleaning access can be as important as bone dimensions on a scan.
For each proposed site, the record should link the planned implant position to the radiation information. It should also describe bone and soft-tissue findings, nearby structures, existing disease, prosthetic space, occlusal considerations, access for surgery and maintenance, and any uncertainty. The fact that another jaw region appears less exposed does not create an automatic green light. Likewise, implant count should not be chosen from a package name.
The restorative plan should identify whether the prosthesis is fixed or removable, how it will be retained, how it can be cleaned, how clinicians will inspect underlying tissues, and how components can be repaired or replaced. It should address speech, lip support, chewing goals, appearance, bite forces, opposing teeth and parafunctional habits. If the person has reduced sensation or dexterity, monitoring and cleaning design deserve extra attention.
There is no fixed waiting period in this guide. Timing after radiotherapy, after reconstruction, between surgical and restorative stages, and before loading depends on cancer status, tissue condition, the actual intervention, healing observations and the responsible team’s judgement. A calendar alone cannot prove biological readiness. “Same trip” language should never override the option to stop, stage or change the plan after examination.
The plan should also say what happens if an implant cannot be placed, does not integrate, becomes infected or cannot support the planned prosthesis. A fallback may involve modifying the prosthesis, using fewer or no implants, returning to a removable design, further assessment or no additional surgery. These are clinical contingencies, not guaranteed remedial promises.
Hyperbaric oxygen and evidence uncertainty
Hyperbaric oxygen, often called HBO, involves breathing oxygen in a pressurised environment under medical supervision. Its role in preventing or managing osteoradionecrosis has been debated for decades. Older local pathways and patient leaflets may describe it differently, and patients may encounter detailed schedules online. Those schedules should not be copied into a personal plan without specialist review.
The current 2024 ISOO-MASCC-ASCO guideline states that routine prophylactic hyperbaric oxygen before dental extractions is not recommended and that evidence supporting HBO for prevention and management of ORN is limited. The guideline contains qualifying context for individual cases, but it does not justify advertising HBO as a universal safeguard for implant surgery. Evidence about implants specifically is also limited and heterogeneous.
This means neither “everyone needs HBO” nor “HBO is never discussed” is a responsible public rule. If a specialist raises it, ask what precise clinical problem is being addressed, which evidence applies, what uncertainty remains, what contraindications or burdens matter, who provides the medical assessment, and what alternatives exist. The decision must come from the responsible clinicians, not a travel coordinator.
HBO does not replace review of the radiation plan, disease control, atraumatic clinical judgement, informed consent or long-term follow-up. It should not be described as restoring tissue to its pre-radiotherapy state or eliminating ORN. Financial consent should separate any external service and make clear what happens if the patient cannot or chooses not to undergo it.
Other proposed adjuncts also require caution. Do not start medicines or supplements mentioned in professional guidelines without the prescriber and dental clinician considering the actual procedure, indication, bleeding risk, interactions and contraindications. This guide deliberately gives no drug dose or regimen.
Consent under lifelong uncertainty
Valid consent is a conversation and continuing process, not a signed travel form. The patient needs information about the diagnosis, purpose of rehabilitation, material alternatives, no-treatment option, uncertainties, foreseeable risks, likely maintenance, costs, clinician identity and what happens if the plan changes. They need time to ask questions and should not lose a deposit merely for requesting clarification about clinical risk.
Post-radiotherapy consent should address ORN, delayed or failed healing, infection, pain, altered sensation, implant loss, prosthetic complications, tissue trauma, caries and periodontal disease in remaining teeth, dry-mouth burden, need for ongoing review and the limits of remote care. It should explain that a favourable assessment cannot remove lifelong uncertainty and that future cancer or dental care may alter the restoration.
Consent should distinguish clinical decisions from commercial terms. The clinician explains clinical options and accepts clinical responsibility. The business explains charges, cancellation, revision and complaint terms. A commercial promise cannot turn uncertain biology into a guarantee. If a quoted plan changes after examination, the patient should receive the reason, updated options and costs before agreeing.
Language support matters. The patient should understand complex terms without relying on promotional shorthand. An interpreter should be competent and independent where needed, and the record should state how communication occurred. Consent also includes permission for relevant professionals to share health information. The patient should know what will be sent, to whom, for what purpose and how to withdraw optional permissions.
Capacity may fluctuate because of illness, medicines, fatigue or distress. The treating team must follow applicable professional and legal duties rather than assuming a signature settles the issue. A companion can support the patient, but should not replace the patient’s voice or the clinician’s responsibility.
Records and clinical handover
Good records allow another qualified professional to understand what was known, decided and done. Before treatment, the file should include the cancer and radiotherapy documents, medical and medicine history, dental assessment, clinical photographs where justified, radiographs with dates and identifiers, specialist opinions, options considered, consent discussions and the final written plan.
After any procedure, the patient and local provider may need a discharge summary identifying the named clinic and clinicians, procedure sites, materials and implant/component identifiers, operative findings, complications, medicines prescribed, laboratory or pathology results where relevant, prosthesis design, occlusal decisions, aftercare instructions, review findings and escalation contacts. Records should clearly distinguish a provisional component from a definitive one.
The radiation plan and oncology summary should remain linked to the dental file because later clinicians may need them. Do not assume the overseas provider will be reachable indefinitely. Give the patient copies in a usable format, with image files that preserve diagnostic quality rather than screenshots. The local dentist should receive information with the patient’s consent and have a named clinical contact for questions.
Remote messages about symptoms should be added to the clinical record and triaged by an accountable professional. A messaging service is not an emergency department and cannot examine tissue, test mobility, take imaging or assess airway compromise. The written handover must state the limits of remote review and direct the patient to local services when needed.
GDC guidance on records, consent, treatment planning and dental care abroad supports clear written information, provider checks, aftercare planning and contemporaneous records. Patients can ask for professional registration details and verify them with the relevant regulator. A referral coordinator’s brand does not substitute for the named treating entity’s registration and complaint route.
Local maintenance and urgent escalation
Post-radiotherapy rehabilitation needs local maintenance, not only a return visit to the treating clinic. Before travel, identify a local dentist or appropriate specialist willing to provide ongoing examinations, prevention, periodontal and peri-implant monitoring, prosthesis review and urgent assessment. Send them the proposed plan early enough for meaningful input. Do not promise that any dentist will service unfamiliar components without prior agreement.
Maintenance frequency and content should be individualised. It may include examination of mucosa and reconstructed tissues, caries and periodontal review, prosthesis fit, hygiene access, implant and peri-implant assessment, functional review and imaging only when clinically justified. The patient should receive tailored home-care instructions from the treating clinician, with adaptations for dry mouth, trismus, altered anatomy or dexterity. This page does not prescribe a universal schedule or product.
Symptoms that deserve prompt local assessment include new or worsening pain, swelling, discharge, a persistent sore area, exposed or non-healing bone, a draining tract, fever with dental symptoms, altered sensation, increasing difficulty opening the mouth, a loose implant or prosthesis, or a sudden change in function. These signs have several possible causes; an online service should not label them ORN without examination.
Heavy bleeding that does not stop, severe swelling affecting breathing, swallowing or the eye, major facial trauma, collapse or another life-threatening symptom requires emergency care through the local emergency system. Do not fly or wait for a remote reply. For urgent but non-life-threatening dental problems, use the local urgent dental or hospital pathway and inform the oncology team when relevant.
The handover should explain who pays for local assessment, repairs, imaging or emergency treatment. Clinical urgency must not depend on prior financial approval. Commercial discussions can follow once immediate safety is addressed.

Travel and the no-travel option
Travel is a separate decision from clinical suitability. A patient can be clinically considered for a procedure yet reasonably decide that distance, fatigue, swallowing or nutrition issues, airway concerns, mobility, communication, cost, insurance or lack of local follow-up make travel inappropriate. The no-travel option must remain available throughout planning.
Before booking, ask the oncology and treating teams whether any current condition or planned care affects travel. Obtain insurer guidance in writing where relevant; do not assume ordinary travel insurance covers planned treatment or complications. Consider accessibility, medicines in transit, secure carriage of records, dietary needs, support from a companion, and how urgent care would be accessed both abroad and after returning home.
No website can provide a universal flight interval after implant or related surgery. The appropriate timing depends on the procedure, anaesthesia, bleeding and swelling, observed healing, complications, general health and access to care. The treating clinician should provide case-specific written advice after assessing the person. Tickets that cannot be changed can pressure unsafe decisions, so flexible travel arrangements are preferable where possible.
The patient should know the clinic address, treating clinician, appointment purpose, likely decision points, and what is and is not clinically confirmed before departure. A preliminary remote proposal may change after examination. Build enough flexibility for further assessment, a staged procedure, or no procedure at all.
If continuity near home cannot be arranged, local rehabilitation or a lower-maintenance option may be safer and more practical. Choosing not to travel is not a failed plan. It is a legitimate outcome of informed comparison.
Itemised quote and commercial terms
An itemised quote should follow a defensible clinical plan. It should separate consultations, specialist opinions, imaging, laboratory work, surgery, anaesthesia or sedation, materials and components, temporary and definitive prostheses, maintenance, revisions, medicines and external services. Travel and accommodation logistics should be priced separately from clinical care so that commercial bundling does not hide who supplies each service.
The quote should identify provisional items and assumptions. For example, an implant proposal may depend on examination, radiotherapy interpretation, tissue condition or specialist review. If an item cannot be confirmed until a later stage, say so. State the currency, payment schedule, cancellation terms, refund rules and how price changes are approved.
Remedial terms should be written without presenting a biological outcome as guaranteed. Ask what is covered when a component is defective, what is excluded, who decides the cause of a problem, what evidence is required, whether professional fees differ from travel costs, and which jurisdiction and complaint process apply. A vague coverage label without those details can mislead.
Clinical records, urgent advice and complaint access should not be withheld because of a payment dispute. The patient should receive the named provider’s complaint procedure and know how to contact the relevant professional regulator. A second opinion should be possible without surrendering source records.
WeCare’s logistics boundary should be explicit in any document: it may relay an enquiry or practical information, but it does not diagnose, prescribe, select an implant site, interpret a radiotherapy plan or guarantee a clinical outcome. Clinical charges and responsibilities belong to the named provider that accepts the patient.
Questions to ask before implant treatment
Use these questions to test whether the proposal is record-led and accountable:
- Who is the named clinician responsible for the overall dental diagnosis and plan?
- Which registered entity is the treating clinic, and how can its status be verified?
- Has the radiation oncologist reviewed the exact proposed implant site against the original plan?
- Which radiotherapy documents were obtained, and what remains missing?
- Is cancer treatment complete, ongoing or under investigation, and who confirmed that status?
- Has suspected ORN, recurrent disease or another cause of symptoms been considered through the proper diagnostic pathway?
- Which remaining teeth can reasonably be preserved, and what evidence supports extraction?
- What non-implant and no-treatment options could meet the functional goal?
- How do dry mouth, caries, periodontal health, mouth opening and reconstructed anatomy affect the proposal?
- What does the prosthesis need to achieve, and can it be cleaned, inspected and repaired?
- What uncertainties remain about healing and long-term maintenance?
- Why is each image or investigation needed, and who interprets it?
- If HBO or another adjunct is discussed, what exact problem is it intended to address and what does current evidence say?
- What are the foreseeable ORN, infection, healing, nerve, prosthetic and maintenance risks?
- Who will provide local maintenance and urgent care after the patient returns home?
- What records and component identifiers will the patient receive?
- What happens clinically and financially if the plan changes or no implant is placed?
- How are consent, interpretation, privacy, complaints and second opinions handled?
- Does the travel plan allow assessment, staging, delay or cancellation without clinical pressure?
Answers should appear in the clinical record or written plan, not only in a sales chat. “The doctor will decide later” may be honest at an early stage, but the patient should know what evidence the decision will use and should not be asked to consent or pay for an irreversible procedure before the decision is explained.
Post-radiotherapy implant planning checklist
Cancer and radiotherapy evidence
- Exact cancer diagnosis, anatomical site and current treatment or surveillance status recorded.
- Radiotherapy summary and source planning information requested from the treating centre.
- Dose distribution, treated volume and anatomical field reviewed in relation to each proposed implant location.
- Previous surgery, reconstruction, reirradiation and ORN history documented.
- Radiation oncologist and oncology contact identified.
Dental and functional assessment
- In-person whole-mouth examination completed by an accountable clinician.
- Mucosa, saliva, caries, periodontal health, teeth, prostheses, mouth opening, sensation and hygiene access assessed.
- Functional goals for chewing, speech, appearance and prosthesis retention written down.
- Imaging justified for defined questions and its limits explained.
- Suspicious lesions or symptoms referred through an appropriate diagnostic pathway.
Options and clinical ownership
- Tooth preservation, removable, tooth-supported, implant and no-treatment routes compared.
- Named clinician accepts responsibility for the diagnosis and final plan.
- Relevant oncology, surgical, restorative, oral medicine and local dental input recorded.
- No website dose threshold or calendar rule used as a substitute for individual assessment.
- No fixed waiting period or promised result used to secure a booking.
Consent and continuity
- ORN, delayed healing, infection, implant and prosthetic complications, dry mouth, caries and maintenance discussed.
- Patient understands the limits of remote review and the right to stop or seek a second opinion.
- Local maintenance provider identified before invasive care.
- Urgent and emergency pathways written down for both locations.
- Discharge records, imaging, procedure details and component identifiers promised in a usable format.
Travel and commercial clarity
- Travel fitness and timing discussed with the appropriate clinical teams.
- Flexible arrangements allow staging, delay or the no-travel option.
- Itemised clinical quote separated from travel logistics and external services.
- Cancellation, revision, complaint and remedial terms supplied in writing.
- The roles of WeCare, the named treating clinic and every external supplier are clearly separated.
This checklist cannot turn a complex history into a yes-or-no answer. Its purpose is to reveal missing evidence, unclear ownership and continuity gaps before the patient accepts risk.
Sources and review dates
This guide was reviewed against the following sources. Guidance can change, so clinicians should check the current version and the patient’s actual records rather than relying on this summary.
- [ISOO-MASCC-ASCO osteoradionecrosis guideline](https://ascopubs.org/doi/10.1200/JCO.23.02750), published 1 May 2024 and accessed 29 August 2026. It supports site-specific review of radiation exposure, multidisciplinary communication and acknowledgement of limited evidence for several preventive adjuncts.
- [ISOO/MASCC/ASCO salivary gland hypofunction and xerostomia guideline](https://pubmed.ncbi.nlm.nih.gov/34283635/), published 2021 and accessed 29 August 2026. It supports structured assessment and clinician-led management of dry-mouth effects.
- [MASCC/ISOO mucositis guideline](https://pmc.ncbi.nlm.nih.gov/articles/PMC7540329/), published 2020 and accessed 29 August 2026. It supports basic oral care and appropriate dental evaluation in cancer care while recognising intervention-specific evidence limits.
- [NICE NG36: cancer of the upper aerodigestive tract](https://www.nice.org.uk/guidance/ng36/chapter/recommendations), published 10 February 2016, subsequently updated, and accessed 29 August 2026. It describes multidisciplinary head and neck cancer management and consideration of treatment volume, treatment effects and function.
- [NHS head and neck radiotherapy dental-care information](https://www.gloshospitals.nhs.uk/your-visit/patient-information-leaflets/dental-care-information-for-patients-who-will-receive-head-and-neck-radiotherapy/), current leaflet with review due February 2028 and accessed 29 August 2026. It explains long-term dry mouth, caries and ORN concerns and the importance of continuing dental care.
- [NHS urgent dental guidance](https://www.nhs.uk/nhs-services/dentists/how-to-find-an-nhs-dentist-in-an-emergency/), accessed 29 August 2026. It distinguishes urgent dental problems from emergencies such as uncontrolled bleeding or swelling affecting breathing.
- [GDC Principle 2: communicate effectively](https://standards.gdc-uk.org/pages/principle2/principle2), accessed 29 August 2026. It supports clear written treatment plans, costs and explanations when plans change.
- [GDC Principle 3: obtain valid consent](https://standards.gdc-uk.org/pages/principle3/principle3), accessed 29 August 2026. It supports patient-specific discussion of options, risks and the right to decide.
- [GDC Principle 4: maintain and protect patient information](https://standards.gdc-uk.org/pages/principle4/principle4), accessed 29 August 2026. It supports accurate, contemporaneous and secure records.
- [GDC guidance for people considering dental treatment abroad](https://www.gdc-uk.org/standards-guidance/information-for-patients-public/going-abroad-for-dental-treatment), accessed 29 August 2026. It supports verification of providers, clear aftercare, complaint planning and careful comparison before travel.
Evidence, technology and individual health change. The source list helps a patient ask better questions; it is not a clinical instruction. The named treating professionals remain responsible for checking current guidance and applying it to the exact radiotherapy record, oral findings, proposed site and patient priorities.