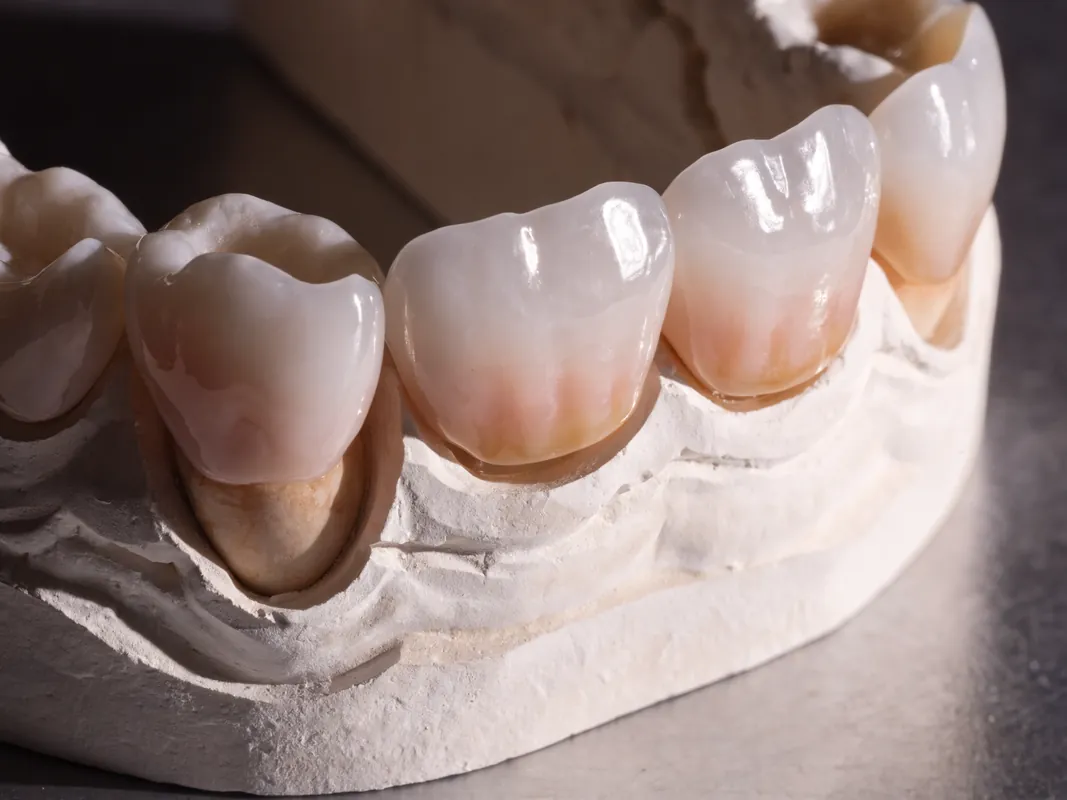
A search for root canal with zirconia crown combined often begins with a painful tooth, an old root filling, a broken restoration or a quotation that treats two procedures as one product. The search phrase is useful, but it does not establish diagnosis, restorability, crown need or material choice.
Root canal treatment and the restoration that follows are linked but distinct decisions. The endodontic decision concerns the pulp and tissues around the root. The restorative decision concerns whether enough maintainable tooth remains, how it can be sealed and protected, what design is appropriate, and whether the wider bite and maintenance conditions support that design. A patient can receive technically completed root canal treatment yet still have a tooth that cannot be predictably restored. A tooth can also need endodontic care without automatically needing a full zirconia crown.
This guide publishes no fixed price, appointment count, treatment duration, response time, comfort promise, outcome percentage, lifespan, warranty, saving or travel schedule. It does not decide whether a particular tooth needs root canal treatment, retreatment, surgery, extraction, a crown, an onlay, a direct restoration, a post or zirconia. Those choices require examination and case-specific professional judgment.
The purpose is verification and sequencing. It explains how to identify the legal provider and responsible clinicians, test the diagnosis and restorability, compare alternatives, understand imaging and consent, verify isolation and disinfection boundaries, protect the tooth between stages, assess residual structure, document core, post and ferrule decisions, compare crown materials without assuming zirconia superiority, trace laboratory work, check fit and occlusion, plan aftercare and local handover, and stop travel when urgent care is needed.
For separate service overviews, see the root canal treatment guide and zirconia crowns guide. This page focuses on the interface between them.
Begin with the legal provider and two clinical owners
Before sharing health records or paying, identify the exact legal healthcare provider. A brand, coordinator, travel company or marketing site may arrange communication without being the entity responsible for diagnosis or treatment.
The personal record should name at least two clinical responsibilities:
- the clinician who owns the endodontic diagnosis and root-canal stage;
- the clinician who owns restorability, provisional sealing and final restoration.
One clinician may hold both roles if appropriately trained and responsible. The point is not to require a particular job title. The point is to prevent each stage from being assumed to belong to someone else.
Also identify:
- the facility where each stage will occur;
- the clinician who interprets images;
- the clinician who decides whether referral is needed;
- the laboratory or fabricating party when known;
- the data controller for records;
- the entity receiving payment;
- the provider responsible for urgent concerns;
- the provider responsible for routine aftercare;
- the complaint contact.
Verify current professional and facility status through the appropriate official source. Names on a website do not prove personal involvement. Ask for those names in the dated plan, consent and treatment notes.
Use a responsibility table:
| Decision | Named owner and evidence |
|---|---|
| Pulpal and apical diagnosis | Clinician, findings and records reviewed |
| Restorability | Clinician, residual-structure and periodontal assessment |
| Alternatives | Clinician-led discussion and patient decision |
| Endodontic procedure | Treating clinician and stage record |
| Temporary or provisional seal | Material category, placement and review responsibility |
| Core or post | Restorative clinician, indication and tooth-preservation boundary |
| Crown or other restoration | Restorative clinician, design and material rationale |
| Laboratory prescription | Prescribing clinician and laboratory identity |
| Fit and occlusion | Clinician, checks and adjustments |
| Handover | Provider, record set and local-care pathway |
If the endodontic and restorative owners disagree, the disagreement should be documented before irreversible treatment proceeds.
Diagnosis comes before the root-canal label
Pain, sensitivity, tenderness, swelling, a dark tooth, a radiographic finding or an old restoration can have different causes. A message or image may support triage, but it does not replace the diagnostic process selected by the responsible clinician.
The [European Society of Endodontology clinician resources](https://www.e-s-e.eu/for-professionals/resources-for-clinicians/) link to its current evidence-based guideline for pulpal and apical disease. The guideline emphasises history, case evaluation, aseptic practice, appropriate training and reassessment. It does not turn one symptom into a universal treatment.
Ask the endodontic owner to document:
- the patient's concern and symptom history;
- relevant medical and dental history;
- clinical tests performed;
- teeth used for comparison where appropriate;
- periodontal and restorative findings;
- imaging reviewed;
- pulpal diagnosis or clearly stated uncertainty;
- apical diagnosis or clearly stated uncertainty;
- whether a crack, trauma, referred pain or non-dental cause is considered;
- whether the tooth has previous endodontic treatment;
- what additional information could change the diagnosis;
- why the proposed option is preferred;
- the consequences and uncertainty of alternatives.
A treatment name should follow this record. It should not be the starting assumption.
Restorability is a separate gate
A tooth may be endodontically treatable but not restorably maintainable. Before root canal treatment, ask whether the final restoration can be designed without hiding a poor structural, periodontal or functional outlook.
The restorability assessment may consider:
- remaining sound tooth structure;
- location and depth of decay or damage;
- cracks or suspected fracture;
- previous restorations and access;
- margin location;
- periodontal support and maintainability;
- crown-to-root relationships relevant to the case;
- space and alignment;
- bite contacts and loading;
- parafunctional history;
- ability to isolate and seal the tooth;
- possibility of an acceptable provisional restoration;
- future hygiene access;
- relation to adjacent teeth and planned work;
- patient priorities and tolerance for uncertainty.
This is not a scoring system for patients to apply themselves. The restorative owner should state which findings matter and how they affect the choice.
Ask for a written restorability verdict:
- restorable on the current evidence;
- provisionally restorable pending further information;
- uncertain and requiring another assessment;
- not considered restorable by the responsible clinician.
If the verdict is provisional, list the change triggers. Root canal treatment should not be sold as proof that a crown can later be fitted.
Do not accept the brittle-tooth shortcut
A common sales explanation says that every root-filled tooth becomes brittle because the pulp or internal moisture is removed. That is too simple. The amount and distribution of remaining tooth structure, existing damage, cracks, cavity configuration, restoration design, tooth position and loading all matter.
The [European Society of Endodontology position statement on restoring root-filled teeth](https://onlinelibrary.wiley.com/doi/full/10.1111/iej.13607) explains that restoration choice is multifactorial and should preserve sound residual structure. It also describes circumstances in which cuspal coverage may not be necessary. A full crown is therefore not an automatic consequence of root canal treatment.
Ask the restorative clinician:
- what structural finding supports cuspal coverage;
- whether a direct restoration, onlay, endocrown, crown or another option was considered;
- how much additional tooth preparation each option requires;
- what the intended benefit and trade-off are;
- whether a crack changes the decision;
- how the position in the mouth affects design;
- how the opposing tooth and bite affect design;
- how future repair or replacement would work.
Do not let an unsupported statement about brittleness replace this analysis.
Compare all reasonable alternatives
A responsible plan should discuss alternatives before payment or travel. Depending on diagnosis and restorability, these may include:
- monitoring or no active treatment;
- disease management short of root canal treatment where appropriate;
- vital-pulp treatment where appropriate;
- root canal treatment and a suitable restoration;
- endodontic retreatment for a previously treated tooth;
- surgical endodontic assessment where relevant;
- extraction;
- extraction followed by no replacement;
- extraction followed by a removable, tooth-supported or implant-related option after separate assessment;
- an independent opinion.
The guide does not recommend one option. It requires the clinician to explain which alternatives are reasonable for the personal case.
For each alternative, request:
- clinical purpose;
- material risks and uncertainties;
- effect on symptoms or infection;
- effect on remaining tooth structure;
- expected maintenance;
- future treatment implications;
- financial scope;
- travel implications;
- consequences of delay or no treatment;
- point at which the option may no longer remain available.
Extraction should not be presented as a simple failure of root canal treatment. It is a separate irreversible decision with its own consequences and replacement questions. No treatment should not be dismissed without explaining the clinical risk of waiting.
Imaging must answer a documented question
Imaging should support diagnosis, anatomy, restorability, treatment planning or review. It should not be ordered merely because a device is available or repeated without explaining the need.
Ask:
- which image is proposed;
- what diagnostic question it addresses;
- whether a recent usable image already exists;
- who justifies and interprets it;
- what limitations remain;
- how findings are recorded;
- how the image changes the plan;
- how the patient obtains a copy.
A panoramic image may not answer the same question as an intraoral image or a three-dimensional scan. This guide does not prescribe which modality is appropriate. The responsible clinician should use current guidance and individual justification.
If imaging reveals a possible crack, resorption, unusual anatomy, previous treatment issue or lesion, ask whether referral or further assessment is indicated. Do not convert an uncertain image into a certainty claim in a quotation.
Consent must be versioned across both stages
Consent for root canal treatment is not blanket consent for a post and zirconia crown. Each stage has different alternatives, risks, preparation and cost.
A valid consent record should cover:
- diagnosis and uncertainty;
- restorability status;
- proposed endodontic procedure;
- alternatives and no-treatment consequences;
- anaesthesia and isolation;
- possible findings that could stop or change treatment;
- provisional sealing plan;
- final restorative options;
- core and post decisions;
- crown preparation and material;
- laboratory involvement;
- aftercare;
- urgent-care pathway;
- travel uncertainty;
- itemised costs and exclusions.
The current [GDC consent standard](https://standards.gdc-uk.org/pages/principle3/principle3) treats consent as an ongoing process for professionals under its jurisdiction and requires changes to treatment or estimated cost to be discussed and documented. That is a useful transparency benchmark even where another jurisdiction governs treatment.
A signature is not the whole process. The patient should have information in a language and format they understand, time to ask questions, and the ability to pause before an irreversible stage. If diagnosis, restorability, material or scope changes, create a new version.
Stage gate A: urgent need versus planned travel
A patient with active pain or swelling may need local assessment before considering international treatment. Travel planning must not delay urgent care.
Use current official guidance for the patient's location. The [NHS dental abscess guidance](https://www.nhs.uk/conditions/dental-abscess/) states that an abscess needs urgent dental treatment and gives emergency escalation signs, including difficulty breathing, speaking or swallowing, significant mouth swelling and eye involvement.
Seek urgent local dental help when there is suspected abscess, increasing swelling, uncontrolled pain, fever or deterioration. Use emergency services when current local guidance indicates airway, swallowing, eye, severe systemic or rapidly spreading concerns. Do not board a flight or wait for a remote reply when emergency assessment is needed.
The first gate asks:
- Is the patient medically and dentally safe to travel?
- Has urgent infection or swelling been assessed locally?
- Is immediate drainage, extraction, endodontic access or another urgent step required?
- Are antibiotics being mistakenly treated as definitive dental treatment?
- Who owns follow-up if symptoms change before departure?
- Does the insurer cover the situation?
A future appointment abroad is not an emergency plan.
Stage gate B: confirm endodontic diagnosis and tooth preservation
When urgent needs are stable, the responsible clinician should confirm the diagnosis, restorability and alternatives before beginning definitive endodontic work.
The gate record should state:
- diagnostic findings;
- restorability status;
- patient's priorities;
- alternatives discussed;
- referral need;
- isolation feasibility;
- expected endodontic scope;
- provisional restoration plan;
- final restoration options still open;
- reasons to stop;
- consent version.
If the tooth cannot be isolated or restored, the clinician should explain how that affects the plan. If a crack or periodontal finding changes the outlook, do not proceed simply because laboratory work has been scheduled.

Isolation is a safety and disinfection boundary
Root canal treatment involves managing a complex internal space while preventing contamination and protecting the patient. Ask how the tooth will be isolated.
The [British Endodontic Society root-canal guidelines](https://britishendodonticsociety.org.uk/_userfiles/pages/files/a4_bes_guidelines_2022_hyperlinked_final.pdf) state that rubber-dam isolation is mandatory for root canal treatment. The treating clinician should explain their isolation method, how the operating field is disinfected and what happens if adequate isolation cannot be achieved.
Verification questions include:
- Is rubber dam planned?
- Can the clamp and seal be placed safely?
- Is pre-endodontic build-up needed to create an isolatable tooth?
- How is leakage controlled?
- What happens if isolation fails?
- How are instruments and irrigants prevented from entering the mouth?
- How is the field disinfected?
- How is contamination between stages prevented?
Do not accept a microscope, file brand or equipment list as a substitute for aseptic isolation. Magnification can support work but does not independently prove diagnosis, disinfection or outcome.
Disinfection and canal preparation need a clinical record
Patients do not need to choose an instrument system or irrigation brand. They do need a record showing that an appropriately trained clinician took responsibility for cleaning, shaping, disinfecting, filling and sealing the canal system.
The procedure record can include:
- access route;
- isolation;
- canal anatomy identified;
- working-length method;
- preparation approach;
- irrigating-solution categories and safety steps;
- inter-appointment dressing if used;
- obturation approach;
- complications or deviations;
- images taken;
- coronal seal;
- postoperative instructions;
- review plan.
This guide does not prescribe a technique. The ESE guideline assesses multiple treatment approaches and stresses asepsis, training and reassessment. The provider should explain why its approach is appropriate for the case without claiming that a branded method guarantees success.
If a canal cannot be negotiated, an instrument separates, a perforation or crack is suspected, or another unexpected event occurs, create a new finding and consent record. Do not hide it from the restorative clinician.
Retreatment is not the same as primary treatment
A tooth with previous root canal treatment needs a separate diagnosis. Symptoms, a radiographic finding or planned crown replacement do not automatically prove that retreatment is required.
Ask:
- why the existing treatment is being questioned;
- whether the restoration is leaking or defective;
- whether anatomy may have been untreated;
- whether a crack or periodontal problem is considered;
- whether the tooth remains restorable;
- what records from the first treatment are available;
- which alternative options exist;
- whether referral is indicated;
- what could prevent completion;
- how the final restoration decision changes.
Existing posts, cores, crowns or restorative materials can affect access and structural risk. The endodontic and restorative owners should agree on how access will be created and how the tooth will be resealed.
Do not accept a fixed retreatment success percentage. The outlook depends on personal findings and cannot be reduced to a marketing statistic.
The coronal seal is part of the endodontic pathway
The root-canal stage is not isolated from the restoration above it. Between appointments or before definitive restoration, the tooth needs a documented coronal-seal plan.
Ask the provider to record:
- whether the seal is temporary, provisional or definitive;
- material category;
- remaining tooth structure;
- contact and bite management;
- how long the stage is intended to function without promising a fixed duration;
- dietary or loading instructions;
- signs of loss or fracture;
- who replaces or repairs it;
- what happens if it dislodges during travel;
- how contamination is assessed;
- whether re-disinfection may be needed before progression.
A temporary filling should not be described as a completed combined treatment. A crown preparation should not proceed until the responsible clinicians agree that the endodontic and structural conditions are ready.
Provisional restoration is a decision stage
A provisional restoration can protect the tooth, maintain position, support appearance or allow assessment of function. Its role depends on the case.
The written provisional plan should identify:
- purpose;
- tooth surfaces covered;
- retention strategy;
- material category;
- expected loading limits;
- how margins and contacts are checked;
- how the patient cleans it;
- symptoms that require review;
- who adjusts or replaces it;
- criteria for definitive progression;
- records created before removal.
If there is doubt about symptoms, healing, restorability, gum condition or occlusion, the plan may need a review stage before definitive crown manufacture. That is not a fixed rule; it is a transparency boundary.
A provider should not convert a travel deadline into proof that the provisional stage has answered its clinical questions.
Stage gate C: endodontic completion versus readiness to restore
Endodontic treatment can be recorded as complete while the tooth still needs review before final restoration. Conversely, delaying a protective restoration without a clear reason can expose the tooth to structural or sealing problems.
The gate should answer:
- Is the endodontic procedure complete on the clinician's terms?
- Are there unresolved symptoms or findings?
- Is the coronal seal intact?
- Is the tooth still considered restorable?
- Has the restorative design been reassessed after access?
- Is further disease control needed?
- Is provisional monitoring appropriate?
- Is the patient fit for the next procedure?
- Has consent been updated?
- Has the quotation changed?
The [NHS root canal overview](https://www.nhs.uk/tests-and-treatments/root-canal-treatment/) says a tooth is sealed with a filling and that a crown may be needed in some cases. The word may matters. Readiness and restoration type are clinical decisions, not an automatic calendar step.
Reassess remaining tooth structure after access
The amount of sound tissue can be different from what was estimated before access. Decay, cracks, old material and unsupported structure may become clearer during treatment.
The restorative owner should update the tooth map with:
- remaining walls;
- wall thickness and location where relevant;
- cracks or fracture findings;
- margin feasibility;
- isolation and bonding feasibility;
- periodontal relationship;
- core-retention needs;
- ferrule potential;
- restorative options;
- prognosis uncertainty;
- stop or referral triggers.
The updated map should be shared with the endodontic owner and laboratory. A pre-treatment crown quote should be revised when the structural basis changes.
Core build-up is not just a filler
A core replaces missing coronal structure to support the chosen restoration. The plan should explain why it is needed, how much sound tissue remains and how the core relates to the preparation.
Ask:
- what structure the core replaces;
- material category;
- isolation and bonding conditions;
- retention from remaining walls;
- whether a post is proposed;
- how canal sealing is protected;
- how preparation preserves tissue;
- how margins will be placed;
- whether the core is provisional or definitive;
- what record will be supplied.
Avoid assuming one core material is superior in every case. The ESE restoration statement notes limited comparative evidence for core materials in root-filled teeth restored with crowns. Case factors and technique matter.
A post retains a core; it does not strengthen the root
The word post is often presented as reinforcement. The ESE restoration position statement explains that the purpose of a post is to facilitate core retention; it does not strengthen the root or replace the structural effect of a ferrule. Additional dentine removal solely to place a post should be questioned.
If a post is proposed, request:
- the specific retention problem it solves;
- remaining coronal walls;
- alternative ways to retain the core;
- post-space preparation;
- tooth-structure removal;
- post material category without superiority claims;
- cementation or bonding approach;
- effect on retreatment access;
- perforation or fracture considerations;
- traceability;
- responsible clinician.
If no post is proposed, the plan should still explain how the core is retained. A post should not appear automatically because root canal treatment was performed.
Ferrule is a structural design concept, not a sales word
A ferrule refers to the relationship between remaining tooth structure and the encircling restoration design. The ESE position statement identifies an adequate circumferential ferrule as beneficial where an indirect restoration is planned, while also emphasising preservation of sound structure.
Ask the restorative clinician:
- what sound structure exists above the margin;
- whether it is continuous or interrupted;
- whether margin placement is maintainable;
- what preparation is required to create the planned design;
- whether creating it sacrifices excessive tissue;
- whether periodontal or orthodontic procedures are being considered;
- what alternatives exist;
- how the finding affects restorability.
This guide does not prescribe a measurement or procedure. A ferrule claim should be supported by the personal tooth map and preparation plan.
A crown is not always the only restorative option
Depending on the tooth and remaining structure, the responsible clinician may discuss a direct restoration, onlay, endocrown, partial-coverage restoration, full crown or another design. The ESE position statement supports conservative design and notes that cuspal coverage is not necessary in every root-filled posterior tooth.
Ask each option to be compared on:
- tissue removal;
- ability to seal and protect remaining structure;
- retention and resistance;
- isolation requirements;
- material and bonding demands;
- fit and contact control;
- occlusion;
- repairability;
- laboratory involvement;
- future access;
- maintenance;
- cost and travel consequences.
The answer cannot come from the phrase root canal plus crown. It comes from the post-treatment structural assessment.
Zirconia is one material family, not a universal winner
Zirconia can be considered for some crown designs, but the word alone does not define composition, translucency, strength, surface treatment, design, thickness, connector geometry, finishing or cementation. It also does not prove suitability.
The ESE restoration statement says evidence-based material selection for root-filled teeth is complex and does not support a simple universal hierarchy. Ask the restorative clinician to compare zirconia with reasonable alternatives for the personal tooth.
Decision factors can include:
- anterior or posterior position;
- available restorative space;
- remaining structure;
- preparation design;
- margin location;
- isolation;
- retention;
- aesthetic priority;
- substrate colour;
- opposing material;
- bite and parafunction;
- required bonding or cementation;
- laboratory capability;
- adjustment and polishing;
- repairability;
- future access;
- evidence and uncertainty.
Do not accept phrases such as strongest, best, unbreakable or ideal for every back tooth. A material should be selected after design, not used to predetermine it.
Record the exact zirconia specification if selected
If zirconia is selected after assessment, the personal record should identify it precisely enough for future care.
Request:
- manufacturer;
- product line or material class;
- restoration design;
- shade and characterisation instructions;
- monolithic or layered areas where relevant;
- laboratory identity;
- milling or fabrication route;
- sintering or processing traceability where supplied;
- surface finishing and polishing instructions;
- cementation or bonding system;
- lot or batch information where available;
- statement of conformity or equivalent document where applicable;
- substitution process.
A general website list does not prove which material was used. If a substitute is proposed, the clinician should explain why, obtain consent and update the quotation and record.
Name the laboratory and prescribing clinician
The laboratory fabricates to a prescription; it does not own diagnosis, tooth preparation or final fit.
The laboratory trail should contain:
- legal laboratory identity and location;
- prescribing clinician;
- tooth notation;
- restoration type;
- material specification;
- shade and design instructions;
- scan or impression source;
- file version;
- requested contacts and occlusal scheme;
- change requests;
- remake or adjustment process;
- final conformity and traceability documents.
A named technician in advertising is not evidence of personal involvement. Use only the person and laboratory recorded for the individual case.
If the laboratory changes, document who authorised it, whether the specification changed and whether consent or price changed.
Impression or scan quality needs verification
Digital scanning and conventional impressions are methods, not outcome guarantees. The clinician should decide which is appropriate and verify the resulting record.
Ask:
- whether margins are visible;
- whether moisture and tissue are controlled;
- whether adjacent and opposing teeth are captured;
- whether bite records are usable;
- whether the file or impression was accepted by the laboratory;
- who approves a rescan or new impression;
- how files are named and retained;
- whether the patient can obtain a copy where appropriate.
The word digital should not replace fit verification.
Occlusion belongs in both provisional and final stages
A root-filled tooth with a new restoration functions within a wider bite. The plan should record relevant contacts and any adjustment.
Questions include:
- what contacts existed before treatment;
- whether the tooth was already out of contact;
- whether symptoms relate to biting;
- how the provisional is checked;
- how the final crown is checked in static and functional movements as appropriate;
- how opposing restorations influence material choice;
- whether parafunction is suspected;
- whether a protective appliance is being considered and why;
- who handles a high or uncomfortable contact after travel;
- what record is supplied.
Do not accept claims that a crown will automatically correct the bite, prevent grinding or eliminate jaw symptoms. Those require separate assessment.
Try-in, fit and cementation are clinical gates
Before final placement, the restorative clinician should verify that the restoration corresponds to the prescription and is acceptable clinically.
The record may include:
- identity of tooth and restoration;
- material and laboratory match;
- margin assessment;
- proximal contacts;
- internal fit;
- shade or appearance discussion;
- occlusal contacts;
- surface condition after adjustment;
- patient understanding;
- cementation or bonding protocol;
- final clean-up;
- postoperative instructions;
- images or notes.
If fit, contacts, appearance or function are not acceptable, the plan should allow adjustment, remake or reconsideration. Travel pressure should not force final cementation.
Stage gate D: final restoration or further review
Before definitive placement, ask:
- Is the tooth symptomatically and structurally ready on the treating clinicians' assessment?
- Is the endodontic record complete?
- Is the provisional seal intact?
- Has restorability been reconfirmed?
- Is the core or post decision documented?
- Is the final design conservative and justified?
- Is the material specification final?
- Has the laboratory prescription been verified?
- Are fit and occlusion acceptable?
- Has the patient consented to any changes?
- Are handover and aftercare ready?
If a gate is not met, the options may include further review, provisional care, another opinion, redesign or stopping. The patient should know the clinical and financial consequences.
Warning signs before or after treatment
General information cannot diagnose a complication. The provider should give personalised instructions and current local emergency contacts.
Seek urgent dental assessment for increasing pain, swelling, a lost provisional seal, fracture, new discharge, fever, difficulty opening the mouth, or a deteriorating general condition. Emergency signs vary by jurisdiction. Current [NHS dental abscess guidance](https://www.nhs.uk/conditions/dental-abscess/) directs emergency help for difficulty breathing, speaking or swallowing, significant mouth swelling, eye pain or sudden visual problems.
After a root-canal or crown stage, also contact the treating provider and local dentist for:
- the restoration or temporary coming loose;
- the bite feeling markedly different;
- the tooth or restoration fracturing;
- symptoms returning or worsening;
- swelling or a gum boil;
- an allergic or medication concern;
- inability to clean the area;
- trauma to the tooth.
Do not rely only on photographs if examination is indicated. Health and airway concerns take priority over protecting a travel itinerary or obtaining a remote reply.
When not to travel
Do not travel for elective dental treatment when urgent local assessment is indicated, when the patient is medically unfit, when swelling or systemic illness is worsening, or when a clinician has advised against travel.
A no-travel plan should cover:
- local urgent provider;
- emergency service route;
- records available to local clinicians;
- medication list and allergies;
- insurer notification;
- cancellation or postponement terms;
- remote communication boundary;
- rescheduling only after clinical clearance.
This page does not publish a universal waiting period after treatment. Fitness to fly or travel depends on the procedure, symptoms, medical history, medication, route and clinician's advice.
Travel contingency for staged care
A combined root-canal and crown pathway may change after direct assessment. The tooth may need urgent care, further diagnostic work, a different restoration, a provisional stage, referral, extraction or no elective treatment.
Before booking, write down:
- which decisions are provisional;
- what must be confirmed in person;
- possible stop points;
- who approves progression;
- flexible travel arrangements;
- local-care availability;
- insurance exclusions for planned treatment;
- cost of schedule change;
- record transfer process;
- urgent return plan;
- refund and cancellation terms.
Do not advertise or assume completion within a fixed trip. A clinically justified pause is preferable to an irreversible procedure performed to meet a departure date.

Local handover must be arranged, not assumed
A provider abroad should not assume that a home dentist will maintain or repair the work. Ask a local dentist before travel what care they can offer and which records they require.
The handover should identify:
- diagnosis and treatment summary;
- responsible clinicians;
- images and reports;
- canal anatomy and procedure record;
- obturation and coronal-seal record;
- core and post details;
- preparation and crown design;
- material and laboratory traceability;
- cementation system;
- fit and occlusion notes;
- postoperative instructions;
- review needs;
- urgent-care contact;
- unresolved findings;
- provider-to-provider contact.
A local dentist may choose to assess the tooth without accepting responsibility for the original treatment. Make fees and boundaries explicit.
Aftercare is more than a message channel
Separate:
- immediate postoperative guidance;
- review of endodontic symptoms or healing;
- review of provisional restoration;
- crown fit and occlusal adjustment;
- hygiene and margin maintenance;
- radiographic review when clinically indicated;
- management of recurrent symptoms;
- repair or replacement of the restoration;
- unrelated new disease.
For each category, name the responsible provider, location, contact route, records needed, examination threshold and fee responsibility.
Remote messaging can support triage but cannot confirm healing, diagnose a crack, assess a margin or adjust occlusion. Do not promise unlimited support or instant response. The patient needs a realistic local route.
Records must remain usable after travel
The current [GDC record standard](https://standards.gdc-uk.org/pages/principle4/principle4) identifies complete and accurate records, images, consent, models, laboratory prescriptions and related documents as parts of the patient record for professionals under its jurisdiction. Ask any provider how equivalent records will be created, protected and released.
The patient handover set may include:
- medical and dental history;
- diagnostic findings;
- pulpal and apical diagnosis;
- restorability assessment;
- images and reports;
- consent versions;
- treatment notes;
- isolation and canal-procedure record;
- working-length and obturation records;
- complications or deviations;
- coronal-seal and provisional details;
- residual-structure map;
- core and post details;
- ferrule assessment;
- preparation design;
- laboratory prescription;
- material and batch traceability;
- scan or impression record;
- fit, contact and occlusion notes;
- cementation record;
- prescriptions;
- invoices;
- aftercare and emergency instructions;
- complaint procedure.
Confirm format, release timing, data controller and secure transfer route before treatment.
Build the itemised quotation around clinical gates
A combined total hides whether the root canal, provisional restoration, core, post, crown, laboratory work, records and aftercare are actually included.
Use a worksheet:
| Quote line | Detail required |
|---|---|
| Assessment | Examination status, records reviewed and diagnosis boundary |
| Imaging | Modality only if justified, interpretation and copies |
| Endodontic treatment | Primary, retreatment or other scope; responsible clinician |
| Isolation or pre-endodontic build-up | Included purpose and material category |
| Interim dressing | Trigger and follow-up responsibility |
| Coronal seal | Temporary, provisional or definitive status |
| Core | Material category and retention approach |
| Post | Indication, material status and traceability |
| Provisional restoration | Purpose, adjustments and replacement boundary |
| Tooth preparation | Design and preservation boundary |
| Final restoration | Crown, onlay, endocrown, direct restoration or other selected option |
| Material | Case-specific specification, not a website promise |
| Laboratory | Identity, prescription and conformity record |
| Fit and cementation | Try-in, adjustments and final placement |
| Records | Images, procedure notes and handover files |
| Aftercare | Routine review, urgent assessment and local interface |
| Conditional work | Trigger, alternative, consent and price effect |
| Travel change | Patient-owned exposure and cancellation terms |
A blank should be marked as excluded, undecided, not applicable or awaiting assessment. Do not assume included.
Make exclusions and change triggers explicit
Ask whether the quotation excludes:
- specialist referral;
- additional images;
- management of acute infection;
- retreatment;
- removal of an existing crown, core or post;
- repair of perforation or resorption;
- crack assessment;
- pre-endodontic build-up;
- temporary seal replacement;
- core;
- post;
- provisional crown;
- alternative final restoration;
- laboratory remake;
- occlusal adjustment after return;
- medication;
- local review;
- emergency treatment;
- extraction;
- replacement after extraction;
- record copies;
- travel changes.
For each conditional item, record:
- finding that triggers it;
- responsible clinician;
- alternatives;
- itemised financial effect;
- sequence effect;
- travel effect;
- consent requirement;
- right to pause.
Do not accept a broad complication fee or promise that every remedy is included.
Payment and provider identity must align
The person receiving payment should appear in the treatment contract or have a documented legal role. Request:
- legal payee;
- invoice currency;
- payment stage;
- deposit purpose;
- cancellation and refund terms;
- change-control process;
- card or bank charges;
- dispute process;
- receipt.
Do not send payment to an unnamed individual because a coordinator requests it. Do not accept pressure based on expiring material, laboratory or travel availability.
Complaints and remedy require a real pathway
Before payment, obtain:
- provider complaints contact;
- accepted language;
- acknowledgement and review process;
- clinical records required;
- external professional or facility route;
- governing law and jurisdiction;
- payment dispute route;
- available outcomes and exclusions.
A professional regulator, facility authority, insurer, payment provider and court can have different roles. A regulator may investigate conduct without awarding the remedy sought. Seek independent legal advice when jurisdiction or rights matter.
Keep plan versions, consent, images, procedure notes, laboratory traceability, invoices and communication. If health is at risk, seek clinical care before pursuing a complaint.
Red flags
- Root canal treatment is recommended without a documented diagnosis.
- The tooth is assumed restorable without structural assessment.
- A crown is described as mandatory for every root-filled tooth.
- Zirconia is called universally strongest, best or permanent.
- A provider blames tooth brittleness only on loss of pulp moisture.
- Extraction and no-treatment consequences are not discussed.
- The endodontic and restorative owners are unnamed.
- Rubber dam isolation is absent or dismissed.
- Brand names replace an aseptic procedure record.
- A microscope is presented as an outcome guarantee.
- A post is sold as strengthening the root.
- The ferrule claim has no residual-structure record.
- The crown is manufactured before restorability is reconfirmed.
- The provisional seal has no failure plan.
- Material specification appears only in marketing.
- The laboratory identity and prescription are missing.
- Fit and occlusion are not documented.
- A changed finding produces no revised consent or quote.
- Completion is promised around a fixed departure date.
- Urgent swelling is managed only by messaging.
- A local dentist's participation is assumed.
- Aftercare is reduced to a warranty statement.
- Records are withheld until a dispute.
- Payment goes to an unrelated person.
- A fixed outcome, lifespan or comfort claim is used to close the sale.
A patient-led sequencing workflow
Verify identity
Record the legal provider, endodontic owner, restorative owner, imaging interpreter, laboratory, payee, aftercare owner and complaints contact.
Stabilise urgent needs
Use local urgent or emergency services when indicated. Do not delay care for travel.
Confirm diagnosis
Obtain the pulpal and apical diagnosis, relevant tests, images, uncertainty and alternatives.
Confirm restorability
Map remaining structure, cracks, periodontal conditions, isolation, margin feasibility, loading and maintenance.
Compare options
Discuss no treatment, tooth-preserving endodontic options, retreatment where relevant, extraction and restoration alternatives.
Approve the endodontic stage
Version consent, verify isolation, record the clinical procedure and establish the coronal seal.
Reassess after access
Update residual structure, restorability, core, post, ferrule and restoration design.
Use provisional care where indicated
State purpose, failure signs, adjustment owner and criteria for progression.
Select material after design
Compare zirconia and reasonable alternatives without blanket superiority. Record the exact selected specification.
Verify laboratory and fit
Match prescription, material, margins, contacts, appearance, occlusion and cementation.
Complete handover
Release the diagnostic, endodontic, restorative, laboratory and aftercare record set.
Maintain a local route
Arrange routine and urgent assessment without assuming remote messages are enough.
Final checklist
- The legal healthcare provider is identified.
- The endodontic and restorative owners are named.
- Diagnosis is documented before treatment.
- Restorability is assessed separately.
- Reasonable alternatives include extraction and no treatment where relevant.
- Imaging is justified and interpreted.
- Consent is versioned across both stages.
- Urgent warning signs and local routes are understood.
- Rubber-dam isolation is documented.
- The endodontic procedure record is complete.
- Retreatment is distinguished from primary treatment.
- The coronal seal has an owner and failure plan.
- Residual tooth structure is reassessed after access.
- Core and post decisions are justified.
- A post is not presented as strengthening the root.
- Ferrule is linked to the personal structure map.
- Full crown need is not assumed.
- Zirconia is compared with reasonable alternatives.
- The selected material and laboratory are traceable.
- Impression or scan quality is verified.
- Fit, contacts and occlusion are documented.
- Final placement is not controlled by departure time.
- The quotation maps to stages and exclusions.
- Conditional work has triggers and consent.
- Records are ready for local handover.
- Routine and urgent aftercare have named owners.
- No-travel and emergency plans exist.
- Complaints, governing law and payment routes are clear.
- No decision relies on fixed price, time, outcome, lifespan, comfort or remedy promises.
The responsible combined plan
A responsible root canal and crown pathway does not begin with a zirconia package. It begins with diagnosis, restorability and a tooth-preservation decision. It names the endodontic and restorative owners, protects the tooth between stages, reassesses structure after access, uses a post only for a documented retention need, treats ferrule as a design question, and selects crown material after the restoration is defined.
The strongest plan makes uncertainty visible. It allows treatment to stop when urgent care, new findings or travel safety require it. It leaves the patient with traceable records and a realistic local pathway rather than a fixed promise.