Start with the exact product, not the family name
Geistlich Bio-Gide is a name used within a family of collagen barrier membranes for oral and maxillofacial regenerative procedures. It is not a diagnosis, a bone graft, an implant, a promise of bone formation or a complete surgical plan. A quotation that says only Bio-Gide leaves open which product, dimensions, reference, market document and clinical design are proposed.
The official Geistlich catalogue currently presents several related names, including Bio-Gide, Bio-Gide Compressed, Bio-Gide Perio, Bio-Gide Shape and Bio-Gide Forte, as well as combination presentations. The names are not interchangeable. They can differ in form, handling, intended clinical context, presentation and applicable instruction. A clinician or seller should not borrow an indication or handling statement from one line to support another without checking the exact current documentation.
This page is a neutral verification and decision guide. It does not state that WeCare, any clinic, intermediary, laboratory or event clinician stocks, uses, supplies or is authorised for Geistlich products. It does not select a membrane for any patient, endorse guided bone regeneration, publish a performance percentage, promise comfort, set a universal recovery schedule or predict an outcome. Those decisions require direct diagnosis, current product documents and named professional responsibility.
The defensible sequence is diagnosis first, alternatives second, exact product third and surgical design fourth. Product evidence should then remain connected to sterile handling, graft identity, fixation, closure, records, costs, aftercare and a plan for complications.
Distinguish Bio-Gide variants and presentations
Ask for the exact trade name as printed on the box and sterile blister. Bio-Gide without a qualifier should not silently become Bio-Gide Compressed, Bio-Gide Perio, Bio-Gide Shape, Bio-Gide Forte or a membrane supplied inside a combination kit. The current manufacturer website is useful for seeing that these lines exist, but the box reference and product-specific instruction determine what is actually proposed.
The [official UK Bio-Gide product page](https://www.geistlich.com/en-gb/dental-professionals/products/membranes/bio-gide) currently displays standard Bio-Gide presentations labelled 13 × 25 mm, 25 × 25 mm and 30 × 40 mm. An accessible manufacturer instruction also lists those standard presentations while separately naming Compressed and Perio forms. These dimensions are an identification aid, not proof that every size is registered, supplied or suitable in Turkey, Great Britain or another market at the time of treatment.
A product schedule should capture:
| Identity field | What to retain |
|---|---|
| Full trade name | Exact wording from the sterile label |
| REF or re-order number | Manufacturer identifier used to retrieve the eIFU |
| Dimensions or shape | Labelled size or preformed presentation |
| Batch or lot | Case-linked batch code |
| Expiry | Use-by information visible before opening |
| Sterile status | Intact sterile-barrier record before use |
| Manufacturer | Legal manufacturer on the applicable label |
| Market document | Current eIFU language, revision and jurisdiction |
| Surgical site | Tooth, implant or ridge location where placed |
A website image, empty outer carton or certificate created by a clinic does not provide the full chain. The record must connect the specific sterile item to the specific patient and site.
Retrieve the current eIFU by reference
The [Geistlich electronic instructions page](https://www.geistlich.com/en-gb/dental-professionals/professionals/e-ifu) directs users to enter the REF or re-order number from the product box or blister and choose the relevant language. That process is more reliable than searching the product name and opening the first PDF found online. Similar names, older revisions and country-specific files can otherwise be confused.
An accessible manufacturer PDF for Bio-Gide, Bio-Gide Compressed and Bio-Gide Perio identifies document DOC-2958, Revision 06, and includes composition, intended use, indications, handling, contraindications, precautions, adverse effects, sterile-barrier symbols and presentations. It is useful evidence of how a particular revision describes those products. It should not be described as the permanent or universally current instruction. For a new case, the responsible professional should retrieve the document that matches the exact REF, market, language and date from the live eIFU system.
Record the document title, product scope, revision and retrieval date. Read the intended use, indications, contraindications, warnings, precautions, single-use status, sterile handling, storage, orientation, fixation, interaction limitations and post-operative instructions that apply. If the label and eIFU do not match, pause before opening the sterile pack and ask the manufacturer or lawful supplier to resolve the discrepancy.
Product pages, instructions and studies answer different questions
A manufacturer product page introduces the commercial range and may summarise handling or research. An eIFU sets product-specific use and safety information for the relevant market. A regulatory database concerns market actors, device identity or registration within its jurisdiction. A clinical study addresses a defined population, procedure and outcome. None can substitute for the others.
Marketing phrases such as reliable, natural, easy or proven should not be copied into personal treatment promises. A manufacturer-sponsored study, data-on-file reference or clinician quotation requires different weighting from an independent systematic review. Evidence involving Bio-Gide with a particular graft, defect and protocol cannot automatically support Bio-Gide alone, a different variant, a different defect or a different closure strategy.
For every claim in a proposal, ask four questions: What exact product was studied? What procedure and comparator were used? Which patient and defect characteristics were included? Does the current case match closely enough for the information to matter? If the answer is unclear, treat the claim as background rather than a prediction.
CE marking and registration are jurisdiction specific
A CE mark is not an international approval badge and does not certify the treating clinic. It concerns conformity for the applicable European device framework and the product covered by the relevant documentation. It does not by itself prove that the item was lawfully placed on the Turkish market, registered for Great Britain, supplied through an authorised route, selected correctly or used in accordance with its instruction.
The European Commission explains the EU device identification framework through its [EUDAMED UDI and device-registration information](https://health.ec.europa.eu/medical-devices-eudamed/udidevice-registration_en). Great Britain has a separate manufacturer and device-registration framework described by the [MHRA registration guidance](https://www.gov.uk/guidance/register-medical-devices-to-place-on-the-market), with public records presented through its registration database. Turkey has its own product-tracking environment, including the [Ürün Takip Sistemi public medical-device search](https://utsuygulama.saglik.gov.tr/UTS/vatandas#/vatTibbiCihazListele).
Use the database relevant to where the device is placed on the market and used. Search by the strongest identifiers available: legal manufacturer, trade name, REF, UDI where applicable and responsible economic operator. A database entry can support identity or market status; it cannot prove that the labelled item in one surgery came through that route. A missing search result also requires careful interpretation because public systems, transition rules, naming and data completeness change.
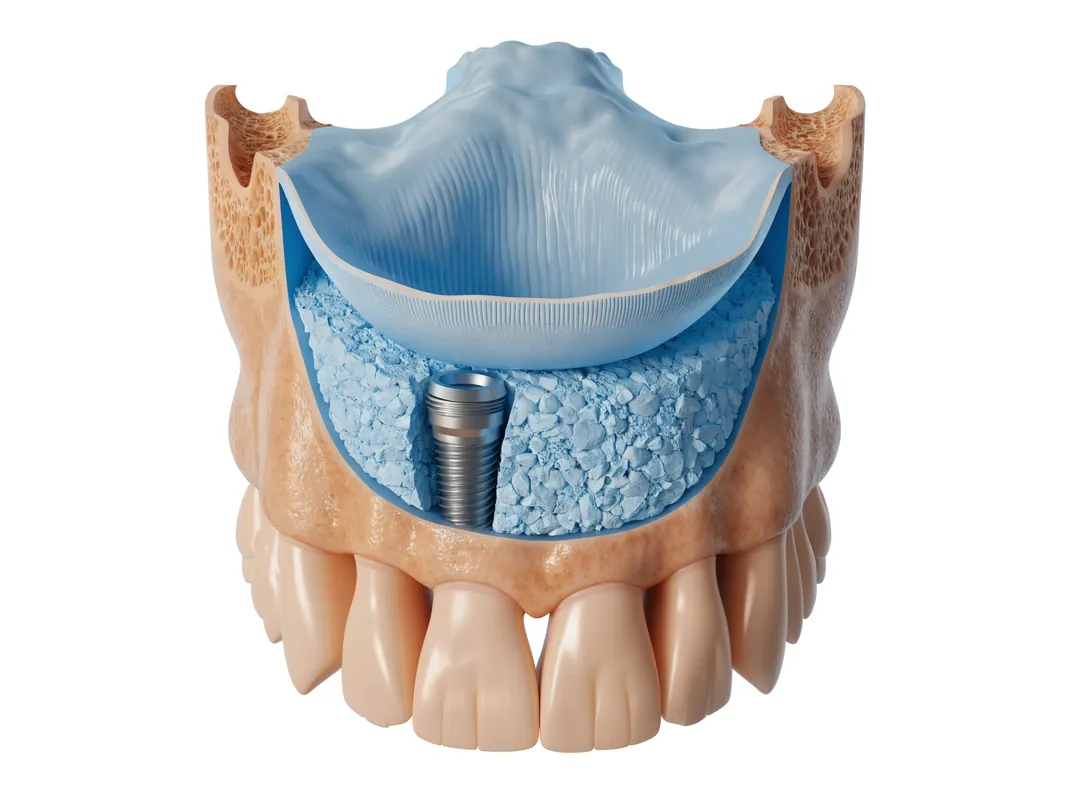
The membrane is not the graft
A barrier membrane is used to separate and protect a regenerative space under a defined surgical design. A bone-substitute material, autogenous bone, allograft, xenograft, synthetic material or mixture placed beneath it is a separate product or tissue decision. Fixation pins, tacks, screws, meshes, sutures, implants and medicines are separate again.
The Bio-Gide name does not identify what fills the defect. It does not establish that a filler is required, that a particular graft is compatible, that autogenous bone will or will not be harvested, or that the membrane can maintain space without another structure. Ask for a component map naming every material, manufacturer, reference, lot, source and site where relevant.
A combination presentation should also be unpacked. If a kit contains a membrane and a separately named bone substitute, each component retains its own composition, instruction, lot and clinical role. The quote should not merge them into one branded regeneration material. The patient may accept one component and decline another because source, risk, evidence or alternatives differ.
Diagnose the defect before discussing GBR
Guided bone regeneration is a procedure concept, not a diagnosis. The plan should describe what is missing, why it matters and how it was measured. Possible contexts include an extraction socket, local ridge deficiency, implant dehiscence or fenestration, staged ridge augmentation, periodontal intrabony defect or another hard- or soft-tissue problem. Those contexts are not interchangeable.
The assessment can include medical and dental history, periodontal examination, tooth and implant prognosis, clinical photographs, appropriate two- or three-dimensional imaging, soft-tissue evaluation, occlusion, restorative plan and the patient's ability to maintain the site. Imaging should be justified by the question rather than ordered simply because grafting is marketed.
For implant-related care, the restorative endpoint should guide the bone plan. Implant position, emergence, prosthetic space and hygiene access are relevant before choosing a membrane. The not-enough-bone implant guide explains why insufficient bone has several possible responses, while the implant planning guide places grafting within the wider diagnostic pathway.
Ask whether regeneration is necessary at all
The reasonable alternatives depend on the diagnosis. They may include monitoring, no immediate treatment, preserving a tooth, accepting a ridge contour, a removable prosthesis, a tooth-supported restoration, changing implant position or number, using a different implant dimension within its legitimate indication, staged treatment, another regenerative design or referral for local specialist assessment. This is a question list, not a recommendation that any alternative fits.
The clinician should explain what clinical or restorative objective the proposed regeneration serves and what happens if it is not performed. Avoid statements that every implant needs a graft or that a branded membrane makes grafting minimal. A less extensive procedure can have different compromises; a more extensive procedure can introduce additional morbidity, cost and aftercare.
Consent should document the option of not proceeding where relevant. It should also separate preserving anatomy after extraction from creating volume for a future implant, because the benefit, uncertainty and timing decisions may differ. When the definitive need cannot be established from remote records, the quote should label the membrane and graft as provisional rather than prepaid certainty.
Map defect anatomy and blood supply
Regenerative design depends on three-dimensional anatomy. Record the site, number of remaining bony walls, horizontal and vertical component, contained or non-contained form, neighbouring roots or implants, vital structures, cortical and cancellous features, soft-tissue thickness, scar or previous surgery, flap access and available blood supply. A broad small, medium or large label is not a surgical map.
A contained defect can provide different support from an open ridge deficiency. A vertical component can impose different stability and closure demands from a limited contour defect. A socket with an intact wall is not the same as one with a missing wall. Periodontal defects also depend on tooth prognosis, root anatomy, mobility, furcation, plaque control and the pattern of attachment loss.
The prescription should show how the chosen membrane dimensions permit trimming and coverage under the applicable instruction without creating folds or impingement. If the defect is too extensive for the proposed presentation or requires another space-maintaining structure, that should be recognised before opening the product.
Soft tissue and closure are part of the plan
The membrane sits beneath living soft tissue, so flap design, tissue quality, vascularity, thickness, mobilisation, wound-edge position and closure tension matter. The product name cannot compensate for inadequate soft tissue or an unstable wound. Previous scars, thin tissue, inflammation, anatomical attachments and the need for future restorative access can change the design.
Ask whether primary closure is intended, whether open healing is contemplated for a product and indication that permit it, and what evidence supports that choice. Do not transfer an open-healing statement from a preformed extraction-socket product to standard Bio-Gide or another site without checking the exact current instruction and case. The plan should describe what happens if the flap cannot close as intended.
Suture choice and wound support should be documented separately from the membrane. The patient should receive instructions for protecting the site, maintaining permitted hygiene and contacting the surgical team. A statement that the membrane resorbs does not mean it can be ignored if exposed or infected.
Intended use is not personal suitability
The accessible manufacturer instruction describes the referenced Bio-Gide products for hard- and soft-tissue defects in oral and maxillofacial surgery and lists broad clinical conditions. That is a manufacturer-defined boundary. It does not establish that a specific person, defect, graft combination or surgical technique is suitable.
The clinician still needs to assess active infection, periodontal stability, metabolic disease, medicines, immune conditions, previous radiotherapy, smoking, wound-healing capacity, allergy, pregnancy or lactation considerations, oral hygiene, ability to attend review and reasonable alternatives. The exact current eIFU governs which cautions apply; the medical history determines their relevance.
If the proposed use falls outside the current instruction, the clinician should disclose that fact, explain the evidence and alternatives, and document the legal and professional basis. A patient should not discover after surgery that the product was used in a materially different way from the written proposal.

Porcine collagen requires informed discussion
The accessible manufacturer instruction describes the collagen in Bio-Gide, Bio-Gide Compressed and Bio-Gide Perio as derived from veterinary-certified pigs and purified through controlled manufacturing. The source is clinically relevant because a known collagen allergy is listed as a contraindication in that instruction and allergic reactions are described as possible. Source can also matter for personal, ethical, cultural or religious reasons.
The clinician should ask about known reactions to collagen or animal-derived medical products and explain uncertainty without dismissing a patient's concern. Dietary rules and implanted medical materials are not necessarily treated identically within every belief system; the patient may wish to consult a trusted adviser. That choice deserves time before the pack is opened.
The label and current eIFU, not an assumption based on the word natural, should establish composition. If a patient declines porcine collagen, reasonable alternatives and their different handling, removal, evidence and complication questions should be discussed. No substitute should be presented as identical merely because it is also resorbable.
Medical history and healing capacity
Regenerative surgery should not begin with a product order. The history should cover diagnoses, operations, allergies, current medicines and supplements, anticoagulant or antiplatelet use, diabetes and metabolic control, immune conditions, bone-related medicines, corticosteroids, cancer treatment or radiotherapy, pregnancy or lactation, tobacco or nicotine use, alcohol and previous wound-healing problems. This is not a complete medical screen.
The accessible eIFU lists several circumstances requiring particular caution and says that some clinical conditions or medicines can negatively influence tissue healing. A caution does not automatically prohibit treatment, and the absence of a named caution does not make treatment safe. The responsible clinician must relate the complete history to the planned operation and coordinate with relevant medical professionals when needed.
The patient should know which findings could cancel, defer or modify surgery. If medical clarification is outstanding, the written plan should state that the membrane and graft choice remain provisional. Travel and hotel reservations should not pressure the team to proceed before those questions are resolved.
Control acute infection and stabilise periodontal disease
The accessible manufacturer instruction lists acutely infected wounds as a contraindication and calls for special caution with chronic infection at the surgical site, including periodontitis. A membrane must not be marketed as a way to seal infection beneath a flap. Diagnosis, source control and a stable environment come first.
For periodontal regeneration, document plaque control, bleeding, probing findings, tooth prognosis, mobility, furcation where relevant, endodontic status and completion of the non-surgical phase. The instruction emphasises control of underlying bacterial infection and adequate oral hygiene before periodontal surgery, with continuing maintenance afterward. The implant-after-gum-disease guide explains why disease control and maintenance remain distinct from implant or graft selection.
For an extraction or implant site, identify any acute swelling, suppuration, sinus tract, untreated endodontic lesion, peri-implant infection or retained pathology. Antibiotics do not substitute for diagnosis and source control, and this page does not prescribe a medicine. If the status changes between remote review and surgery, reassess the regenerative plan and renew consent.
Smoking, nicotine and modifiable risk factors
The accessible eIFU identifies heavy smoking as a circumstance requiring special caution. Independent evidence also matters: a [systematic review on smoking and periodontal bone regeneration](https://pubmed.ncbi.nlm.nih.gov/21627463/) found less favourable regenerative findings among smokers in the studies it analysed. That evidence does not supply an individual percentage or define a universal safe threshold.
Record combustible tobacco, vaping, nicotine replacement, smokeless products and frequency rather than asking only whether the patient smokes. The clinician should explain how nicotine exposure and smoking can affect vascularity, wound healing, infection risk and maintenance, while being honest about evidence limits for newer products and specific protocols.
Other modifiable factors can include plaque control, glycaemic management, nutrition, trauma to the site and adherence to post-operative restrictions. Risk-factor work should be supportive, not punitive. If a clinician sets a condition for proceeding, it should be clinically justified, measurable and documented without promising that compliance guarantees regeneration.
Check sterile barrier, expiry and storage before opening
The product record begins before the membrane touches the surgical field. Ask the team to verify the legal manufacturer, full trade name, REF, dimensions, batch or lot, use-by date, package integrity and storage conditions against the current label and eIFU. The accessible instruction describes sterile double-blister presentations, irradiation sterilisation, single-patient use and precautions against use when packaging is damaged or unintentionally opened.
The outer carton alone is not the sterile barrier. A photograph should show relevant identifiers without compromising asepsis or exposing another patient's information. Storage should follow the exact labelled temperature, dryness and light conditions; a clinic shelf or delivery receipt does not prove the complete storage history.
Do not use an expired, damaged, previously opened, reused or resterilised item. If a pack is rejected, record why and capture the identifiers of the replacement. Unused membrane from an opened primary package should not be saved for another patient merely to reduce cost.
Preserve a sterile chain of custody
Traceability should show who received the product, where it was stored, who selected it for the case, who checked the label, when the sterile barrier was opened and which site received it. If an intermediary, hospital, external surgical centre or supplier is involved, the legal handoffs should be clear. A branded delivery box does not establish an authorised supply chain.
The operating record can include a label sticker or readable digital copy, batch, REF, dimensions, expiry, opening time or procedure date, responsible clinician and site. Any unused or discarded portion should be documented according to product and clinical-waste requirements. If two membranes are used, both identifiers and locations belong in the record.
Patient data and commercial records can be shared proportionately. The patient does not need another person's invoice or confidential supplier agreement, but should receive enough case-specific information for later recall, vigilance, allergy, complication or re-operation questions.
Orientation and handling are product specific
The accessible instruction describes a bilayer structure with a porous and a dense surface and gives orientation guidance for the referenced products. It also explains that the membrane can be trimmed and adapted. The current exact-product eIFU controls which side faces the defect, which side faces soft tissue, whether the product is applied dry or otherwise prepared, and whether any markings identify orientation.
The surgical record should state the exact variant and confirm that orientation and handling followed its instruction. This matters because not every membrane family has the same surfaces or preparation. A social-media video showing one product is not a validated technique for another.
Avoid contaminating the membrane with unstudied substances. The accessible instruction notes limits in evidence for local use with certain medicinal products, alcohol, disinfectants or antibiotics. If the team applies another agent, the clinician should identify it, explain the evidence and record the decision rather than treating it as an invisible routine step.
Coverage, adaptation and margins need a design
The membrane should be planned against the measured defect, not cut by eye after an unspecified graft has been placed. The design should show how the barrier covers the intended defect, contacts appropriate bone, avoids unstable folds and remains clear of structures that could compromise tissue or future restoration. Current product instructions may state overlap or adaptation requirements; apply the exact document rather than copying a number from an older brochure.
The chosen size should allow the intended design after trimming. A larger sheet is not automatically safer, because unnecessary extension can complicate adaptation and closure. A smaller sheet is not economical if it cannot cover the planned margins. Where several pieces are proposed, document how their relationship and stability are managed.
Photographs or diagrams in the surgical plan can help later review, but they do not replace intraoperative judgement. If the actual defect differs materially from imaging, the surgeon should reassess the product, graft, fixation and closure rather than forcing the pre-purchased membrane into the original plan.
Space maintenance and fixation are separate questions
A resorbable collagen membrane is a barrier; it is not automatically a rigid tent. Space maintenance can depend on defect walls, graft particles, autogenous bone, tenting screws, pins, mesh, implant position, soft-tissue pressure and flap design. The plan should explain what prevents collapse into the intended regenerative space.
The accessible eIFU says fixation with sutures or pins is possible. It does not mean fixation is always necessary or never necessary. Ask how the clinician decided, which fixation device is proposed, how it will be positioned, whether removal is expected, and what happens if stability is lost. Each pin, tack, screw or mesh needs its own manufacturer, reference and lot where applicable.
Fixation choice also affects future imaging, retrieval and local aftercare. If metal hardware remains, record its site and identity. If no fixation is planned, the design should explain how the membrane and graft remain stable. Neither route should be promoted as universally simpler.
Name every graft material separately
The quotation should list the membrane and graft on separate lines. For the graft, record whether it is autogenous, allogeneic, xenogeneic, synthetic or a mixture; legal manufacturer and trade name; source material; particle or block form; size and quantity where relevant; REF and lot; and the sites from which autogenous material is harvested. One word such as natural, Swiss or synthetic is not a complete description.
The current instruction for each graft governs preparation and use. Compatibility should be assessed for the exact combination and defect. Evidence for Bio-Gide used with one named graft cannot prove equivalence with another. If autogenous bone is mixed in, donor-site risks and consent require separate discussion.
The patient may have ethical, religious or allergy questions about both membrane and graft. A porcine collagen membrane paired with a bovine-derived graft involves two different sources. The team should not answer a question about one component with a leaflet for the other.
Combination kits still contain separate devices
Geistlich markets combination presentations that place a Bio-Gide-family membrane and a separately named graft product in one commercial kit. Commercial packaging can simplify procurement, but it does not merge the products' functions, indications, contraindications, source materials or records.
For a combination presentation, record the kit REF and lot as well as the component identities and applicable instructions. Confirm that the exact membrane dimensions and graft quantity fit the diagnosed defect rather than assuming the kit defines the treatment. If an additional graft or second membrane is opened, add those identifiers separately.
A kit price should not become a fixed clinical package. Imaging, anaesthesia, surgery, fixation, implant placement, provisional restoration, review and complication care are distinct services. Consent remains free to accept or decline the proposed components, and a changed diagnosis may require a different plan.
Closure failure, dehiscence and membrane exposure
Wound dehiscence or membrane exposure is a clinical event, not merely an aesthetic inconvenience. It can involve contamination, inflammation, infection, loss of graft particles, altered tissue healing or a need for additional care. Management depends on location, size, timing, product, graft, symptoms, tissue condition and clinician assessment; a universal home remedy is unsafe.
An independent [systematic review and meta-analysis of membrane exposure](https://pubmed.ncbi.nlm.nih.gov/29368353/) found less favourable regenerative findings at exposed sites in the included studies. That evidence supports taking exposure seriously, but it does not predict the result of one Bio-Gide case or prove that every exposed membrane should be removed.
The consent form should explain exposure and dehiscence as possible complications, state whom to contact, and distinguish observation, hygiene measures, medication, local care, surgical intervention or removal as clinician-led possibilities. If exposure occurs after the patient has travelled home, a local dentist or surgical service should assess it rather than relying only on photographs.

Infection and complication boundaries
Possible problems after regenerative surgery can include bleeding, swelling, pain, bruising, flap injury, tissue necrosis, infection, wound opening, membrane exposure, graft loss, altered sensation, injury to nearby structures, failure to obtain the intended volume, harm to a tooth or implant, and a need to revise or abandon the plan. This is not a personalised risk list; the clinician should tailor consent to the site and procedure.
The accessible manufacturer instruction describes possible surgery-related adverse effects and notes that a collagen product can cause allergic reactions. The team should explain how suspected allergy differs from ordinary post-operative inflammation and how urgent assessment will be obtained.
Do not turn the word resorbable into no-removal-needed under every circumstance. The accessible instruction notes that removal may be possible during surgery but may become incomplete after tissue integration. A clinician must decide whether and how to intervene when complications occur.
Urgent signs require local assessment
Patients should receive written normal-postoperative guidance and clear escalation thresholds. Increasing or spreading swelling, pus or a bad taste, fever or systemic illness, uncontrolled bleeding, worsening pain, wound opening, visible material, persistent numbness, rash or breathing symptoms deserve prompt professional assessment. The exact urgency depends on severity and associated features.
The [NHS dental-abscess guidance](https://www.nhs.uk/conditions/dental-abscess/) advises emergency action for difficulty breathing, speaking or swallowing, major mouth swelling, serious eye symptoms or marked difficulty opening the mouth. Those signs should not wait for a reply from an overseas messaging account or a return flight.
A local clinician may need the operation note, product labels, graft and fixation details, medication record and current images. The overseas surgical team should remain contactable, but remote advice is not a substitute for examination when airway, infection, bleeding, nerve or wound concerns exist.
Build a case-specific record bundle
The final record should allow another qualified professional to understand what was diagnosed, what was placed, why it was chosen and how to respond later. Request the medical and dental history, examination, periodontal chart where relevant, justified imaging and reports, diagnosis, alternatives, consent, operation note, membrane and graft labels, fixation and implant records, medication record, review findings and aftercare plan.
For Bio-Gide, retain the full product name, REF, dimensions, lot, expiry, sterile-barrier check, eIFU revision and surgical site. If a patient implant card or manufacturer information card is supplied for the presentation, check it against the label and keep both. A card is a portability tool, not proof of correct technique.
Documents should distinguish proposed, opened, implanted, discarded and substituted products. A preoperative quote shows intention; the operative record shows what happened. If a pack was opened but not used, that distinction matters for both traceability and billing.
Chain of custody supports authenticity, not outcome
Authenticity is stronger when independent records agree: manufacturer product listing, exact sterile label, lawful supplier invoice or receipt, clinic stock record, case assignment, opening record, operation note and patient handover. A logo or a photograph of a Bio-Gide box in a storeroom cannot link that product to one patient.
If the REF, lot, dimensions or manufacturer details conflict across records, resolve the discrepancy before surgery or fitting the next treatment stage. The lawful supplier or manufacturer can help check whether an identifier format is plausible, but should not be asked to decide personal suitability.
Traceability cannot prove that the membrane was oriented, adapted, fixed or covered correctly. It also cannot predict regeneration. It establishes which product was involved and supports recall, vigilance, adverse-event investigation and future clinical decisions.
Use an itemised quotation
The quote should separate diagnosis and imaging, periodontal or infection control, membrane, graft, autogenous donor procedure, fixation hardware, implant components, anaesthesia or sedation, surgery, provisional work, laboratory services, reviews, removal of hardware where planned and management of complications. Each material line should carry the proposed identity or state that selection remains provisional.
State the currency, payment stages, cancellation and refund terms, the consequence of a changed diagnosis, and which services are excluded. Travel, accommodation and transfers should be separate from clinical and material fees so comparisons remain meaningful. An included logistical item is not evidence that surgery is suitable or complete.
The quote should explain whether an unused product is charged, who pays for additional material when the defect differs from the estimate, and how a decision not to graft affects the total. Do not accept one bone graft price that hides the membrane, graft, fixation and professional work.
Keep remote estimates provisional
Photographs, panoramic images, CBCT data and records can support preliminary discussion, but anatomy, active infection, soft tissue, mobility, probing findings and surgical access may change the plan after direct examination. The proposal should label which decisions are provisional and which evidence is still required.
Possible changes include no graft, another membrane size or variant, another graft, added autogenous bone, fixation, staged surgery, treatment of infection, tooth preservation, referral or stopping. The clinician should explain each material change, alternatives, additional risks and costs before irreversible work continues.
An itinerary is not clinical evidence. Do not pre-authorise substitutions simply because a return flight is booked. Valid consent requires a genuine opportunity to ask questions, consider changed information and decline.
Plan travel around clinical uncertainty
Cross-border regenerative surgery requires more than choosing flight dates. Before travel, obtain an initial written assessment, named treating provider, provisional diagnosis, proposed records, regulator and complaint information, current cost structure and a plan for findings that change treatment. The [GDC guidance on dental treatment abroad](https://www.gdc-uk.org/standards-guidance/information-for-patients-public/going-abroad-for-dental-treatment) advises patients to research regulation, assessment, qualifications, aftercare, complications and complaints and to speak with their own dentist.
The visit must allow direct assessment, informed consent, safe surgery if indicated, review and correction based on clinical need. This guide does not publish a universal number of days or visits. Large, infected, staged or medically complex defects can require a different pathway from a limited site.
Check travel insurance exclusions for planned dental treatment and complications. Identify where urgent dental and hospital care can be accessed both abroad and at home. A promise that a coordinator is reachable does not replace a clinical emergency route.
Arrange local aftercare before leaving
Ask a local dentist or relevant specialist whether they are willing to review the site and which records they require. A UK clinician is not automatically responsible for overseas treatment and may not agree to manage an unfamiliar product or surgical design. Early contact allows gaps in records to be found before travel.
The handover should state the procedure, sites, exact membrane, graft and fixation products, implants if any, medicines, sutures or hardware, complications, permitted hygiene, dietary or activity instructions, review objectives and contact details. It should explain which findings require ordinary review and which require urgent assessment without using a fixed universal schedule.
The returning-home guide provides a broader record checklist. It does not certify the overseas plan or require a UK clinician to accept care.
Maintenance extends beyond membrane resorption
Even when a collagen membrane is intended to resorb, the supporting teeth, implants, regenerated site and periodontal condition need ongoing assessment. Maintenance can include plaque control, periodontal monitoring, implant probing where appropriate, radiographs when justified, restorative review and management of smoking or metabolic risks. The personal plan depends on diagnosis.
Do not frame membrane resorption as the end of responsibility. Infection, tissue recession, progressive periodontal disease, implant complications or inadequate volume can become apparent later. Future clinicians need baseline images and records to interpret change.
If the surgery was intended to support later implant placement or restoration, the next decision requires new assessment of the healed site. The membrane brand cannot predetermine that the next stage will proceed.
Consent should separate product and procedure
Consent should cover why regeneration is proposed, reasonable alternatives including no surgery where relevant, the exact or provisional membrane, animal origin, graft and fixation materials, surgical steps, uncertainties, material risks, financial terms, follow-up and what happens if the plan changes. It is a conversation, not a signature collected immediately before surgery.
A patient may accept a surgical objective but decline porcine material, a graft source, donor-site harvesting or a staged route. Those choices should be explored without pressure. Translation or independent interpretation should be arranged when needed; a sales coordinator should not be the sole source for complex consent.
If the product, graft, fixation, site or procedure changes materially, renew the discussion and document the decision. A generic consent for bone grafting does not authorise every biomaterial or defect design.
Product complaints, recalls and vigilance
If a suspected device defect, damaged package, label mismatch, unexpected material behaviour or adverse event occurs, preserve identifiers and photographs without compromising care. Record the product name, REF, UDI where applicable, lot, expiry, supplier, procedure date, site, event and action taken.
The treating provider should follow the vigilance rules of the jurisdiction where the device was used. The manufacturer, supplier and relevant regulator may need notification depending on the event. A report does not prove product causation; it creates a traceable safety record.
For care received in Turkey, use the applicable Turkish professional and device-reporting routes. EU EUDAMED or UK MHRA records can help with products in their markets but do not replace Turkish reporting. The patient should receive the complaint policy and professional-regulator details before treatment, not only after a problem.

Read independent evidence without turning it into a promise
Systematic reviews aggregate selected studies with different defects, membranes, grafts, techniques and follow-up. They can identify uncertainty or broad patterns, but they do not prove a named product will succeed in one patient. A finding about collagen versus non-resorbable barriers should not be rewritten as Bio-Gide is better.
The exposure review cited above supports recognising wound opening as clinically meaningful. The smoking review supports addressing tobacco as a regenerative risk factor. Neither provides an individual outcome estimate. Study sponsorship, comparator, inclusion criteria, defect type, membrane variant, graft, fixation and closure should be checked before applying a conclusion.
Manufacturer evidence remains useful for product identity, handling and instruction. Independent clinical evidence is useful for broader benefit-risk questions. Professional judgement and patient preferences connect them to the case. Keep those roles distinct.
Evidence limits of the official sources
The official product page confirms that the manufacturer presents multiple Bio-Gide-family products and standard presentations. The eIFU portal explains how to retrieve an instruction by REF. The accessible DOC-2958 PDF documents one revision for named products. EUDAMED, MHRA and ÜTS sources explain market-specific registration or device-tracking contexts.
None of those sources proves that a named clinic possesses a genuine unit, that the unit was stored correctly, that the diagnosis supports GBR, that the chosen graft and fixation are appropriate, or that the surgery will obtain a desired result. Case-specific labels, supply and clinical records are needed, and uncertainty remains.
Online pages and regulations can change. Record access dates and identifiers. When an old PDF conflicts with the live eIFU, the exact current product and market document should be resolved before use rather than choosing the more favourable wording.
Red flags that justify a pause
Pause if a proposal names Bio-Gide without an exact variant, REF, size or current eIFU; describes it as the bone graft; refuses to identify graft or fixation products; uses a stock package photograph as case proof; or presents a CE mark as global approval or clinic accreditation.
Other warning signs include no defect diagnosis, no discussion of no-graft alternatives, untreated acute infection, undisclosed porcine origin, known collagen allergy not addressed, broken or expired packaging, an undocumented substitute, no lot record, dismissal of pain and recovery uncertainty, a fixed universal schedule, bundled costs without material lines, no exposure or infection plan, and pressure caused by flights.
A red flag is a prompt for evidence, not automatic proof of wrongdoing. Ask for clarification, a revised plan or an independent opinion before irreversible care.
Bio-Gide verification worksheet
| Decision | Question | Evidence |
|---|---|---|
| Diagnosis | What defect is present and why treat it? | Examination, images and diagnosis |
| Alternatives | What happens with no graft or another design? | Written option discussion |
| Product | Which exact Bio-Gide variant and REF? | Current label and eIFU |
| Presentation | Which dimensions or preformed shape? | Sterile blister record |
| Origin | Is the collagen source accepted? | Composition discussion and consent |
| Market | Which jurisdictional record applies? | Relevant database or conformity record |
| Sterility | Were expiry, storage and barrier checked? | Opening and stock record |
| Defect design | How is coverage and space maintained? | Surgical plan |
| Graft | What separate material lies beneath? | Product, source, REF and lot |
| Fixation | Are pins, screws, mesh or sutures used? | Component schedule |
| Closure | How is soft tissue managed? | Flap and contingency plan |
| Risk | How are infection, smoking and health factors addressed? | Risk-control record |
| Traceability | Can every implanted item be linked to the site? | Operation note and labels |
| Cost | Are products and services itemised? | Dated quotation |
| Handover | Can a local clinician understand the case? | Portable record bundle |
An incomplete worksheet does not prove the product is unsuitable. It identifies a decision or evidence gap to resolve before opening the sterile pack.
Primary sources used in this guide
Product-family and presentation context comes from the [official Geistlich Bio-Gide page](https://www.geistlich.com/en-gb/dental-professionals/products/membranes/bio-gide). Current case documents should be retrieved through the [official Geistlich eIFU route](https://www.geistlich.com/en-gb/dental-professionals/professionals/e-ifu) using the label REF. The accessible [manufacturer combination-kit IFU PDF](https://www.geistlich.com/fileadmin/content/Germany/Documents/Gebrauchsanweisungen/Gebrauchsanweisungen_IFU_stand_17.07.23/IFU_Geistlich_Combi-Kit_Collagen.pdf) is cited as a revision-specific example, not as a permanent universal instruction.
Jurisdictional context comes from the [European Commission EUDAMED information](https://health.ec.europa.eu/medical-devices-eudamed/udidevice-registration_en), [MHRA device-registration guidance](https://www.gov.uk/guidance/register-medical-devices-to-place-on-the-market) and [Turkey ÜTS public search](https://utsuygulama.saglik.gov.tr/UTS/vatandas#/vatTibbiCihazListele). Cross-border and urgent-care context comes from the [GDC travel guidance](https://www.gdc-uk.org/standards-guidance/information-for-patients-public/going-abroad-for-dental-treatment) and [NHS dental-abscess guidance](https://www.nhs.uk/conditions/dental-abscess/).
Independent evidence examples are the PubMed-indexed systematic reviews on [membrane exposure](https://pubmed.ncbi.nlm.nih.gov/29368353/) and [smoking in periodontal bone regeneration](https://pubmed.ncbi.nlm.nih.gov/21627463/). They support risk discussion, not a Bio-Gide outcome promise.
Final decision rule
Do not accept Bio-Gide as a complete treatment description. Require a diagnosed defect, reasonable alternatives, exact product and dimensions, current REF-matched eIFU, applicable market evidence, porcine-source consent, intact sterile and batch records, separate graft and fixation identities, a documented coverage and closure design, risk-factor control, complication route, itemised cost and portable aftercare record.
If diagnosis or anatomy remains uncertain, keep the material provisional. If the product or surgical design changes, update the quote and consent. If evidence cannot be obtained, record the limitation instead of replacing it with a brand assurance. This chain does not guarantee regeneration; it makes the decision auditable and future care safer to interpret.
What the product name does — and does not — tell you
Bio-Gide® Membrane is a resorbable collagen membrane product family from Geistlich. The name can help a patient identify a product family, but it does not establish the diagnosis, the exact model selected, the competence of a treating professional or the quality of the finished treatment. Product ranges, indications and local availability can change. A current manufacturer instruction for use and the legal market status in the country of treatment take priority over a marketing page.
This page is a research guide. It is not a statement that WeCare, a particular clinic or an event clinician stocks or uses Bio-Gide® Membrane. Availability must come from the named treating provider. If a quotation uses only a broad phrase such as “premium material”, ask for the manufacturer, product family and reference before accepting the plan.
Manufacturer information worth checking
- The official Geistlich product catalogue presents Bio-Gide, Bio-Gide Compressed, Bio-Gide Perio, Bio-Gide Shape, Bio-Gide Forte and combination presentations as distinct products; the exact name and reference must be recorded.
- The manufacturer eIFU portal instructs users to search by the REF or re-order number on the box or blister and select the applicable language; a generic webpage is not the controlling instruction.
- Accessible manufacturer documentation describes Bio-Gide, Bio-Gide Compressed and Bio-Gide Perio as resorbable bilayer collagen membranes of porcine origin, with product-specific presentation and handling information.
- A barrier membrane is not a bone graft. Any graft, fixation device, implant, suture or medicinal product used with it needs its own identity, rationale and traceability record.
- Product identity and market registration do not diagnose a defect, prove surgical suitability, authenticate one case, verify a provider or predict a regenerative result.
These points describe the product family at a general level. They are not a recommendation for a particular mouth and they should not be extended to a different line carrying a similar brand name. The responsible clinician should first diagnose the hard- or soft-tissue defect, control relevant infection and risk factors, explain no-regeneration and other reasonable alternatives, and then connect the exact membrane, graft or no-graft choice, fixation, closure, maintenance and contingency plan to the individual anatomy.
Questions for the named provider
Ask the professional responsible for treatment to answer these points in writing:
- What is the exact manufacturer, product family, model or material grade proposed?
- What clinical finding makes that selection appropriate for this case, and what alternatives were considered?
- Who is the legal treating provider and who will perform each clinical or laboratory stage?
- Which current instruction for use, contraindications and local regulatory status apply?
- What reference, lot, batch or other traceability record will be retained and shared where the device permits it?
- Which components, cements, abutments, membranes, gels or accessories are included, and are they compatible?
- What follow-up is required, who is responsible after travel, and which costs are excluded from the quotation?
Product verification, evidence and traceability boundaries
Manufacturer product pages, an eIFU, CE or other market information and a package label answer different questions. Case evidence should link the exact REF, dimensions, lot, expiry and sterile label to the surgical site, prescription, graft and fixation records, clinical notes, itemised quote and handover. None of those records alone proves correct diagnosis, technique or outcome.
Useful evidence may include a photograph of unopened labelled packaging before use, the product label, an implant or device record, a laboratory prescription, an invoice identifying the exact material, and the treating provider's signed notes. The appropriate record depends on the product. A logo on a website, a stock photograph, an unlabelled box or a verbal statement is not equivalent to case-specific traceability.
How to compare alternatives fairly
Compare membranes and non-membrane options by diagnosed defect, intended use, source material, resorption and handling characteristics, space-maintenance design, need for fixation, graft relationship, closure strategy, evidence quality, complication management, future serviceability and total documented cost. Do not rank products by one marketing adjective or extend evidence from one variant to another.
Compare like with like: indication, exact product, compatible components, laboratory design, operator responsibility, maintenance, staged visits and written exclusions. Do not compare a named product in one quotation with an unspecified category in another. Brand recognition cannot remove biological uncertainty, and no material choice can promise a clinical outcome.
Assessment comes before the brand
A responsible plan starts with medical and dental history, examination and appropriate imaging. Implant decisions can depend on bone, soft tissue, bite, hygiene, smoking, medication and restorative space. Ceramic decisions can depend on remaining tooth tissue, preparation design, opposing teeth and laboratory workflow. Whitening decisions require screening for decay, gum disease, sensitivity and existing restorations. Endodontic and imaging tools are parts of a broader diagnostic or treatment process, not substitutes for professional judgement.
Before paying, request a dated, itemised written plan naming the treating provider, the proposed product, alternatives, material records, visit stages, aftercare responsibilities and financial terms. If the final assessment changes the product or procedure, ask for the reason and revised quotation before treatment proceeds.